Related Experiment Video
Updated: Apr 25, 2026


Introduction of Intracapsular Rotary-cut Procedures IRCP: A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Single port laparoscopic myomectomy with intracorporeal suture-tying and transumbilical morcellation
Jung Ryeol Lee1, Ji Hyun Lee2, Ju Yeong Kim2
1Department of Obstetrics and Gynecology, Seoul National University Bundang Hospital, Seongnam 463-707, Republic of Korea; Department of Obstetrics and Gynecology, Seoul National University College of Medicine, Seoul 110-744, Republic of Korea.

Objective:
To evaluate the feasibility of single-port laparoscopic myomectomy (SPLM) with intracoporeal suture-tying and transumbilical morcellation.
Study Design:
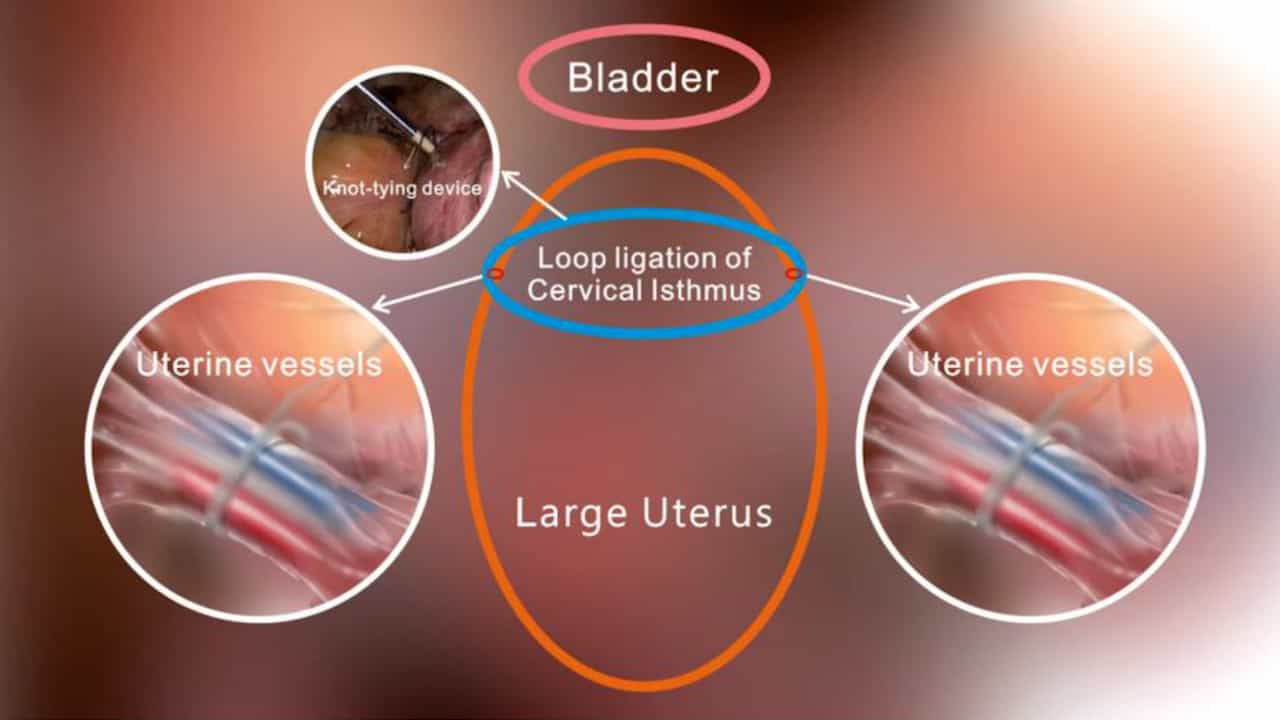
We retrospectively reviewed the medical records of 100 consecutive women who underwent SPLM without any combined surgery between January 2010 and July 2011. The medical records were reviewed and the clinical outcomes were analyzed. Single port entry was established using a wound retractor and a surgical glove. After myoma was enucleated from myometrium, intracorporeal suturing and knot tying was done for myometrium repair. Enucleated myoma was extracted through umbilicus using tissue morcellator. Factors investigated included operation time, blood loss, postoperative hospital stay and complications.
Results:
Mean patient age and BMI were 40.4±7.1 years and 23.1±3.5kg/m(2). Mean diameter of largest myoma and number of myomas were 6.6±2.2 (range 2-12) cm and 1.6±1.2 (range 1-7), respectively. Mean weight of myoma was 136.9±118.4 (range 4-684)g. Type of the main myomas were intramural (80/100), submucosal (5/100), subserosal (12/100), and intraligamentary (3/100). Location of the main myomas were anterior (36/100), posterior (24/100), fundal (30/100), and lateral (10/100). Mean operation time and estimated blood loss were 116.3±36.8min and 94.6±74.5mL. Mean hospital stay after the operation was 2±0.4 days. Conversion to double port surgery (one more trocar inserted on suprapubic site) was occurred in 1 patient due to severe pelvic adhesion. No patient experienced major complications, including bowel, ureter, or bladder injuries, or incisional hernia.
Conclusion:
SPLM is safe and acceptable for various myoma sites and sizes up to 12cm. Intracorporeal suture-tying and transumbilical morcellation are key technical points of SPLM.