Related Experiment Video
Updated: Apr 25, 2026
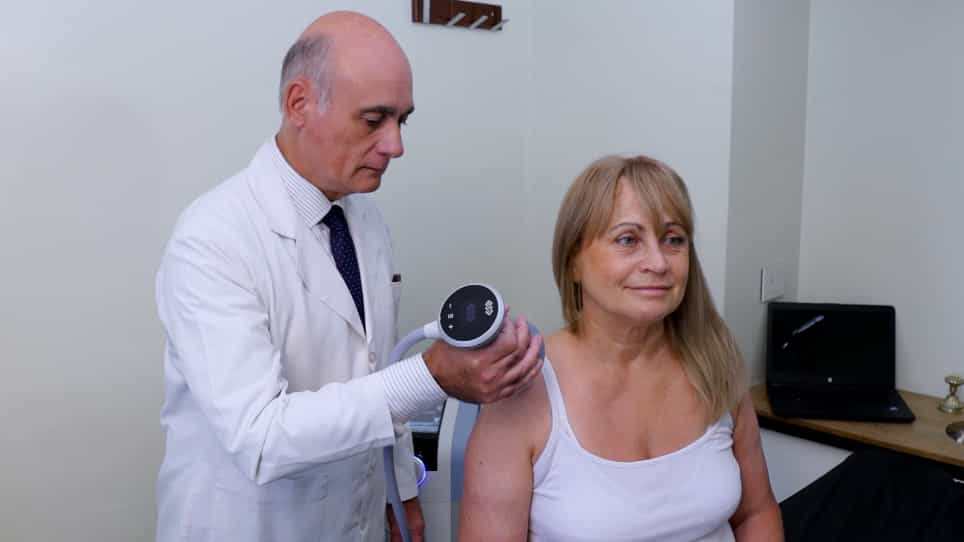
Treatment Protocol for Rotator Cuff Calcific Tendinitis Using a Single-Crystal Piezoelectric Focused Shock Wave Source
Published on: December 23, 2022
Rituximab extended schedule or re-treatment trial for low-tumor burden follicular lymphoma: eastern cooperative
Brad S Kahl1, Fangxin Hong2, Michael E Williams2
1Brad S. Kahl, University of Wisconsin, Madison; Christopher G. Peterson, Aspirus Regional Cancer Center, Wausau; Matthias Weiss, Marshfield Clinic, Marshfield, WI; Fangxin Hong, Dana-Farber Cancer Institute, Boston, MA; Michael E. Williams, University of Virginia, Charlottesville, VA; Randy D. Gascoyne, British Columbia Cancer Agency, Vancouver, British Columbia, Canada; Lynne I. Wagner, Northwestern University, Chicago, IL; John C. Krauss, University of Michigan, Ann Arbor, MI; Thomas M. Habermann, Mayo Clinic, Rochester; Mark D. Sborov, Fairview-Southdale Hospital, St Louis Park, MN; Lode J. Swinnen, Johns Hopkins University, Baltimore, MD; Stephen J. Schuster, University of Pennsylvania, Philadelphia; W. Christopher Ehmann, Penn State Cancer Institute, Hershey, PA; S. Eric Martin, Christiana Care Community Clinical Oncology Program and Helen F. Graham Cancer Network, Newark, DE; and Sandra J. Horning, Genentech, South San Francisco, CA. bsk@medicine.wisc.edu.

Purpose:
In low-tumor burden follicular lymphoma (FL), maintenance rituximab (MR) has been shown to improve progression-free survival when compared with observation. It is not known whether MR provides superior long-term disease control compared with re-treatment rituximab (RR) administered on an as-needed basis. E4402 (RESORT) was a randomized clinical trial designed to compare MR against RR.
Patients And Methods:
Eligible patients with previously untreated low-tumor burden FL received four doses of rituximab, and responding patients were randomly assigned to either RR or MR. Patients receiving RR were eligible for re-treatment at each disease progression until treatment failure. Patients assigned to MR received a single dose of rituximab every 3 months until treatment failure. The primary end point was time to treatment failure. Secondary end points included time to first cytotoxic therapy, toxicity, and health-related quality of life (HRQOL).
Results:
A total of 289 patients were randomly assigned to RR or MR. With a median follow-up of 4.5 years, the estimated median time to treatment failure was 3.9 years for patients receiving RR and 4.3 years for those receiving MR (P = .54). Three-year freedom from cytotoxic therapy was 84% for those receiving RR and 95% for those receiving MR (P = .03). The median number of rituximab doses was four patients receiving RR and 18 for those receiving MR. There was no difference in HRQOL. Grade 3 to 4 toxicities were infrequent in both arms.
Conclusion:
In low-tumor burden FL, a re-treatment strategy uses less rituximab while providing disease control comparable to that achieved with a maintenance strategy.