Related Experiment Video
Updated: Apr 25, 2026
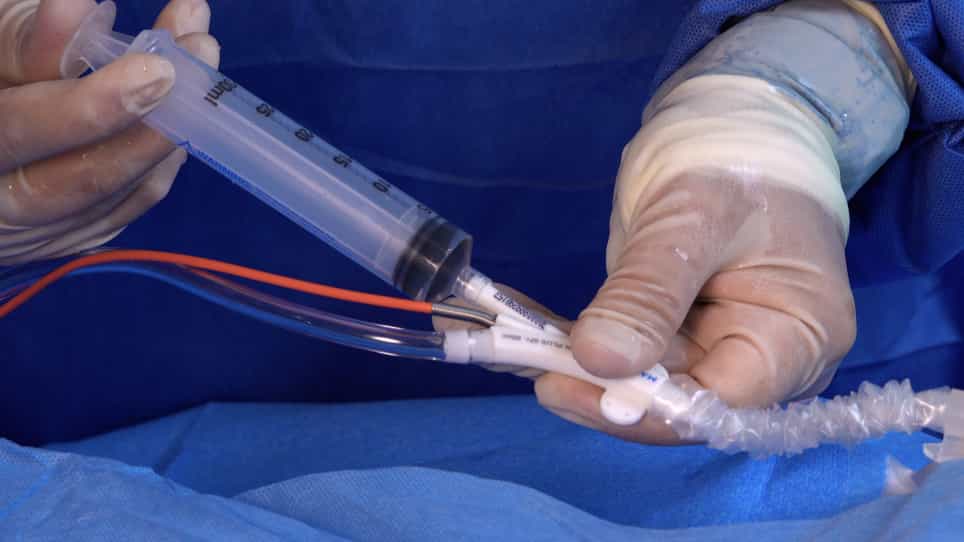

The Intra-Aortic Balloon Pump
Published on: February 5, 2021
[Influence of ECMO and IABP on coronary blood flow. Valuable combination or waste of resources?]
T Schroeter1, M Vollroth, M Höbartner
1Herzzentrum Leipzig, Universität Leipzig, Strümpellstr. 39, 04289, Leipzig, Deutschland, thomas.schroeter@herzzentrum-leipzig.de.

Insights
Simultaneous use of intra-aortic balloon pump (IABP) and extracorporeal membrane oxygenation (ECMO) improves coronary blood flow in antegrade perfusion. However, IABP impairs coronary perfusion during retrograde perfusion, reducing blood pressure in the left anterior descending artery.
Area of Science:
- Cardiovascular Research
- Medical Device Technology
- Hemodynamics
Background:
- Intra-aortic balloon pump (IABP) and extracorporeal membrane oxygenation (ECMO) are critical for severe cardiogenic shock stabilization.
- Limited data exist on the combined use of IABP and ECMO.
- Assessing the impact of concomitant IABP and ECMO on coronary blood flow is crucial.
Purpose of the Study:
- To evaluate the effect of simultaneous IABP and ECMO on coronary blood flow.
- To compare antegrade versus retrograde perfusion strategies with combined IABP and ECMO support.
Main Methods:
- Adult pigs underwent median sternotomy under general anesthesia.
- Arterial ECMO was established via ascending aorta or femoral artery; IABP was inserted via the femoral artery.
- Measurements included arterial pressure in the left anterior descending artery (LAD), left atrial pressure, lactate, and coronary sinus oxygen saturation under varying ECMO support levels (50% and 100% cardiac output) with and without IABP.
Main Results:
- Concomitant IABP and ECMO use is feasible for antegrade perfusion, enhancing coronary artery blood pressure and myocardial oxygen supply.
- In retrograde perfusion, IABP use reduced LAD blood pressure and oxygen supply.
- Antegrade perfusion with IABP support demonstrated significantly higher mean arterial pressure in the LAD compared to retrograde perfusion.
Conclusions:
- Simultaneous IABP and ECMO support is beneficial in antegrade perfusion settings.
- IABP use during retrograde perfusion negatively impacts mean arterial pressure and coronary artery perfusion.
Background:
The treatment of patients in severe cardiogenic shock with an intra-aortic balloon pump (IABP) or extracorporeal membrane oxygenation (ECMO) is a common procedure to achieve stabilization. Only limited data are available on the simultaneous use of both systems. The aim of the present study was to assess the effect of the concomitant use of IABP and ECMO on coronary blood flow. In addition, the influence of antegrade and retrograde perfusion was evaluated.
Methods:
A median sternotomy was performed in adult pigs under general anesthesia. Arterial ECMO perfusion was realized through the ascending aorta or the femoral artery, and the IABP was implanted via the second femoral artery. Six measurements of arterial pressure in the left anterior descending artery (LAD) and in the left atrium were made at intervals of 2 min. In addition, lactate concentration and oxygen saturation in the coronary sinus were recorded. The ECMO support was either 100 or 50 % of cardiac output. Each experiment was carried out first without and then with additional IABP support.
Results:
The simultaneous use of ECMO and IABP is feasible for antegrade perfusion, where the IABP leads to an increase of blood pressure in the coronary arteries. In addition, the myocardial oxygen supply improves. By contrast, the use of an IABP in retrograde perfusion leads to a reduction of blood pressure in the LAD and to a reduced oxygen supply. A comparison between antegrade and retrograde perfusion with IABP support showed significantly better mean arterial pressure in the LAD for antegrade perfusion. Without IABP, blood pressure in the LAD was better in retrograde perfusion.
Conclusion:
In antegrade perfusion the simultaneous use of IABP and ECMO is useful. In retrograde perfusion IABP impairs the mean arterial pressure and consequently the perfusion of the coronary arteries.
Related Concept Videos
 01:17
Autoregulation of Blood Flow
Chemical Signaling in Autoregulation
Chemical signaling operates at the precapillary sphincter level, inciting either contraction or relaxation....
 01:19
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
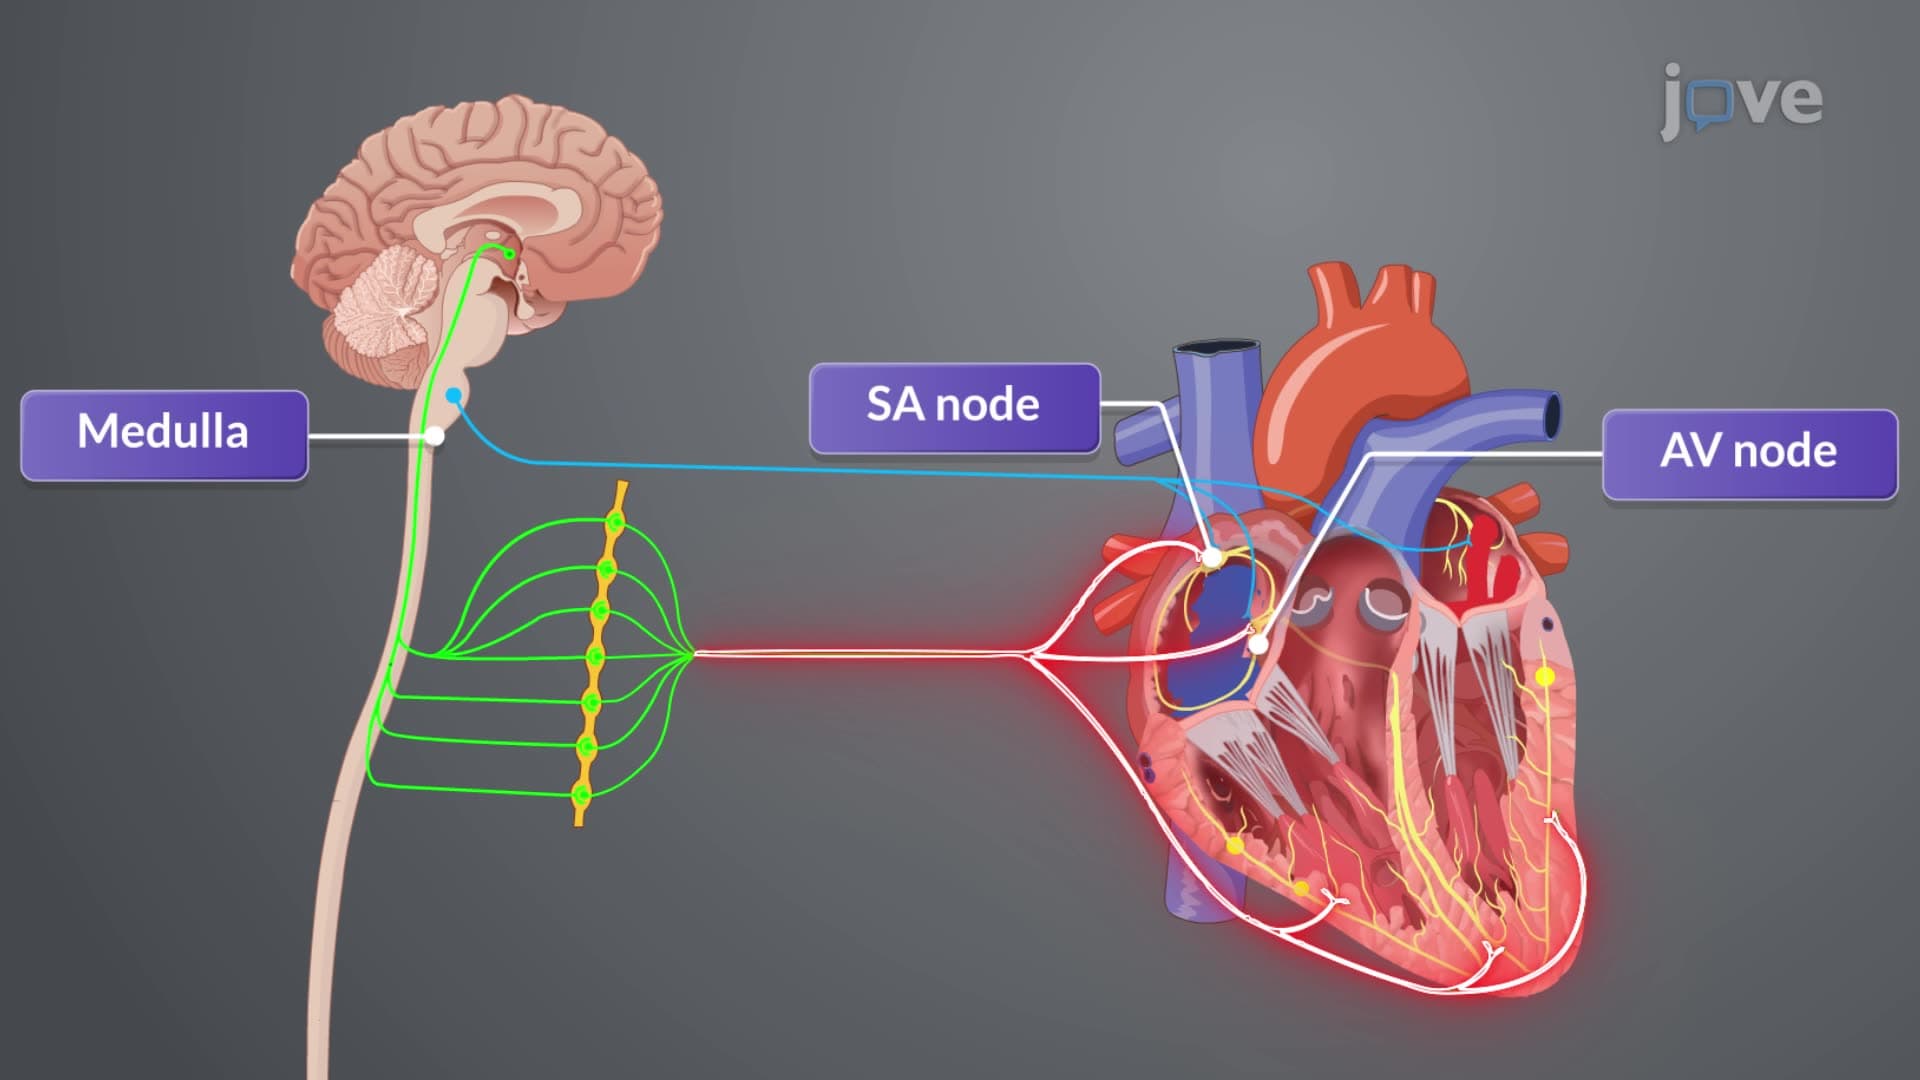
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:29
Pathophysiology of Cardiac Performance
 01:29
Blood Flow
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...