Related Experiment Video
Updated: Aug 14, 2026
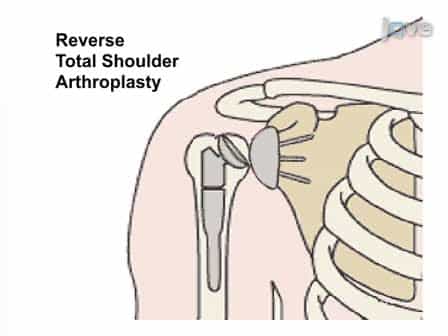
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
[The treatment of dislocated supracondylar humerus fractures in childhood]

Insights
Open reduction and internal fixation using K-wires is recommended for displaced supracondylar humerus fractures (SFH) in children, offering excellent outcomes. Percutaneous pinning is a viable alternative for simpler cases.
Area of Science:
- Pediatric Orthopedics
- Traumatology
- Surgical Innovation
Background:
- Displaced supracondylar humerus fractures (SFH) are common in children.
- Optimal surgical management for these fractures remains a topic of discussion.
- Neurovascular complications can occur with SFH.
Purpose of the Study:
- To evaluate the outcomes of operative management for displaced SFH in children.
- To compare open reduction and internal fixation with closed reduction and percutaneous pinning.
- To assess the incidence of neurovascular complications and functional results.
Main Methods:
- A cohort of 33 children with displaced SFH underwent operative treatment.
- The primary method was open reduction and internal fixation with K-wires (32 cases).
- One case involved closed reduction and percutaneous pinning; neurovascular structures were assessed intraoperatively.
Main Results:
- Excellent or good results were achieved in all 30 reviewed patients (Innocenti's criteria).
- 18% of cases had documented initial neurovascular injury; no nerve sutures were required.
- One patient needed arterial reconstruction due to intima lesions; no early operative complications occurred.
Conclusions:
- Open reduction and internal fixation with K-wires is the preferred method for displaced SFH in children.
- Percutaneous pinning is a suitable alternative if closed reduction is easily achieved.
- The study demonstrates high efficacy and safety of operative management for pediatric SFH.
Abstract:
33 children with displaced SFH were all treated operatively by open reduction and internal fixation or closed reduction and percutaneous pinning. A follow-up study was performed on average 29 (range 3-63) months after the injury. In 18% of the cases an initial injury of the neurovascular structures was observed and documented during the operation. 32 times open reduction and internal fixation by K-wires was performed, only once, closed reduction and percutaneous pinning was attempted. In the presence of a preoperative neurologic deficit, the nerves were always visualised, never, however, a nerve suture was necessary. In one case we had to reconstruct both the arteria brachialis and radialis because of intima lesions with total obstruction of the vessels. The average time of hospitalization was 9 days, which includes the time for removal of the pins, which was usually performed about 4,5 weeks later simultaneously with the removal of plaster. Using Innocenti's criteria, 27 of 30 reviewed patients had an excellent result, 3 had a good result. Early complications due to the operation such as wound healing problems, infection or nerve lesions did not occur. 3 patients could not be reached any more. We recommend for the management of the displaced SFH open reduction and internal fixation by K-wires as the method of choice. Percutaneous pinning is a valid alternative when closed reduction succeeds easily at the first attempt.
More Related Videos
 04:41
Treatment with Locking Intramedullary Nailing for Intertrochanteric Fracture of the Femur Utilizing a New Awl with a Distal Positioner
Published on: June 6, 2025
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
