Related Experiment Video
Updated: Apr 25, 2026

Transoral Endoscopic Thyroidectomy Vestibular Approach for Thyroid Lobectomy
Published on: May 12, 2023
Elective neck dissection for primary oral cavity squamous cell carcinoma involving the tongue should include sublevel
Nigel Gordon Maher1, Gary Russell Hoffman2
1Dermatology Registrar, Department of Dermatology, St George Hospital, Sydney, Australia; Conjoint Associate Lecturer, University of New South Wales, Sydney, Australia.

Purpose:
The surgical clearance of sublevel IIb lymph nodes, facilitated by neck dissection, increases the risk of postoperative shoulder dysfunction. Our study purpose was to determine the value of including sublevel IIb in elective neck dissections for primary oral cavity squamous cell carcinoma (OCSCC).
Materials And Methods:
A retrospective cohort study based on a review of the pathology records accumulated by 1 head and neck surgeon was conducted for 71 patients with clinically node-negative, primary OCSCC treated from 2006 to June 2013. The predictor variables were the oral cavity subsite and tumor clinicopathologic characteristics (ie, perineural, perivascular, and perilymphatic invasion, tumor depth, and T stage). The primary outcome variable was the presence of sublevel IIb metastasis. The secondary outcome variables were the survival and tumor recurrence rates and metastases to any cervical level. Descriptive statistics were calculated for the categorical and continuous variables. A comparison of categorical variables was performed using Fisher's exact test; for continuous variables, t tests or the Mann-Whitney U test were used for 2 groups and analysis of variance or Kruskal-Wallis tests (with Bonferroni's correction) were used for more than 2 groups, depending on the distribution. Disease-specific survival (DSS) analyses were plotted for the predictor variables and patients with sublevel IIb metastasis. Competing risks models were created using the Fine and Gray method (SAS macro %PSHREG) to provide estimates of the crude and adjusted subhazard ratios for DSS for all variables.
Results:
A total of 71 patients were included in the present study, of whom 69% were male. The greatest proportion of oral cavity subsites was from the tongue and floor of mouth. The overall frequency of sublevel IIb lymphatic metastases at neck dissection was 5.6% of the patient cohort. Sublevel IIb metastases occurred from the primary sites involving the tongue (n = 3) and retromolar trigone (n = 1). The incidence of perilymphatic and perivascular invasion was significantly associated with sublevel IIb lymphatic metastases (P < .02).
Conclusions:
Sublevel IIb is likely to be an important region to incorporate in elective neck dissections for primary OCSCC involving the tongue. More studies are needed, with greater numbers, to clarify the risk of metastasis to sublevel IIb from oral cavity subsites in primary OCSCC with clinically node-negative necks.

Related Concept Videos
 01:26
Assessment of the Mouth
Mouth Inspection
The inspection begins with visually examining the mouth for symmetry, color, and size.
 01:01
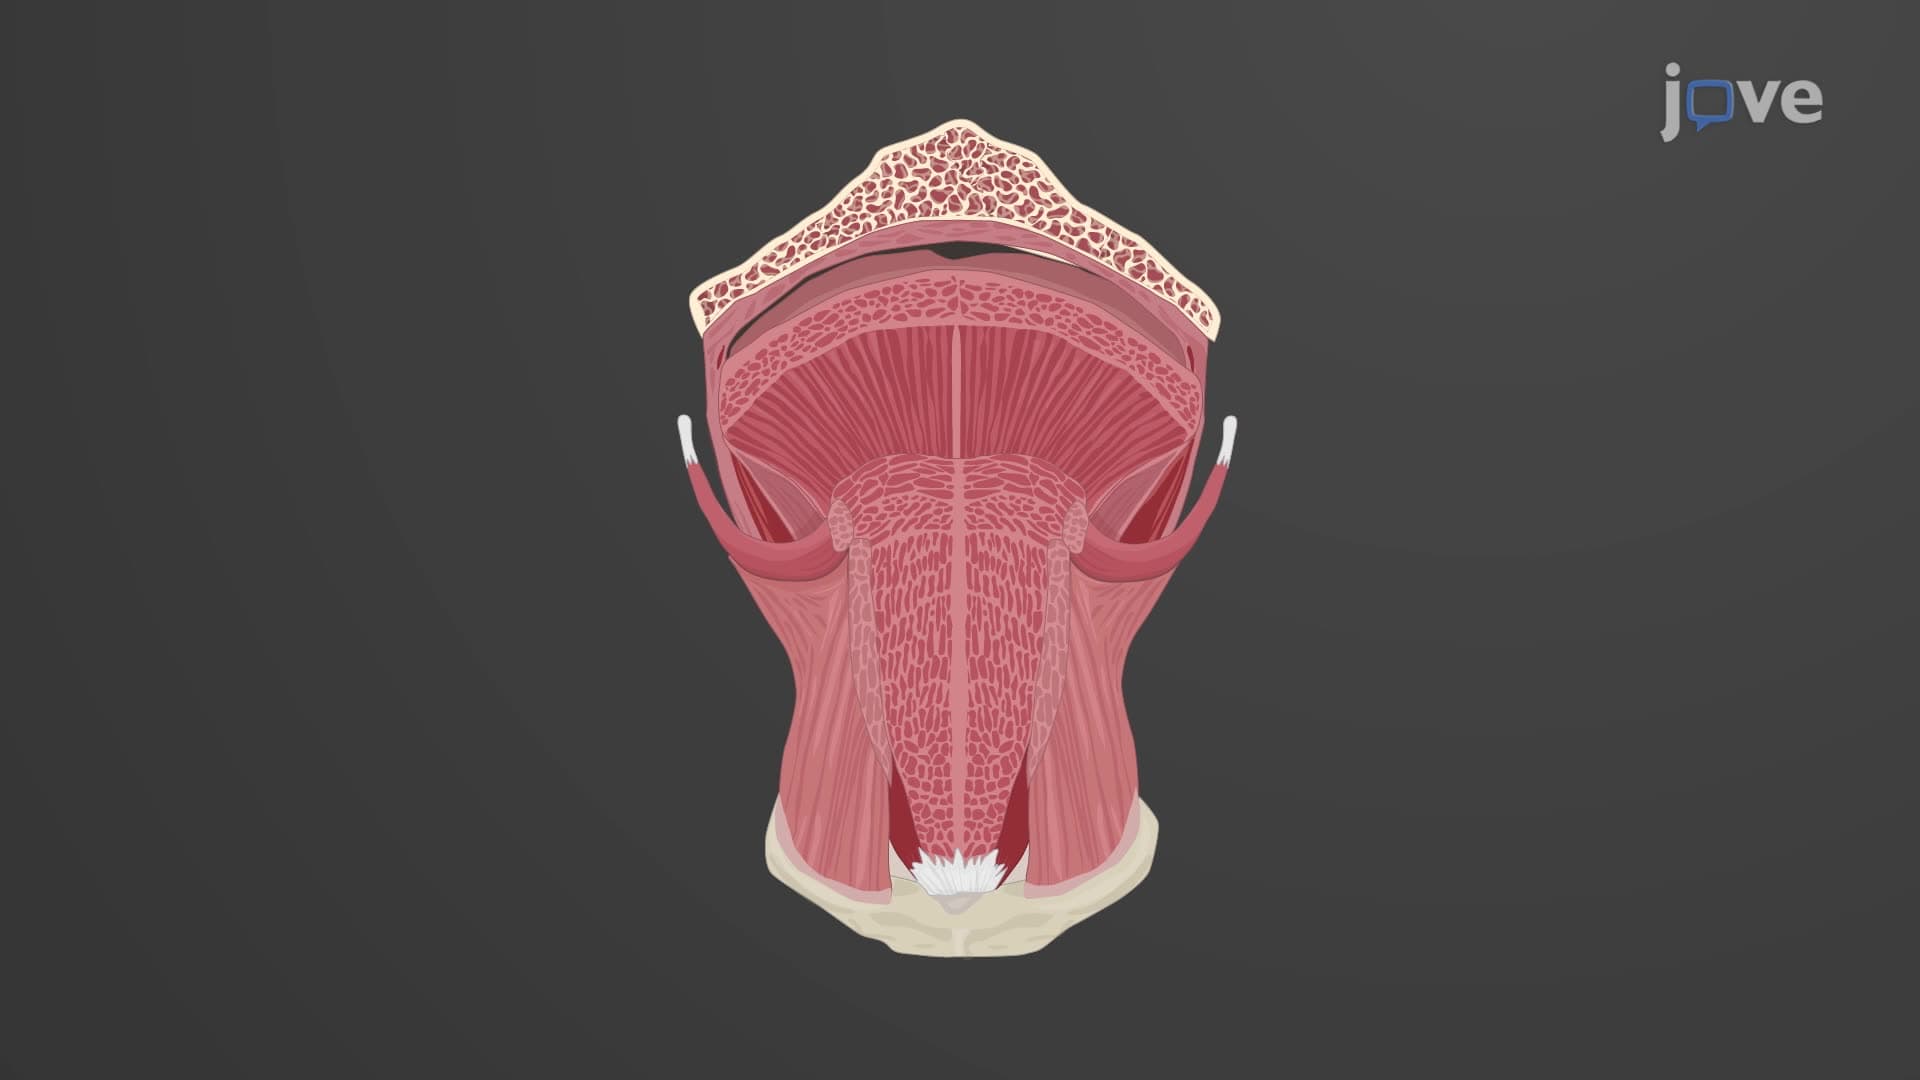
Tongue
Anatomical Position in the Oral Cavity
The tongue is located within the oral cavity, also known as the mouth. It is attached to the floor of the mouth by a fold of mucous membrane called the...