Related Experiment Video
Updated: Apr 25, 2026


Author Spotlight: Repetitive Transcranial Magnetic Stimulation Combined with Movement Observation in Cerebral Palsy
Published on: August 9, 2024
Practice experience in the treatment of infantile spasms at a tertiary care center
Drew Thodeson1, Yoshimi Sogawa2
1Division of Child Neurology/Epilepsy, Children's Hospital of Pittsburgh of UPMC, Pittsburgh, Pennsylvania.

Insights
Treatment choices for infantile spasms vary, especially when the cause is known. Etiology strongly influences initial treatment selection, highlighting the need for more clinical trial evidence.
Area of Science:
- Pediatric Neurology
- Clinical Pediatrics
Background:
- Infantile spasms treatment guidelines lack clarity for cases with known etiology.
- Recent surveys show significant variation in infantile spasms treatment approaches.
- Limited evidence exists for guiding infantile spasms treatment selection.
Purpose of the Study:
- To investigate clinical variables influencing treatment selection for new-onset infantile spasms.
- To analyze treatment variations based on etiology in infantile spasms.
Main Methods:
- Retrospective review of medical records for 65 children with new-onset infantile spasms over 3 years.
- Categorization of treatments into vigabatrin, hormone therapy, and other therapies.
- Systematic extraction of demographic data and treatment response.
Main Results:
- 74% of patients had a known etiology for infantile spasms.
- Vigabatrin was the initial treatment for 62% of patients.
- Other therapies were more common initial treatments in known etiology (40%) versus unknown etiology (6%) cases (P=0.002).
- Initial treatment effectiveness was 35%; 86% of non-responders received subsequent trials within 3 months.
- Treatment response at 3 months did not differ significantly between known and unknown etiology groups (P=0.08).
Conclusions:
- Patient's etiology is a significant factor in initial infantile spasms treatment choice.
- Treatment variations observed reflect a lack of robust clinical trial data.
- Further research is needed to establish evidence-based treatment guidelines.
Background:
The current treatment guidelines for treatment of infantile spasms is ambiguous regarding individuals with known etiology and is backed by limited evidence. Recently published survey data reveal diverse treatment variation for infantile spasms. We conducted a retrospective medical record review to better understand the clinical variables which affect treatment selection for new-onset infantile spasms.
Methods:
We systematically extracted demographic data and treatment response of children with new onset infantile spasms over a 3-year period at a single institution. Treatment was divided into three groups: vigabatrin, hormone treatment, and other therapies.
Results:
Our final cohort had 65 patients; 74% had a known etiology. Sixty-two percent were initially treated with vigabatrin. Other therapies were used more often in known etiology than in unknown etiology as initial treatment (40% versus 6%; P = 0.002). Treatment response at 3 months was not statistically different between unknown etiology and known etiology groups (71% versus 46%; P = 0.08). Overall, initial treatment choice was effective in 35% (23 of 65). Eighty-six percent (37 of 42) who failed the initial medication had subsequent medication trials within 3 months.
Conclusions:
Etiology was strongly associated with initial treatment choice. The variation in treatment choice at our center reflects the limited evidence derived from well-designed clinical trials.
More Related Videos

Related Concept Videos
 01:29
Spasmolytic Agents: Chemical Classification
A major class of centrally acting spasmolytics is the α2-agonist, such as tizanidine. These drugs bind to α2-adrenoceptors, inhibiting the release of the excitatory neurotransmitter glutamate. They also...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:24
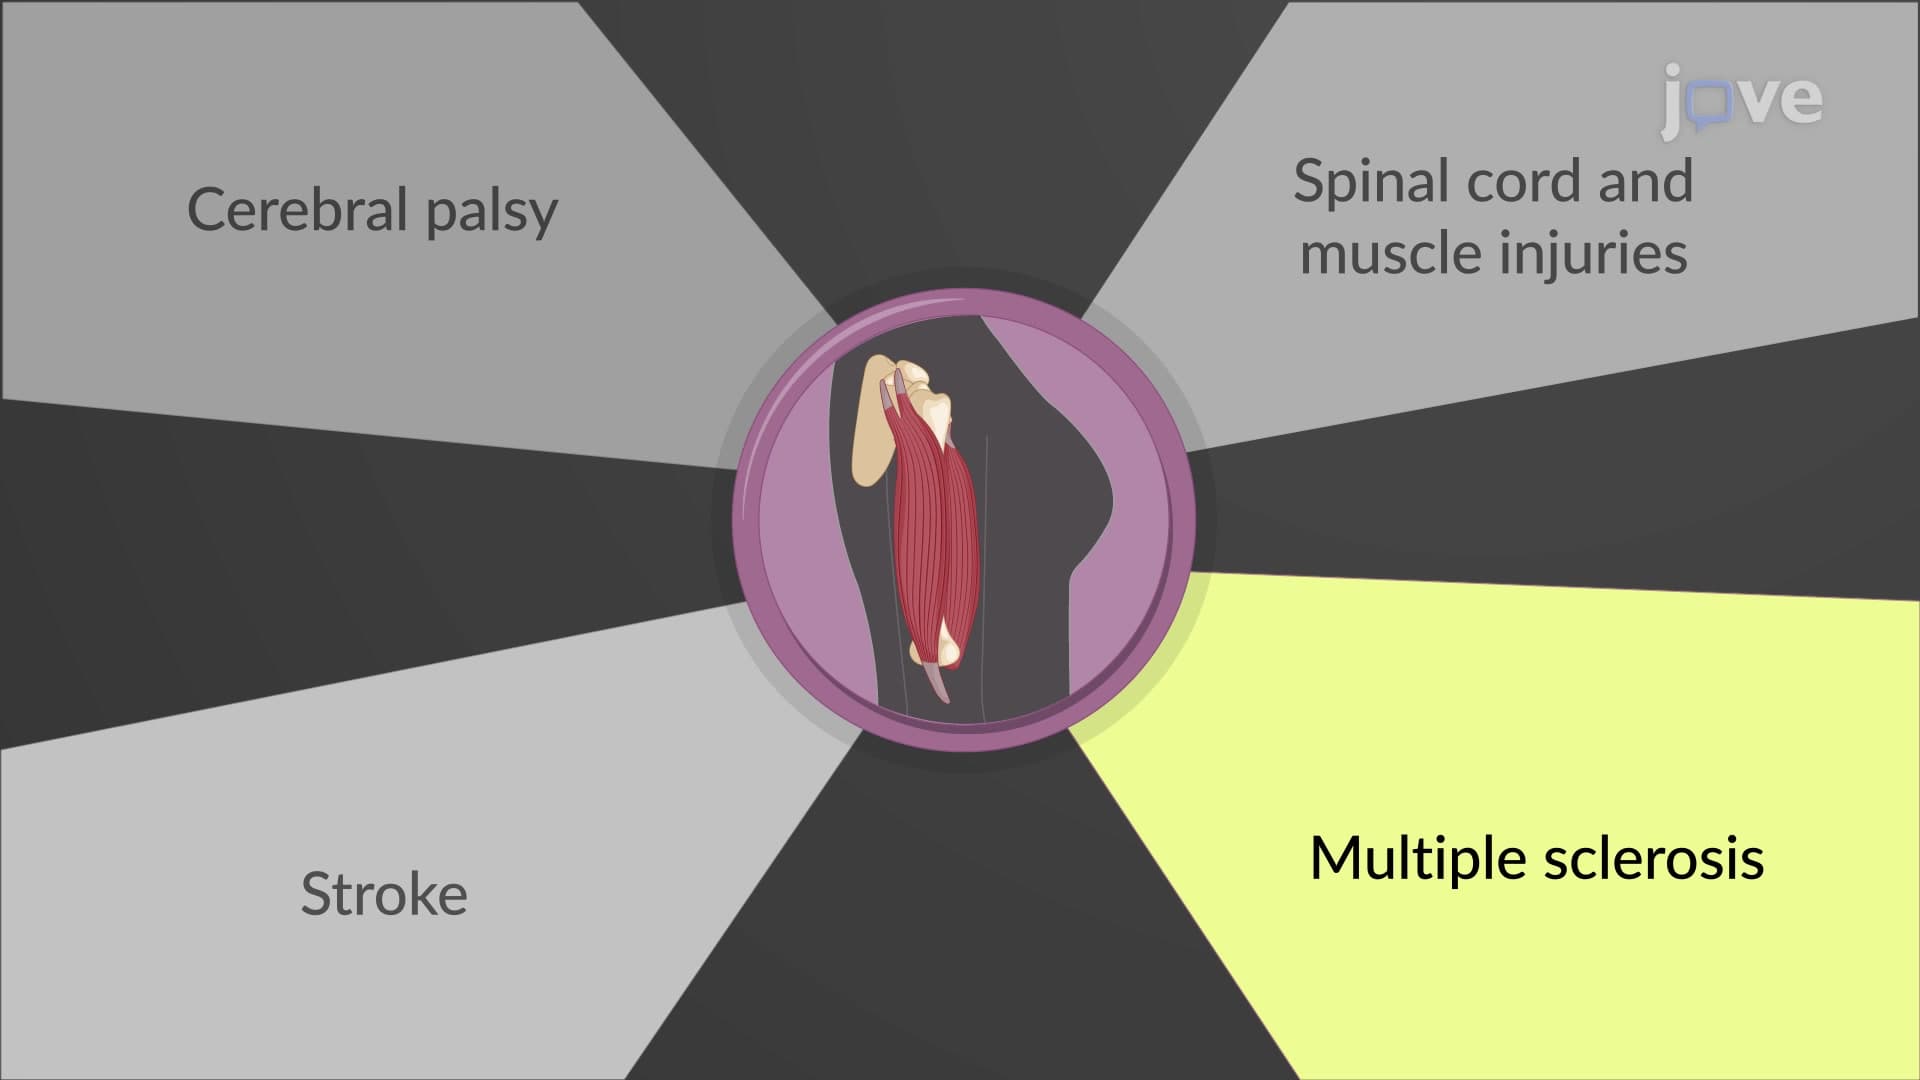
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...
 01:09
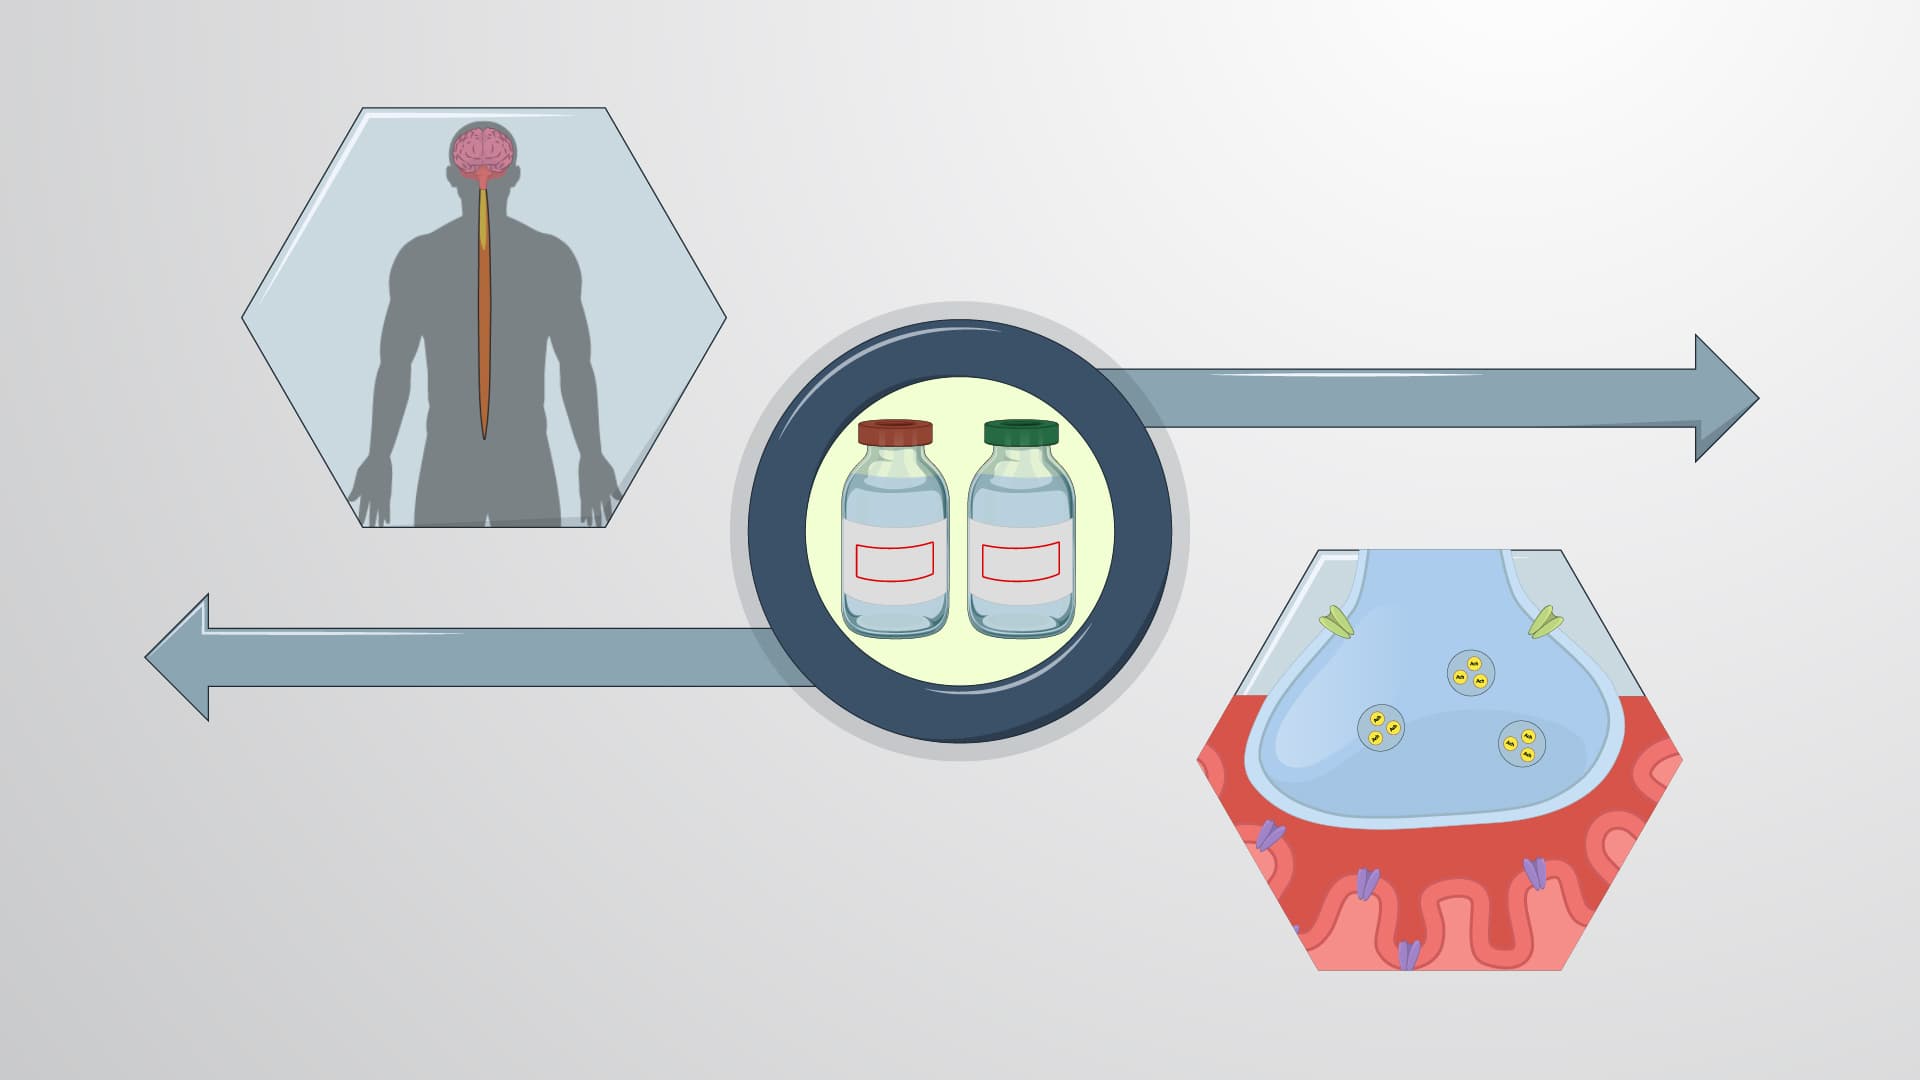
Peripherally and Centrally Acting Muscle Relaxants: A Comparison
Centrally acting muscle relaxants can be further divided into spasmolytic and antispasmodic drugs. Spasmolytic...
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:20
Antiepileptic Drugs: Modulators of Neurotransmitter Release Mediated by SV2A Protein
SV2A is a transmembrane glycoprotein located predominantly in the brain, modulating the release of neurotransmitters for neuronal communication. Both levetiracetam and brivaracetam exhibit a high affinity for...