Related Experiment Video
Updated: Apr 24, 2026
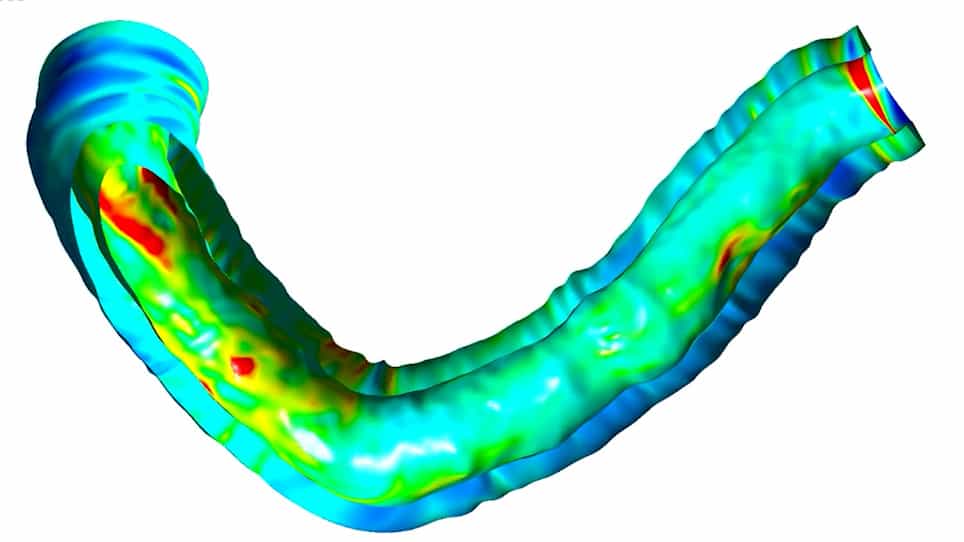
Optical Coherence Tomography Based Biomechanical Fluid-Structure Interaction Analysis of Coronary Atherosclerosis Progression
Published on: January 15, 2022
Differences determined by optical coherence tomography volumetric analysis in non-culprit lesion morphology and
Micheli Zanotti Galon1, Zhao Wang, Hiram G Bezerra
1Heart Institute - InCor, São Paulo University Medical School, São Paulo, Brazil.

Insights
This study reveals that patients with ST-elevation myocardial infarction (STEMI) have thinner fibrous cap (FC) thickness and larger thin-cap fibroatheroma (TCFA) areas with increased inflammation in non-culprit lesions compared to stable angina pectoris (SAP) patients.
Area of Science:
- Cardiovascular Imaging
- Biomedical Engineering
- Pathology
Background:
- Current methods for fibrous cap (FC) thickness measurement in lipid plaques are manual, leading to variability and inaccuracy.
- These methods overlook the three-dimensional (3-D) morphology of coronary artery disease.
Purpose of the Study:
- To compare volumetric FC quantification and macrophage detection using optical coherence tomography (OCT) in non-culprit lesions of STEMI and SAP patients.
- To assess both visual and automated image processing for macrophage detection.
Main Methods:
- Lipid plaques from 67 patients were analyzed using OCT.
- FC was manually delineated and automatically categorized by thickness (thin-cap fibroatheroma [TCFA] <65 μm, 65-150 μm, >150 μm).
- Automated detection and quantification of macrophages within the segmented FC were performed.
Main Results:
- STEMI patients exhibited significantly larger absolute categorical surface area for TCFA (0.43±0.45 mm² vs. 0.15±0.25 mm²; P=0.011) compared to SAP patients.
- Minimum FC thickness was significantly thinner in STEMI patients (31.63±17.09 µm vs. 47.27±26.56 µm; P=0.012).
- STEMI patients showed a greater fractional luminal area for TCFA (1.65±1.56% vs. 0.74±1.2%; P=0.046) and a higher macrophage index (0.0217±0.0081% vs. 0.0153±0.0045%; P<0.01).
Conclusions:
- Novel OCT-based 3-D quantification reveals thinner FC and larger TCFA areas in non-culprit lesions of STEMI patients.
- Increased inflammation, indicated by a higher macrophage index, is associated with these findings in STEMI.
- These results highlight significant differences in plaque morphology and inflammation between STEMI and SAP patients.
Background:
While the current methodology for determining fibrous cap (FC) thickness of lipid plaques is based on manual measurements of arbitrary points, which could lead to high variability and decreased accuracy, it ignores the three-dimensional (3-D) morphology of coronary artery disease.
Objective:
To compare, utilizing optical coherence tomography (OCT) assessments, volumetric quantification of FC, and macrophage detection using both visual assessment and automated image processing algorithms in non-culprit lesions of STEMI and stable angina pectoris (SAP) patients.
Methods:
Lipid plaques were selected from 67 consecutive patients (1 artery/patient). FC was manually delineated by a computer-aided method and automatically classified into three thickness categories: FC < 65 μm (i.e., thin-cap fibroatheroma [TCFA]), 65-150 μm, and >150 μm. Minimum thickness, absolute categorical surface area, and fractional luminal area of FC were analyzed. Automated detection and quantification of macrophage was performed within the segmented FC.
Results:
A total of 5,503 cross-sections were analyzed. STEMI patients when compared with SAP patients had more absolute categorical surface area for TCFA (0.43 ± 0.45 mm(2) vs. 0.15 ± 0.25 mm(2) ; P = 0.011), thinner minimum FC thickness (31.63 ± 17.09 µm vs. 47.27 ± 26.56 µm, P = 0.012), greater fractional luminal area for TCFA (1.65 ± 1.56% vs. 0.74 ± 1.2%, P = 0.046), and greater macrophage index (0.0217 ± 0.0081% vs. 0.0153 ± 0.0045%, respectively, P < 0.01).
Conclusion:
The novel OCT-based 3-D quantification of the FC and macrophage demonstrated thinner FC thickness and larger areas of TCFA coupled with more inflammation in non-culprit sites of STEMI compared with SAP.

Related Concept Videos
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Coronary Syndrome I: Introduction
 01:29
Angina III: Clinical Manifestations and Assessment