Estimating equations for cardiopulmonary exercise testing variables in Fontan patients: derivation and validation using a multicenter cross-sectional database
Related Experiment Video
Updated: Apr 24, 2026
Integration of Brain Tissue Saturation Monitoring in Cardiopulmonary Exercise Testing in Patients with Heart Failure
Published on: October 1, 2019
Ryan J Butts1, Carolyn T Spencer, Lanier Jackson
1Division of Cardiology, Department of Pediatrics, Medical University of South Carolina, 165 Ashley Avenue, MSC 915, Charleston, SC, 29425, USA, butts@musc.edu.

Abstract:
Cardiopulmonary exercise testing (CPET) is a common method of evaluating patients with a Fontan circulation. Equations to calculate predicted CPET values are based on children with normal circulation. This study aims to create predictive equations for CPET variables solely based on patients with Fontan circulation. Patients who performed CPET in the multicenter Pediatric Heart Network Fontan Cross-Sectional Study were screened. Peak variable equations were calculated using patients who performed a maximal test (RER > 1.1) and anaerobic threshold (AT) variable equations on patients where AT was adequately calculated. Eighty percent of each cohort was randomly selected to derive the predictive equation and the remaining served as a validation cohort. Linear regression analysis was performed for each CPET variable within the derivation cohort. The resulting equations were applied to calculate predicted values in the validation cohort. Observed versus predicted variables were compared in the validation cohort using linear regression. 411 patients underwent CPET, 166 performed maximal exercise tests and 317 had adequately calculated AT. Predictive equations for peak CPET variables had good performance; peak VO2, R (2) = 0.61; maximum work, R (2) = 0.61; maximum O2 pulse, R (2) = 0.59. The equations for CPET variables at AT explained less of the variability; VO2 at AT, R (2) = 0.15; work at AT, R (2) = 0.39; O2 pulse at AT, R (2) = 0.34; VE/VCO2 at AT, R (2) = 0.18; VE/VO2 at AT, R (2) = 0.14. Only the models for VE/VCO2 and VE/VO2 at AT had significantly worse performance in validation cohort. Of the 8 equations for commonly measured CPET variables, six were able to be validated. The equations for peak variables were more robust in explaining variation in values than AT equations.
More Related Videos
 07:09
Assessment of Pulmonary Capillary Blood Volume, Membrane Diffusing Capacity, and Intrapulmonary Arteriovenous Anastomoses During Exercise
Published on: February 20, 2017
 08:44
Author Spotlight: Integrating Alveolar-Capillary Reserve Measurements in Exercise Adaptation and Therapeutic Strategies
Published on: February 2, 2024
Related Concept Videos
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical cardiac...
 01:26
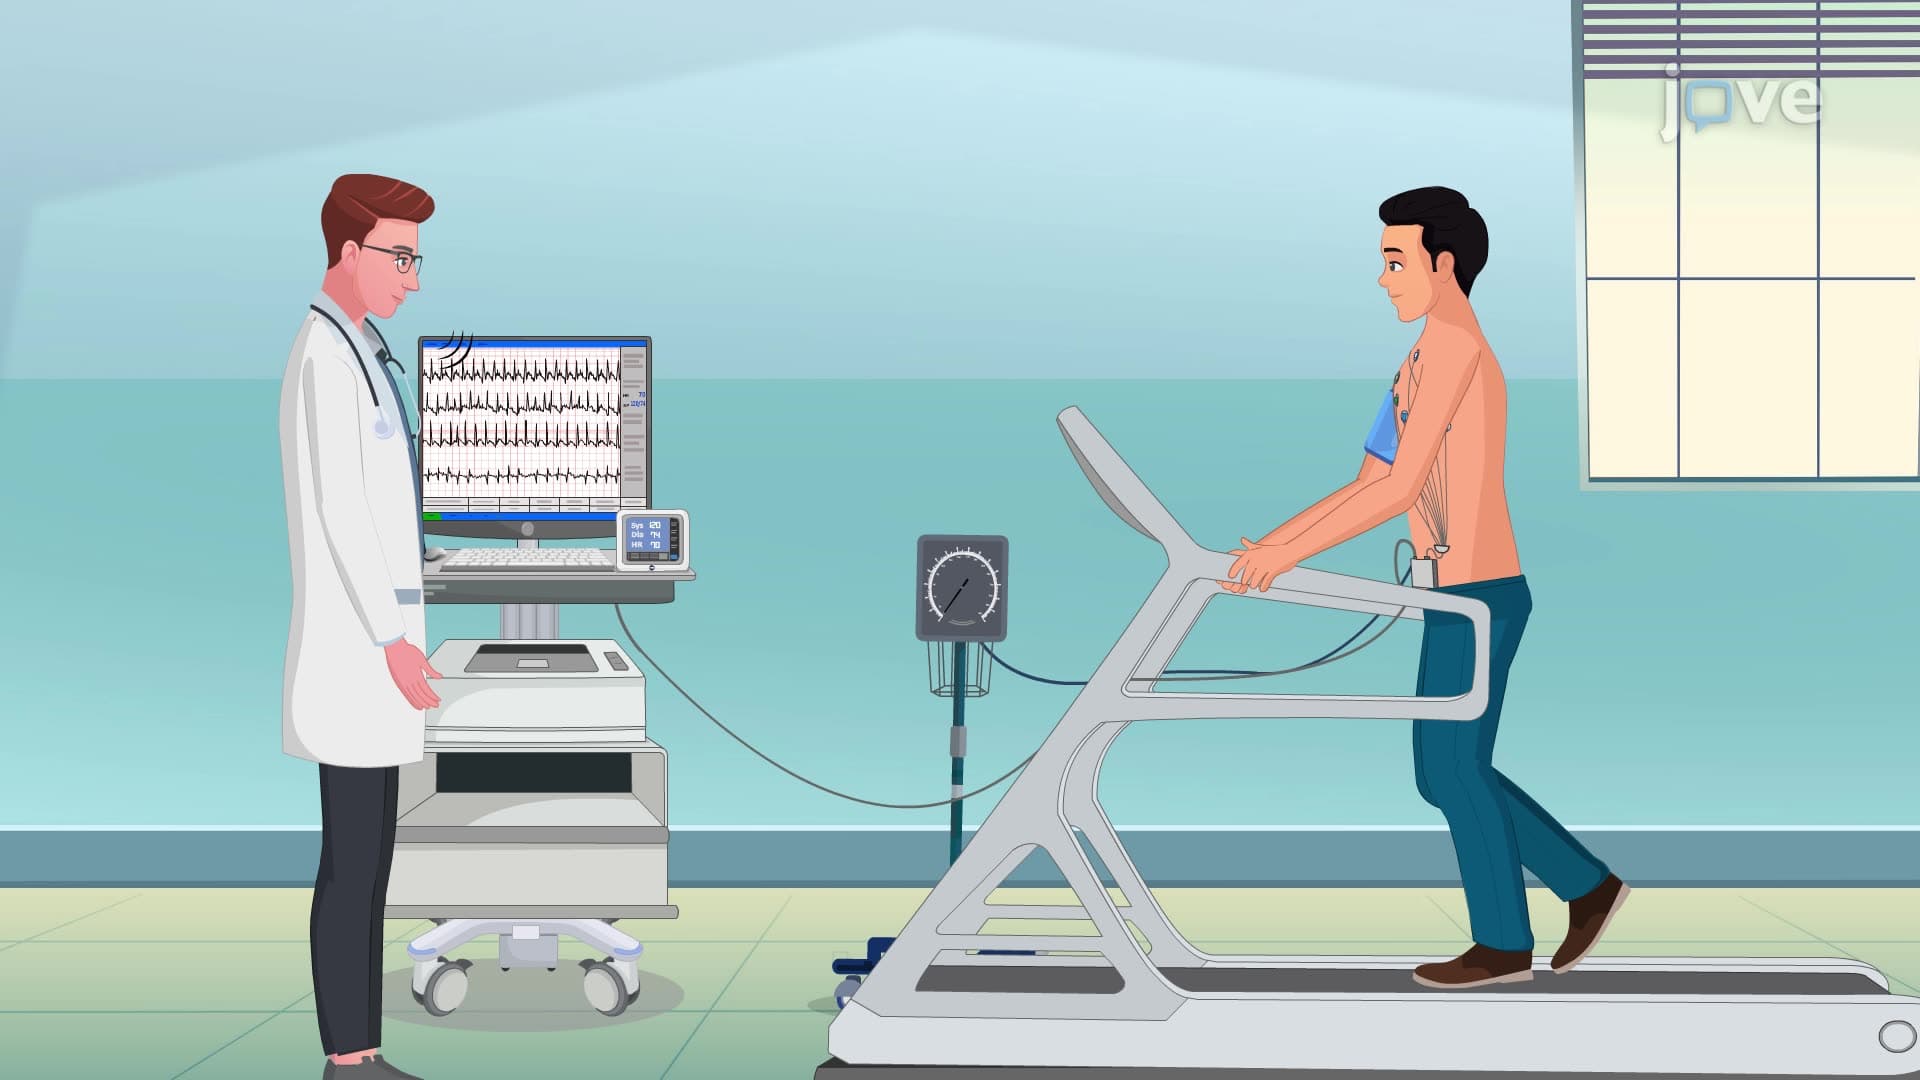
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes