Related Experiment Video
Updated: Apr 24, 2026

Author Spotlight: Integrating Tai Chi with Mindfulness Training to Achieve an Effective Mind-Body Exercise
Published on: July 14, 2023
Association between serum cystatin C and diabetic peripheral neuropathy: a cross-sectional study of a Chinese type 2
Yanyun Hu1, Fang Liu2, Jing Shen1
1Department of Endocrinology and MetabolismShanghai Jiaotong University Affiliated Sixth People's Hospital, Shanghai, ChinaShanghai Key Laboratory of DiabetesShanghai Institute of Diabetes, Shanghai Clinical Medical Center of Diabetes, Shanghai Key Clinical Center of Metabolic Diseases, Shanghai, ChinaDepartments of Vascular SurgeryInterventional RadiologyShanghai Jiaotong University Affiliated Sixth People's Hospital, Shanghai, China Department of Endocrinology and MetabolismShanghai Jiaotong University Affiliated Sixth People's Hospital, Shanghai, ChinaShanghai Key Laboratory of DiabetesShanghai Institute of Diabetes, Shanghai Clinical Medical Center of Diabetes, Shanghai Key Clinical Center of Metabolic Diseases, Shanghai, ChinaDepartments of Vascular SurgeryInterventional RadiologyShanghai Jiaotong University Affiliated Sixth People's Hospital, Shanghai, China.

Objective:
Serum cystatin C (CysC) is a sensitive marker of kidney function and recent studies have shown that CysC plays a critical role in degenerative diseases in both the central and the peripheral nervous systems. The aim of this study was to explore the relationship between serum CysC and diabetic peripheral neuropathy (DPN) in patients with type 2 diabetes.
Methods:
In total, 937 type 2 diabetic patients were enrolled in this cross-sectional study. Serum CysC concentration was measured by immunoturbidimetry. DPN was evaluated by neurological symptoms, neurological signs, neurothesiometer, and electromyogram.
Results:
Serum CysC levels were significantly higher in DPN patients (1.3 (1.1-1.5) mg/l) compared with patients with signs of DPN (1.1 (0.9-1.3) mg/l, P<0.001) and non-DPN patients (1.0 (0.9-1.3) mg/l, P<0.001). Multiple regression analysis revealed that DPN was associated with age, diabetes duration, HbA1c, and serum CysC. Spearman's correlation analysis showed that serum CysC was closely related with age, sex, diabetes duration, hypertension, glomerular infiltration rate, and serum creatinine (Cr) level. The patients were divided into quartiles according to the serum CysC levels. Compared with quartile 1 (referent), the risk of DPN was significantly higher in quartile 2 (odds ratio (OR), 1.753; 95% CI, 1.055-2.912; P<0.05), quartile 3 (OR, 2.463; 95% CI, 1.445-4.917; P<0.01), and quartile 4 (OR, 5.867; 95% CI, 2.075-16.589; P<0.01). Receiver-operating characteristic analysis revealed that the optimal cutoff point of serum CysC to indicate DPN was 1.25 mg/l in male patients and 1.05 mg/l in female patients. High serum CysC level indicated a onefold higher risk of DPN.
Conclusions:
High serum CysC level is closely associated with DPN and may be a potential biomarker for DPN in type 2 diabetic patients.
More Related Videos
 08:15
Author Spotlight: Network Pharmacology and Molecular Docking to Decipher the Action of Jiawei Shengjiang San Against Diabetic Kidney Disease
Published on: May 10, 2024
 11:29
Corneal Confocal Microscopy: A Novel Non-invasive Technique to Quantify Small Fibre Pathology in Peripheral Neuropathies
Published on: January 3, 2011
Related Concept Videos
 01:28
Diabetic Nephropathy
 01:22
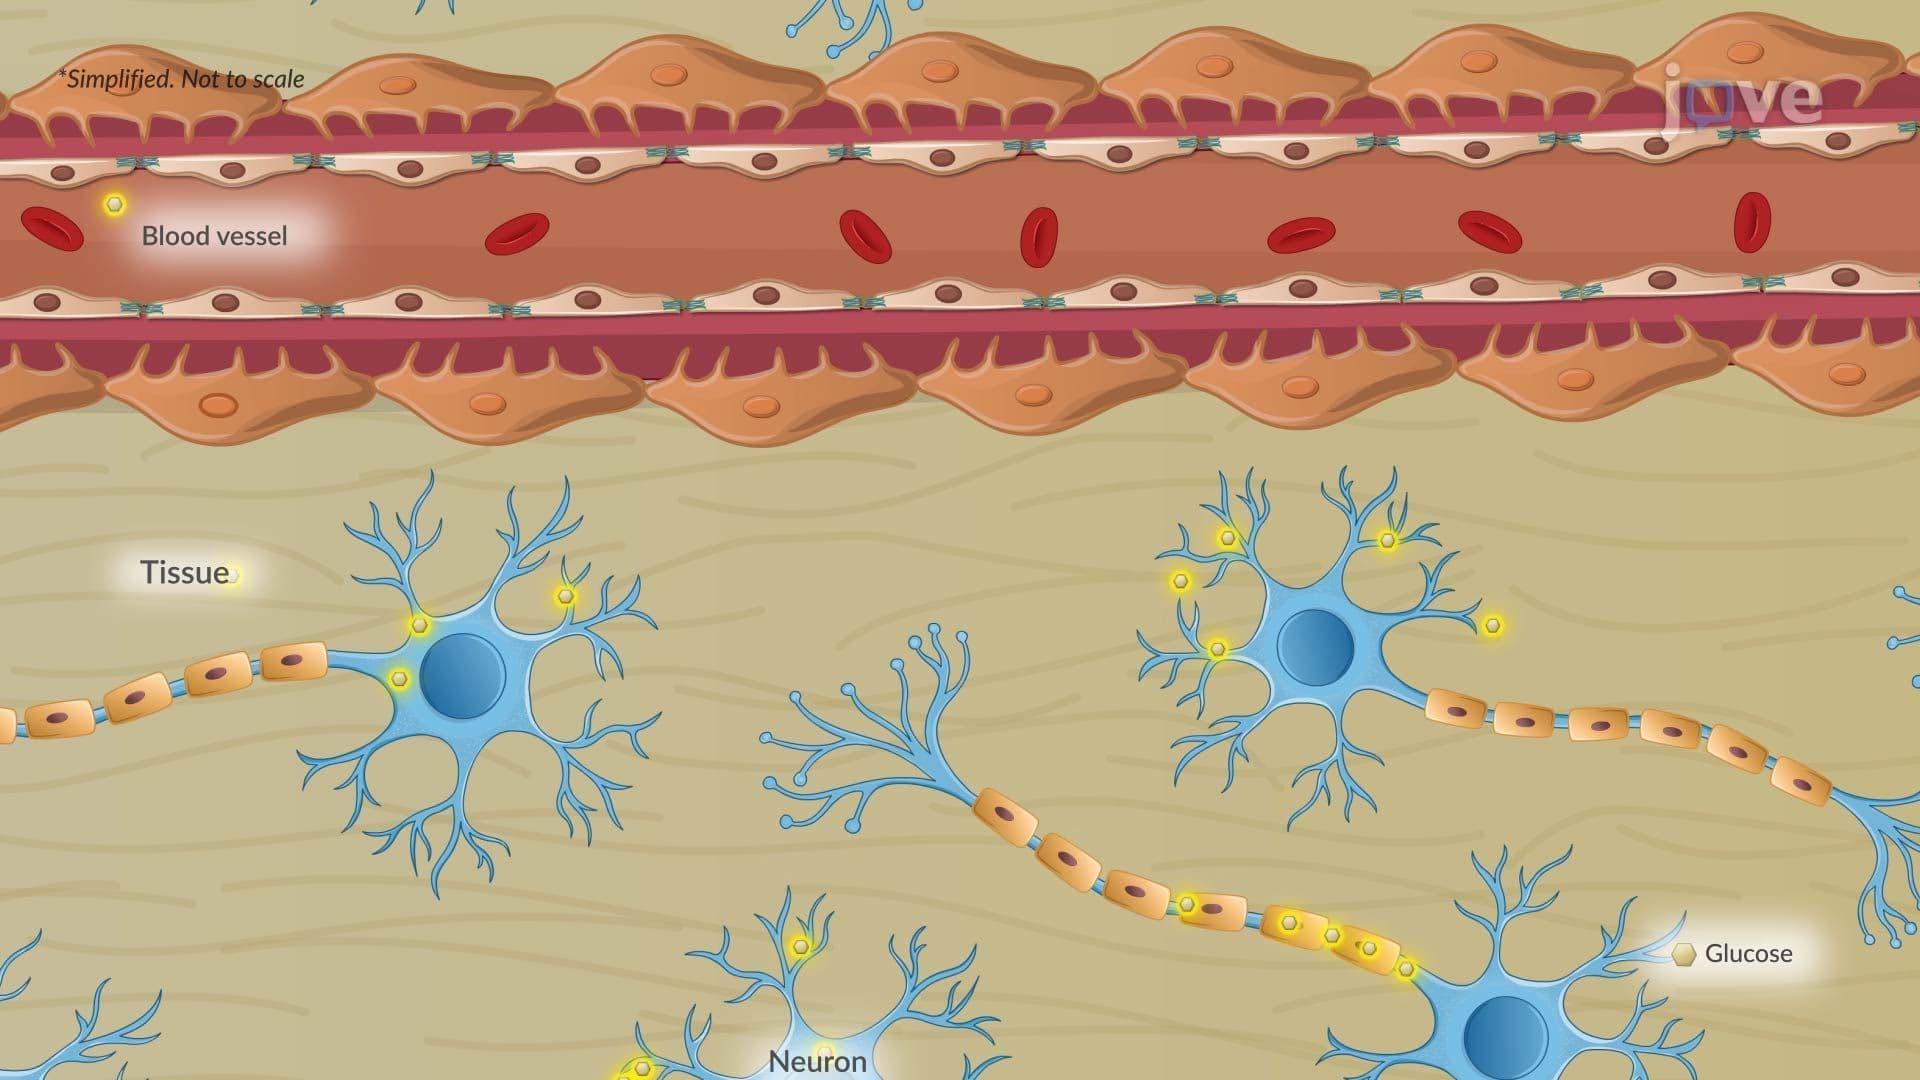
Diabetic Neuropathy
 01:25
Type II Diabetes Mellitus III: Clinical Manifestations and Diagnosis
 01:27
Diabetic Retinopathy
 01:24
Type II Diabetes II: Pathophysiology
 01:26
Type II Diabetes I: Introduction