High-frequency chest wall oscillation in prolonged mechanical ventilation patients: a randomized controlled trial
Related Experiment Video
Updated: Apr 24, 2026
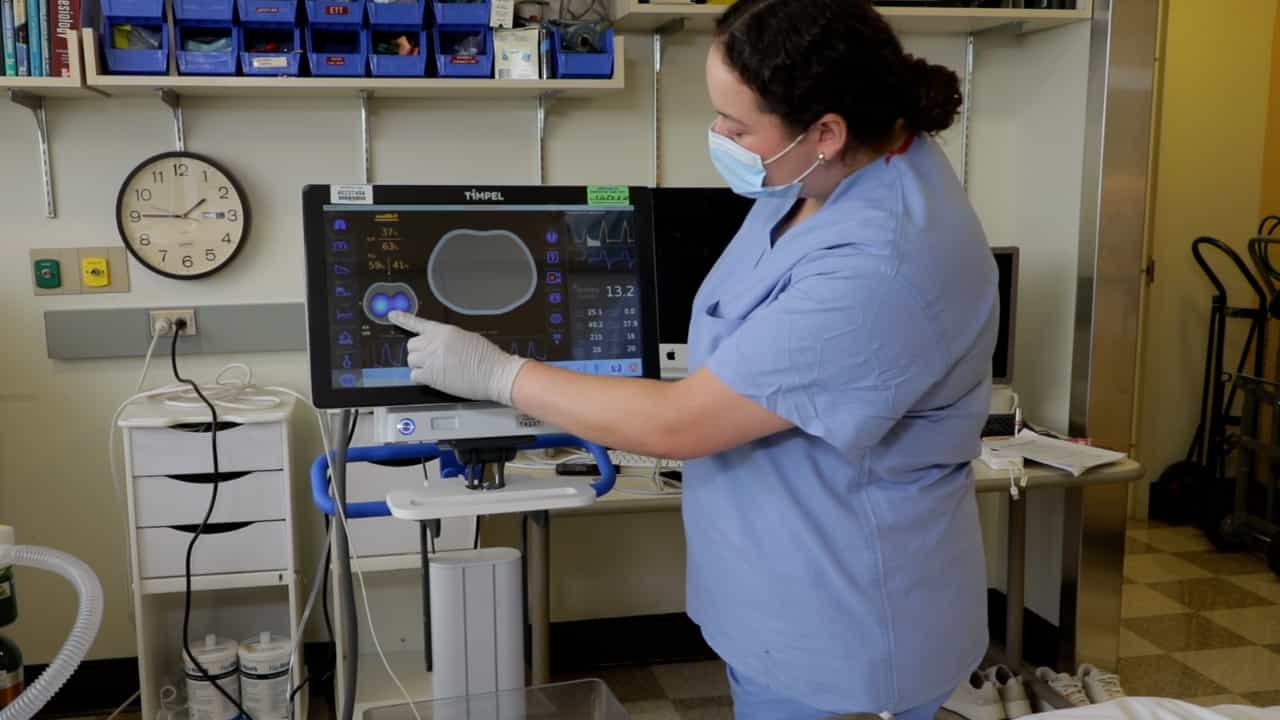
Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Wei-Chang Huang1,2, Pi-Chu Wu3, Chao-Jung Chen3
1Division of Respiratory and Critical Care Medicine, Department of Internal Medicine, Taichung Veterans General Hospital, Taichung, Taiwan.

Background And Aims:
Patients with prolonged mechanical ventilation (PMV) often retain airway secretions, which may be cleared with the assistance of high-frequency chest wall oscillation (HFCWO). This study aimed to determine the effectiveness, safety and tolerance/comfort of HFCWO after extubation in PMV patients.
Methods:
This parallel-designed, randomized controlled trial enrolled subjects with both intra-tracheal intubation and mechanical ventilator support continuously for at least 21 days between January 2011 and December 2012. Upon extubation, the participants were randomly assigned to either receive HFCWO for 5 days or not. The effectiveness [based on weaning success rates, daily clearance volume of sputum, serial changes in sputum coloration and chest X-ray (CXR) improvement rates], safety (by physiologic parameters) and tolerance/comfort [using the Modified Borg Scale (MBS) and Hamilton Anxiety Scale (HAS)] of HFCWO were investigated.
Results:
There were 43 PMV subjects, including 23 in the HFCWO group and 20 in the non-HFCWO group. The weaning success rates were 82.6% (19/23) and 85% (17/20) in the HFCWO and non-HFCWO groups, respectively (P = 1.000). The HFCWO group had persistently greater numbers of daily sputum suctions and higher CXR improvement rates compared with the non-HFCWO group. There was significant sputum coloration lightening in the HFCWO group only. There was no significant difference in the MBS and HAS between the two groups and between pre- and post-HFCWO physiologic parameters.
Conclusion:
In PMV patients, HFCWO was safe, comfortable and effective in facilitating airway hygiene after removal of endotracheal tubes, but had no positive impact on weaning success.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:30
Acute Respiratory Failure-III