Related Experiment Video
Updated: Apr 24, 2026
Assessment of Antibody-based Drugs Effects on Murine Bone Marrow and Peritoneal Macrophage Activation
Published on: December 26, 2017
Intravenous and subcutaneous immunoglobulin replacement: a two-way road. Optimizing healthcare quality in patients
Pere Soler-Palacín1, Ingrid Gasó-Gago, Aurora Fernández-Polo
1Pediatric Infectious Diseases and Immunodeficiencies Unit, Hospital Universitari Vall d'Hebron. Institut de Recerca Vall d'Hebron. Universitat Autònoma de Barcelona, Passeig de la Vall d'Hebron, 119-129, 08035, Barcelona, Spain, psoler@vhebron.net.

Purpose:
To evaluate the alternate use of subcutaneous immunoglobulin (SCIG) and intravenous immunoglobulin (IVIG) in patients with primary immunodeficiencies (PID) in a third-level Pediatric University Hospital.
Methods:
Retrospective study of all patients receiving SCIG from 2006 to 2012. Data collected included demographics, date SCIG was started, date of switch to IVIG and reasons, administration tolerance, and related adverse events. Effectiveness was defined as the lack of severe infections.
Results:
Twenty-three patients (15 male, 8 female) with PID were studied. SCIG was initiated at a median age of 14.2 years (8.4 months-25.7 years) and median duration on SCIG treatment was 41 months (4-68). Nine patients (39.1%) temporarily switched from SCIG to IVIG for the following reasons: vacation (8), administration issues (1), and transient need for immunomodulatory therapy (1). A mean of 5.2 IVIG infusions/patient (SD=2.86) was administered while on SCIG. IVIG-related adverse events were documented in 3 patients with 6 infusions. Eight (34.8%) patients definitively discontinued SCIG use for the following reasons: convenience (5), adverse effects (1), coagulopathy (1), and autoimmune thrombocytopenia (1). There were no severe infections requiring hospital admission in any patient during the study period.
Conclusions:
Alternating SCIG and IVIG use in patients with PID was associated with considerable advantages in terms of convenience for the patients and their caregivers, while maintaining the effectiveness and safety of this therapy. Healthcare units treating these patients should show flexibility with this dual therapy in order to optimize patients' quality of life.
Related Concept Videos
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency...
 01:36
Humoral Immune Responses
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:29
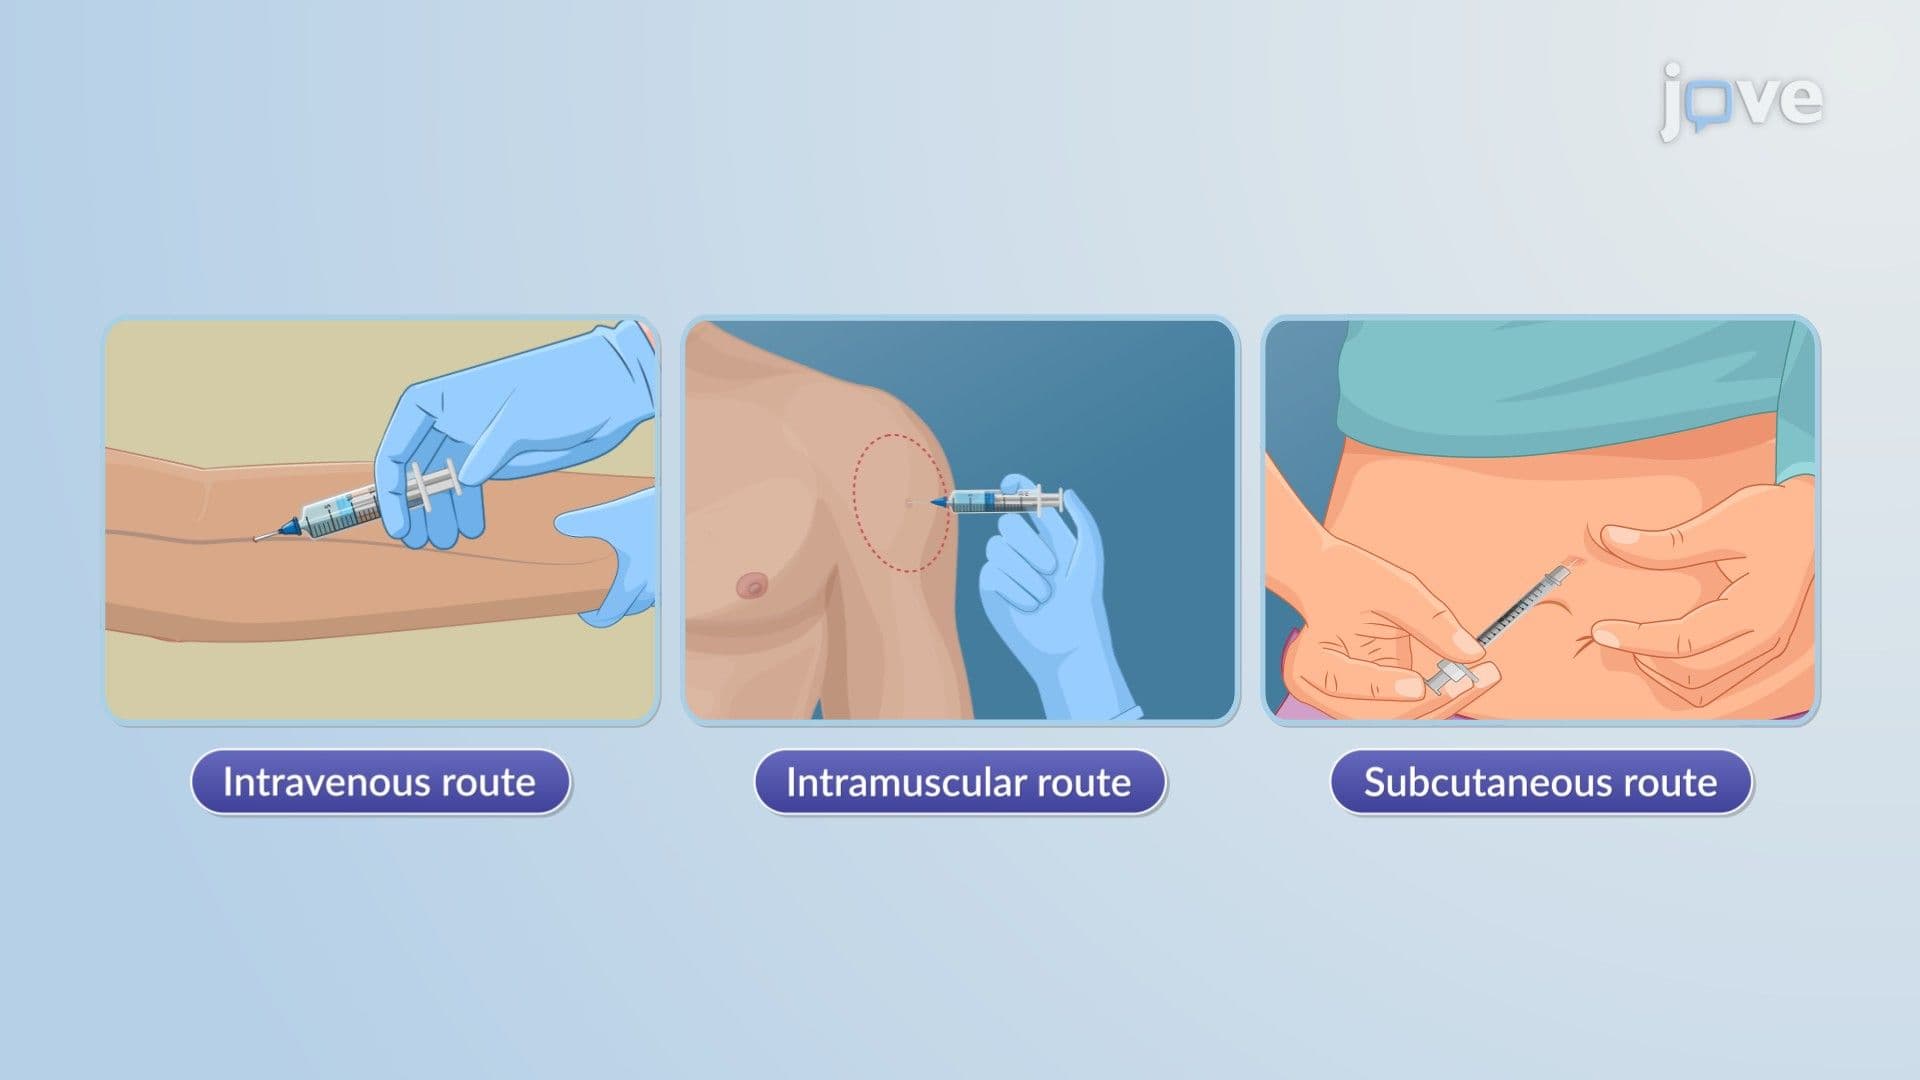
Drug Delivery: Parenteral Route
There are three primary parenteral routes: intravenous (IV), intramuscular (IM), and subcutaneous (SC). The IV route introduces the drug directly into the bloodstream, ensuring immediate action. The IM route...
 01:23
Immunological Memory
What is Immunological Memory?
Immunological memory is an integral function of the immune system that allows it to recognize and react more rapidly and effectively to pathogens previously encountered. This feature...
 01:28
Parenteral Drug Delivery Systems: Injectables, Implants, and Infusion Devices