Related Experiment Video
Updated: Apr 24, 2026
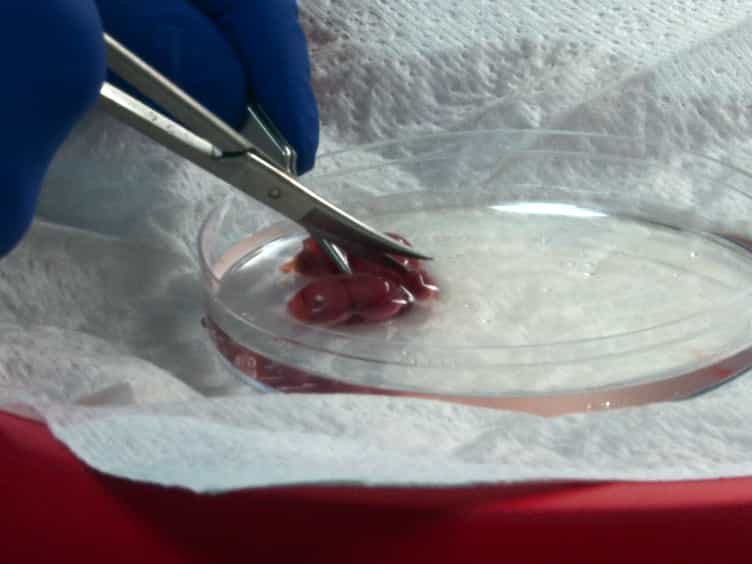

Method of Studying Palatal Fusion using Static Organ Culture
Published on: September 19, 2015
Barriers to care for children with orofacial clefts in North Carolina
Cynthia H Cassell1, Paula Strassle, Dara D Mendez
1National Center on Birth Defects and Developmental Disabilities, Centers for Disease Control and Prevention, Atlanta, Georgia.

Background:
Little is known about the barriers faced by families of children with birth defects in obtaining healthcare. We examined reported perceived barriers to care and satisfaction with care among mothers of children with orofacial clefts.
Methods:
In 2006, a validated barriers to care mail/phone survey was administered in North Carolina to all resident mothers of children with orofacial clefts born between 2001 and 2004. Potential participants were identified using the North Carolina Birth Defects Monitoring Program, an active, state-wide, population-based birth defects registry. Five barriers to care subscales were examined: pragmatics, skills, marginalization, expectations, and knowledge/beliefs. Descriptive and bivariate analyses were conducted using chi-square and Fisher's exact tests. Results were stratified by cleft type and presence of other birth defects.
Results:
Of 475 eligible participants, 51.6% (n = 245) responded. The six most commonly reported perceived barriers to care were all part of the pragmatics subscale: having to take time off work (45.3%); long waits in the waiting rooms (37.6%); taking care of household responsibilities (29.7%); meeting other family members' needs (29.5%); waiting too many days for appointments (27.0%); and cost (25.0%). Most respondents (72.3%, 175/242) felt "very satisfied" with their child's cleft care.
Conclusion:
Although most participants reported being satisfied with their child's care, many perceived barriers to care were identified. Due to the limited understanding and paucity of research on barriers to care for children with birth defects, including orofacial clefts, additional research on barriers to care and factors associated with them are needed.

Related Concept Videos
 01:21
Barriers to Effective Communication II
Cultural barriers:
Differences in values, beliefs, religion, knowledge, and tradition can significantly impact communication. Awareness of nonverbal cues is critical, especially when conversing with a patient from a different culture. What appears appropriate in one culture may be inappropriate in another.
Semantic barriers:
As a result of their tendency to use...
 01:17
Ethical Dilemmas I
Let us explore some examples to understand the potentially complex moral decisions nurses face.
Take the case of caring for minors, particularly in areas related to reproductive...
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...
 01:22
Standards of Care I
 01:30
Barriers to Effective Communication I
Communication barriers include the following:
Physiological barriers: They are limitations caused by a person's health condition or disability, such as hearing loss, poor eyesight, illness, or unconsciousness. An example to overcome this...
 01:30
Specialized Care Centers and Settings-I
Daycare centers
They provide several functions. Some facilities care for healthy newborns and children whose parents work, while others are medically focused and care for...