Related Experiment Video
Updated: Apr 24, 2026
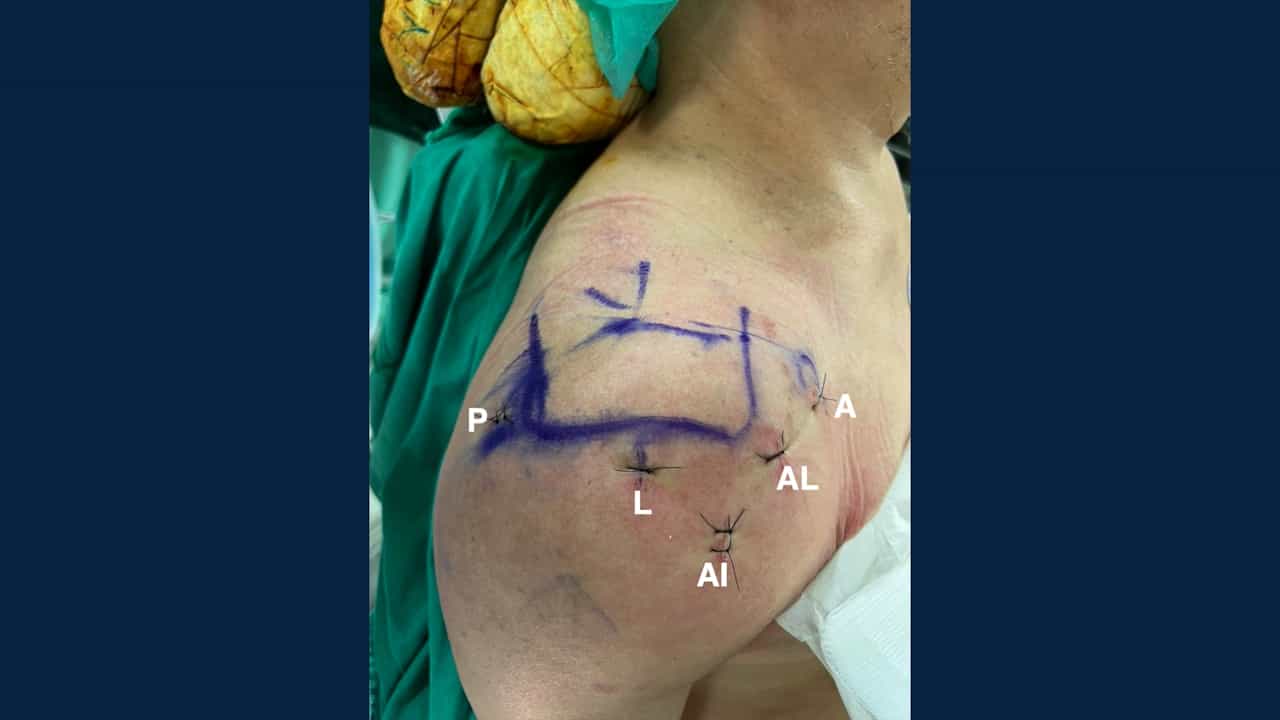
Knotless Independent Double-Row Repair and Biceps Augmentation for Anterosuperior Rotator Cuff Tears
Published on: January 23, 2026
Arthroscopic suprapectoral and open subpectoral biceps tenodesis: a comparison of minimum 2-year clinical outcomes
Brian C Werner1, Cody L Evans1, Russel E Holzgrefe1
1Department of Orthopaedic Surgery, University of Virginia Health System, Charlottesville, Virginia, USA.

Background:
While a vast body of literature exists describing biceps tenodesis techniques and evaluating the biomechanical aspects of tenodesis locations or various implants, little literature presents useful clinical outcomes to guide surgeons in their decision to perform a particular method of tenodesis.
Purpose/Hypothesis:
To compare the clinical outcomes of open subpectoral biceps tenodesis (OSPBT) and arthroscopic suprapectoral biceps tenodesis (ASPBT). Our null hypothesis was that both methods would yield satisfactory results with regard to shoulder and biceps function, postoperative shoulder scores, pain relief, and complications.
Study Design:
Cohort study; Level of evidence, 3.
Methods:
Patients who underwent either ASPBT or OSPBT for isolated superior labrum or long head of the biceps lesions with a minimum follow-up of 2 years were evaluated with several validated clinical outcome measures and physical examinations including range of motion and strength.
Results:
Between 2007 and 2011, a total of 82 patients met all inclusion and exclusion criteria, which included 32 patients with ASPBT and 50 patients with OSPBT; 27 of 32 (84.4%) patients with ASPBT and 35 of 50 (70.0%) patients with OSPBT completed clinical follow-up. Overall outcomes for both procedures were satisfactory. No significant differences were noted in postoperative Constant-Murley (ASPBT: 90.7; OSPBT: 91.8; P = .755), American Shoulder and Elbow Surgeons (ASPBT: 90.1; OSPBT: 88.4; P = .735), Single Assessment Numeric Evaluation (ASPBT: 87.4; OSPBT: 86.8; P = .901), Simple Shoulder Test (ASPBT: 10.4; OSPBT: 10.6; P = .762), long head of the biceps (ASPBT: 91.6; OSPBT: 93.6; P = .481), or Veterans RAND 36-Item Health Survey (ASPBT: 81.0; OSPBT: 80.1; P = .789) scores. No significant range of motion or strength differences was noted between the procedures.
Conclusion:
Both ASPBT and OSPBT yield excellent clinical and functional results for the management of isolated superior labrum or long head of the biceps lesions. No significant differences in clinical outcomes as determined by several validated outcome measures were found between the 2 tenodesis methods, nor were any significant range of motion or strength deficits noted at a minimum 2 years postoperatively.
More Related Videos
 07:10
Modified Long Head of Biceps Tendon Rerouting and Fixation as Partial Capsular Reconstruction for Massive Irreparable Rotator Cuff Tears
Published on: March 6, 2026
 07:22
Arthroscopic Management of Massive Irreparable Rotator Cuff Tears: Whole Rotator Cable Reconstruction Using Proximal Biceps Tendon Autograft
Published on: June 6, 2025