Related Experiment Video
Updated: Apr 24, 2026
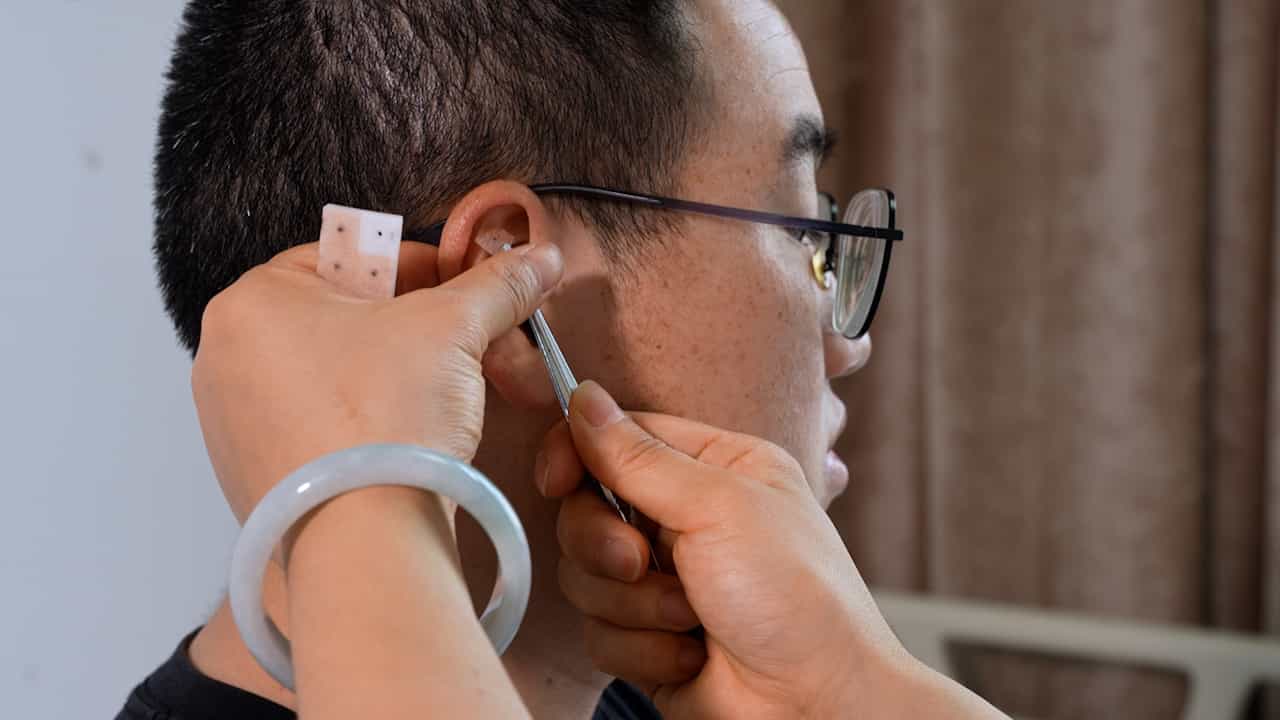
Author Spotlight: Efficacy of Auricular Pressure Bean Therapy in Reducing Wheezing Symptoms
Published on: May 10, 2024
Intermittent montelukast in children aged 10 months to 5 years with wheeze (WAIT trial): a multicentre, randomised,
Chinedu Nwokoro1, Hitesh Pandya2, Stephen Turner3
1Asthma UK Centre for Applied Research, Queen Mary University of London, London, UK.

Insights
Intermittent montelukast did not significantly reduce wheezing episodes in young children. However, a specific genotype (5/5 ALOX5 promoter) may indicate a subgroup that benefits from montelukast treatment.
Area of Science:
- Pediatric respiratory medicine
- Pharmacogenetics
- Clinical trial methodology
Background:
- Effectiveness of intermittent montelukast for wheeze in young children is not well-established.
- Response to montelukast in adults is influenced by ALOX5 gene promoter genotypes.
- Genotype stratification was used to explore differential treatment effects.
Purpose of the Study:
- To assess if intermittent montelukast is more effective than placebo for treating wheeze in children aged 10 months to 5 years.
- To investigate the role of ALOX5 promoter genotypes in modifying montelukast response.
- To evaluate the impact of treatment on unscheduled medical attendances for wheezing.
Main Methods:
- Multicentre, parallel-group, randomised, placebo-controlled trial.
- 1358 children (10 months–5 years) with wheeze were randomly assigned to montelukast or placebo.
- Stratification by ALOX5 promoter genotype (5/5 vs 5/x+x/x) and intention-to-treat analysis.
Main Results:
- No significant difference in unscheduled medical attendances for wheezing between montelukast and placebo groups (IRR 0.88, p=0.06).
- A significant reduction in attendances was observed in the montelukast group within the 5/5 ALOX5 genotype stratum (IRR 0.80, p=0.01).
- No significant benefit was seen in the 5/x+x/x genotype stratum (IRR 1.03, p=0.79).
Conclusions:
- Intermittent montelukast shows no clear overall benefit for young children with wheeze.
- The 5/5 ALOX5 promoter genotype may identify a subgroup of children who respond positively to montelukast.
- Further research into genotype-guided therapy for childhood wheeze is warranted.
Background:
The effectiveness of intermittent montelukast for wheeze in young children is unclear. We aimed to assess whether intermittent montelukast is better than placebo for treatment of wheeze in this age group. Because copy numbers of the Sp1-binding motif in the arachidonate 5-lipoxygenase (ALOX5) gene promoter (either 5/5, 5/x, or x/x, where x does not equal 5) modifies response to montelukast in adults, we stratified by this genotype.
Methods:
We did this multicentre, parallel-group, randomised, placebo-controlled trial between Oct 1, 2010, and Dec 20, 2013, at 21 primary care sites and 41 secondary care sites in England and Scotland. Children aged 10 months to 5 years with two or more wheeze episodes were allocated to either a 5/5 or 5/x+x/x ALOX5 promoter genotype stratum, then randomly assigned (1:1) via a permuted block schedule (size ten), to receive intermittent montelukast or placebo given by parents at each wheeze episode over a 12 month period. Clinical investigators and parents were masked to treatment group and genotype strata. The primary outcome was number of unscheduled medical attendances for wheezing episodes. Analysis was by intention to treat. This trial is registered with ClinicalTrials.gov, number NCT01142505.
Findings:
We randomly assigned 1358 children to receive montelukast (n=669) or placebo (n=677). Consent was withdrawn for 12 (1%) children. Primary outcome data were available for 1308 (96%) children. There was no difference in unscheduled medical attendances for wheezing episodes between children in the montelukast and placebo groups (mean 2·0 [SD 2·6] vs 2·3 [2·7]; incidence rate ratio [IRR] 0·88, 95% CI: 0·77-1·01; p=0·06). Compared with placebo, unscheduled medical attendances for wheezing episodes were reduced in children given montelukast in the 5/5 stratum (2·0 [2·7] vs 2·4 [3·0]; IRR 0·80, 95% CI 0·68-0·95; p=0·01), but not in those in the 5/x+x/x stratum (2·0 [2·5] vs 2·0 [2·3]; 1·03, 0·83-1·29; p=0·79, pinteraction=0·08). We recorded one serious adverse event, which was a skin reaction in a child allocated to placebo.
Interpretation:
Our findings show no clear benefit of intermittent montelukast in young children with wheeze. However, the 5/5 ALOX5 promoter genotype might identify a montelukast-responsive subgroup.
Funding:
Medical Research Council (UK) and National Institute for Health Research.

Related Concept Videos
 01:19
Antiasthma Drugs: Leukotriene Modifiers
Leukotriene modifiers work through two distinct mechanisms:
 01:25
Antiasthma Drugs: Mast Cell Stabilizers and Anti-IgE Drugs
Mast cell stabilizers, such as cromolyn (also known as sodium cromoglycate) and nedocromil (Tilade), are effective drugs in asthma management. These stabilizers hinder histamine release by skillfully obstructing the activation of mast cells and other cellular entities. Notably, they navigate this task without...
 01:30
Asthma-IV: Diagnostic and Management
Clinical Assessment for Asthma:
This is the first step in diagnosing and managing asthma. It includes:
 01:13
Asthma III: Clinical Manifestations
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.
 01:30
Asthma-IV: Nursing Management
First, in...