Related Experiment Video
Updated: Apr 23, 2026
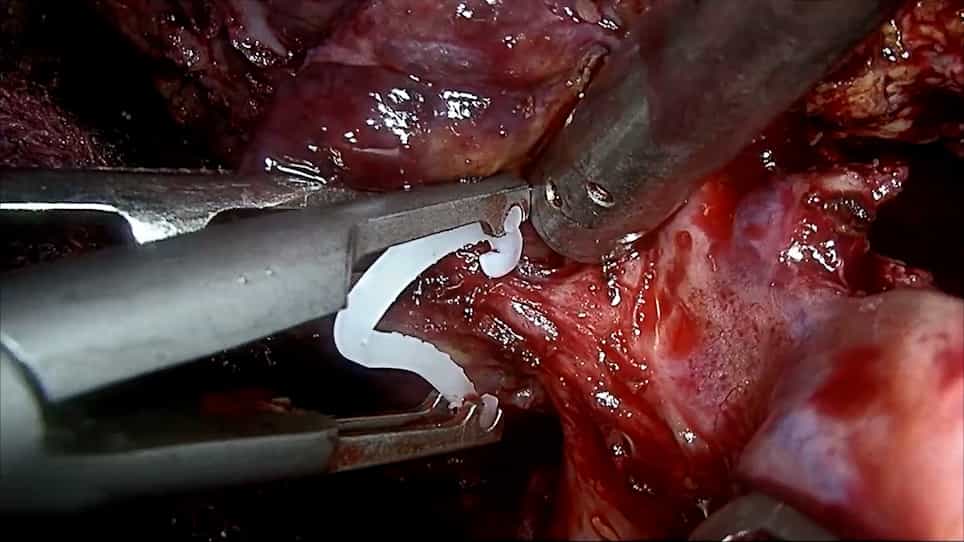

Modified Laparoscopic Anatomic Hepatectomy: Two-Surgeon Technique Combined with the Simple Extracorporeal Pringle Maneuver
Published on: June 16, 2023
Modified Pringle maneuver for laparoscopic liver resection
Takeo Nomi1, David Fuks, Aditya Agrawal
1Department of Digestive Disease, Institut Mutualiste Montsouris, Paris, France.

Background:
The Pringle maneuver is widely used in liver surgery to reduce intraoperative blood loss. However, total vascular inflow occlusion is frequently associated with ischemia reperfusion injury leading to postoperative liver dysfunction and impaired recovery. We describe herein an original procedure of modified Pringle maneuver (MPM) during laparoscopic liver resection with selective clamping of hepatic arterial inflow.
Methods:
Of 183 laparoscopic major hepatectomies performed at the Institute Mutualiste Montsouris between January 1998 and March 2014, 19 patients required vascular clamping, and MPM was used in 6 patients. The video showed this procedure in a 58-year-old woman with multiple colorectal liver metastases planned for laparoscopic right trisectionectomy. After the division of the right hepatic artery and the right portal vein, the parenchymal transection was performed with 12 mm Hg of pneumoperitoneum pressure using MPM in order to control the bleeding.
Results:
The total operative time was 187 min and estimated blood loss was 70 ml. A right trisectionectomy were performed successfully with a purely laparoscopic procedure. After an uneventful postoperative recovery, the patient was discharged on the fifth postoperative day. Among 6 patients in whom this technique was applied, only one patient experienced grade II postoperative liver failure according to Clavien-Dindo classification.
Conclusions:
Selective clamping of hepatic arterial inflow may be a preferred surgical strategy for high-risk patients, with elective application of this maneuver preemptively in all cases where excessive bleeding is anticipated.
Insights
A modified Pringle maneuver selectively clamps hepatic arterial inflow during laparoscopic liver surgery, reducing blood loss and improving recovery. This technique offers a safer alternative for high-risk patients anticipating significant bleeding.
Area of Science:
- Hepatobiliary Surgery
- Minimally Invasive Surgery
- Surgical Innovation
Background:
- The Pringle maneuver is standard for reducing blood loss in liver surgery but can cause ischemia reperfusion injury.
- Laparoscopic liver resection aims to minimize invasiveness, but controlling bleeding remains a challenge.
Observation:
- A modified Pringle maneuver (MPM) selectively clamps hepatic arterial inflow during laparoscopic liver resection.
- This technique was applied in 6 patients undergoing major hepatectomies, including a right trisectionectomy for colorectal liver metastases.
Findings:
- The modified Pringle maneuver resulted in minimal blood loss (70 ml) and a short operative time (187 min) in a case study.
- Postoperative recovery was uneventful for the described patient, discharged on the fifth day.
- Only one of six patients experienced grade II postoperative liver failure using this method.
Implications:
- Selective hepatic arterial inflow clamping may be a preferred strategy for high-risk liver surgery patients.
- This modified Pringle maneuver can be proactively used when excessive bleeding is anticipated.
- It potentially reduces ischemia reperfusion injury and improves outcomes in laparoscopic liver resections.