Effects of dosage, comorbidities, and food on isoniazid pharmacokinetics in Peruvian tuberculosis patients
Related Experiment Video
Updated: Apr 23, 2026
Validated LC-MS/MS Panel for Quantifying 11 Drug-Resistant TB Medications in Small Hair Samples
Published on: May 19, 2020
Ana Requena-Méndez1, Geraint Davies2, David Waterhouse3
1Laboratorio de Investigación de Enfermedades Infecciosas, Universidad Peruana Cayetano Heredia, Lima, Peru Barcelona Centre for International Health Research, CRESIB, Hospital Clinic-Universitat de Barcelona, Barcelona, Spain ana.requena@cresib.cat.

Abstract:
Poor response to tuberculosis (TB) therapy might be attributable to subtherapeutic levels in drug-compliant patients. Pharmacokinetic (PK) parameters can be affected by several factors, such as comorbidities or the interaction of TB drugs with food. This study aimed to determine the PK of isoniazid (INH) in a Peruvian TB population under observed daily and twice-weekly (i.e., biweekly) therapy. Isoniazid levels were analyzed at 2 and 6 h after drug intake using liquid chromatography mass spectrometric methods. A total of 107 recruited patients had available PK data; of these 107 patients, 42.1% received biweekly isoniazid. The mean biweekly dose (12.8 mg/kg of body weight/day) was significantly lower than the nominal dose of 15 mg/kg/day (P < 0.001), and this effect was particularly marked in patients with concurrent diabetes and in males. The median maximum plasma concentration (Cmax) and area under the concentration-time curve from 0 to 6 h (AUC0-6) were 2.77 mg/liter and 9.71 mg · h/liter, respectively, for daily administration and 8.74 mg/liter and 37.8 mg · h/liter, respectively, for biweekly administration. There were no differences in the Cmax with respect to gender, diabetes mellitus (DM) status, or HIV status. Food was weakly associated with lower levels of isoniazid during the continuation phase. Overall, 34% of patients during the intensive phase and 33.3% during the continuation phase did not reach the Cmax reference value. However, low levels of INH were not associated with poorer clinical outcomes. In our population, INH exposure was affected by weight-adjusted dose and by food, but comorbidities did not indicate any effect on PK. We were unable to demonstrate a clear relationship between the Cmax and treatment outcome in this data set. Twice-weekly weight-adjusted dosing of INH appears to be quite robust with respect to important potentially influential patient factors under program conditions.

Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the...
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment
 01:26
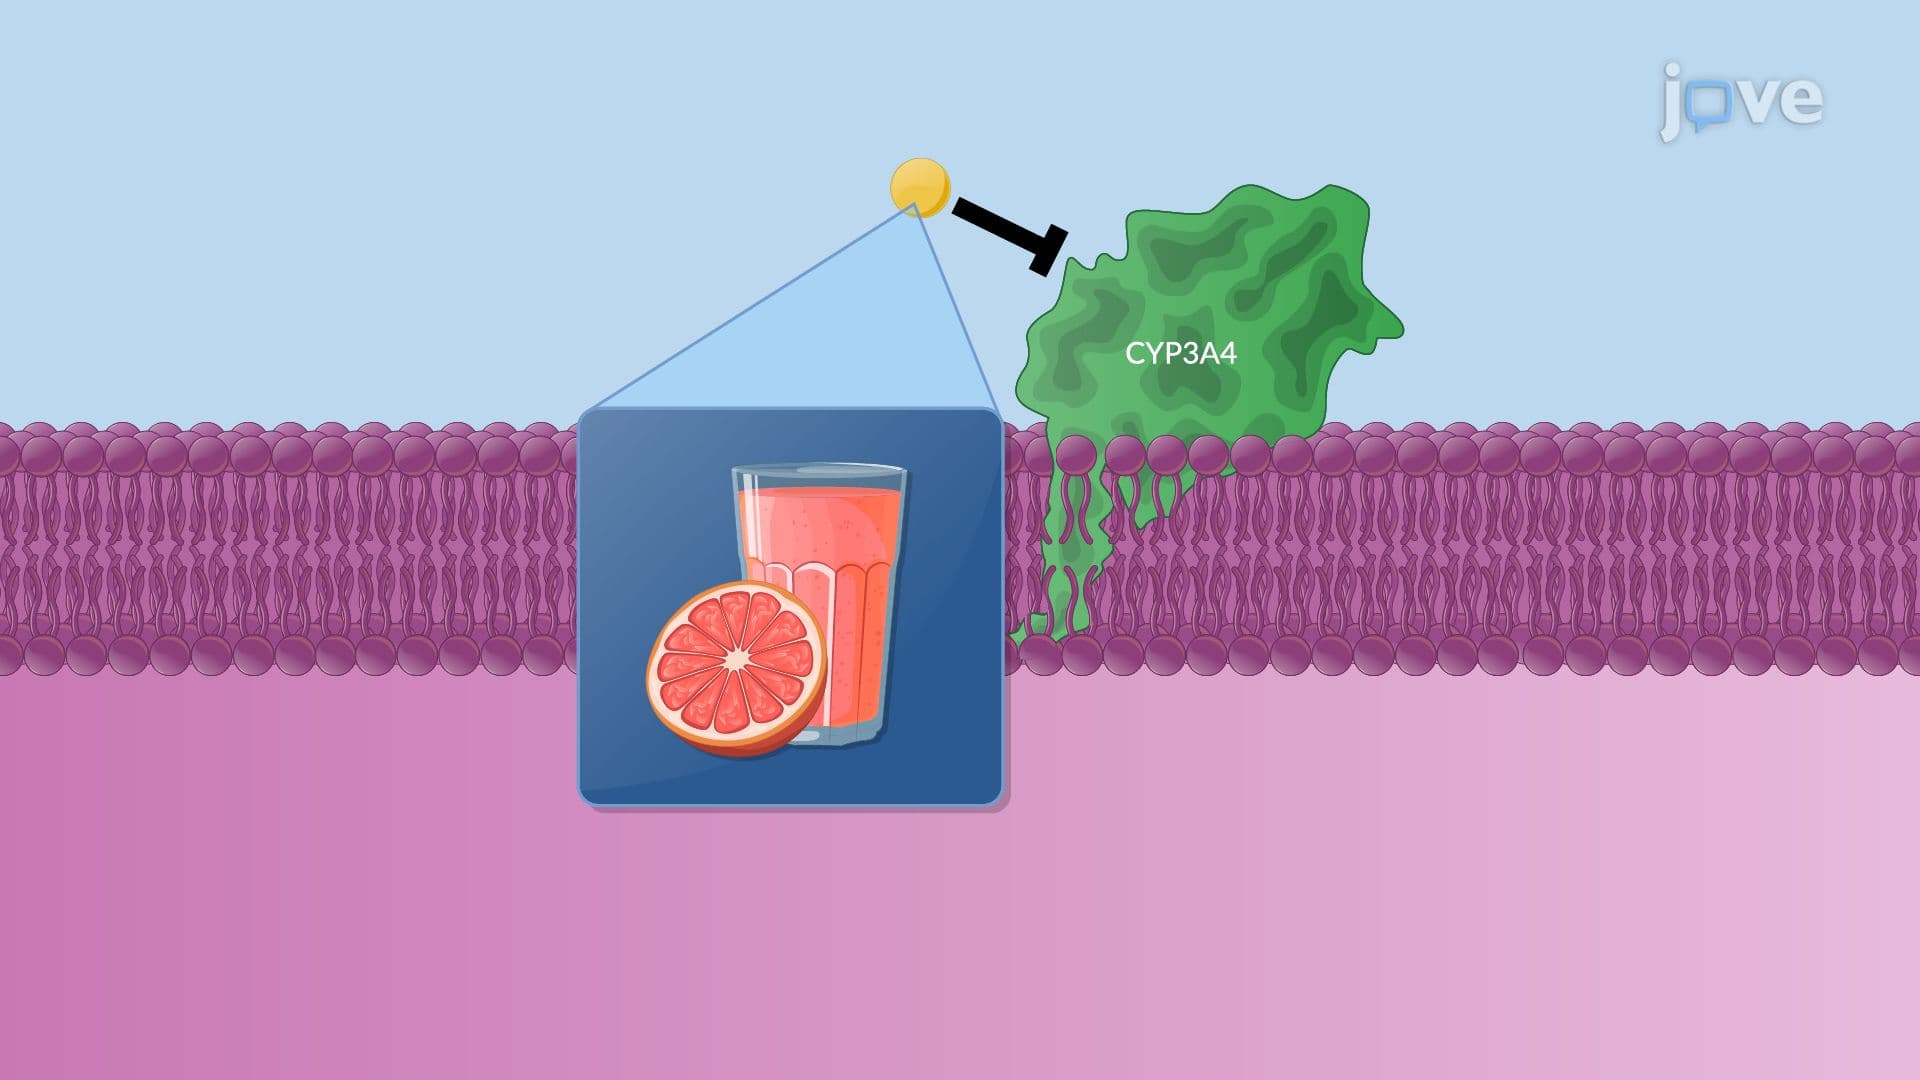
Pharmacokinetics: Drug–Food and Drug–Viral Interactions
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:01
Dosage Regimens: Partial Pharmacokinetic Parameters
 01:16
Drug toxicity: Idiosyncratic Reactions