Related Experiment Video
Updated: Apr 23, 2026
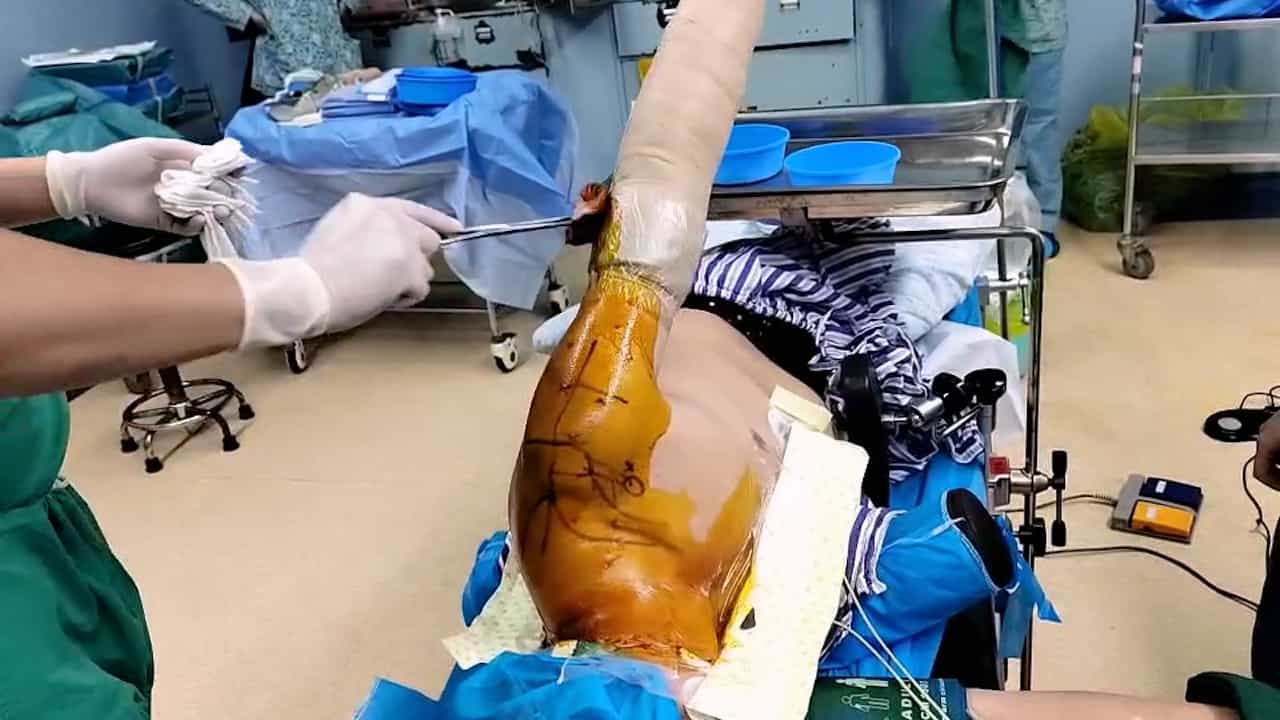

Arthroscopic Management of Massive Irreparable Rotator Cuff Tears: Whole Rotator Cable Reconstruction Using Proximal Biceps Tendon Autograft
Published on: June 6, 2025
Arthroscopic versus open comparison of long head of biceps tendon visualization and pathology in patients requiring
Brian B Gilmer1, Ariana M DeMers2, Dolores Guerrero3
1Taos Orthopaedic Institute, Taos, New Mexico, U.S.A..

Purpose:
The purpose of this study was to compare arthroscopic versus open examination of the proximal long head of the biceps tendon (LHB) in patients undergoing open, subpectoral tenodesis.
Methods:
Eighty consecutive patients were prospectively enrolled, of whom 62 were included in the study. During arthroscopy, the most distal extent of the LHB visualized was marked with a Bovie device. The tendon was pulled into the joint with an arthroscopic grasper, showing additional LHB and was again marked with the device. LHB fraying, flattening, redness, and degeneration were graded as absent, mild, moderate, or severe. During open subpectoral tenodesis, the grossly visualized LHB was graded in the same manner and the locations of both marks plus the total length of the LHB observed during open visualization were measured and recorded. After subpectoral tenodesis, the excised portion of the LHB was histologically graded as normal, fibrosis/tendinosis, or inflamed.
Results:
On average, during open tenodesis, 95 mm (range, 75 to 130 mm) of LHB was visualized. This was greater than the length visualized during diagnostic arthroscopy of 16 mm (range, 5 to 28 mm), or 17%, and the length visualized while pulling the tendon into the joint with an arthroscopic grasper of 30 mm (range, 15 to 45 mm), or 32%. The difference in LHB length observed during open versus arthroscopic examination with a grasper was statistically significant (P < .0001). In addition, when compared with LHB pathology observed in an open manner, arthroscopic visualization showed only 67% of pathology, underestimated noted pathology in 56% of patients, and overestimated noted pathology in 11% of patients. Histologic evaluation showed fibrosis/tendinosis in 100% of cases but inflammation in only 5%.
Conclusions:
When compared with open inspection during subpectoral tenodesis, arthroscopic examination of the LHB visualizes only 32% of the tendon and may underestimate pathology.
Level Of Evidence:
Level II, diagnostic study-development of diagnostic criteria based on consecutive patients with universally applied gold standard.
More Related Videos
 07:10
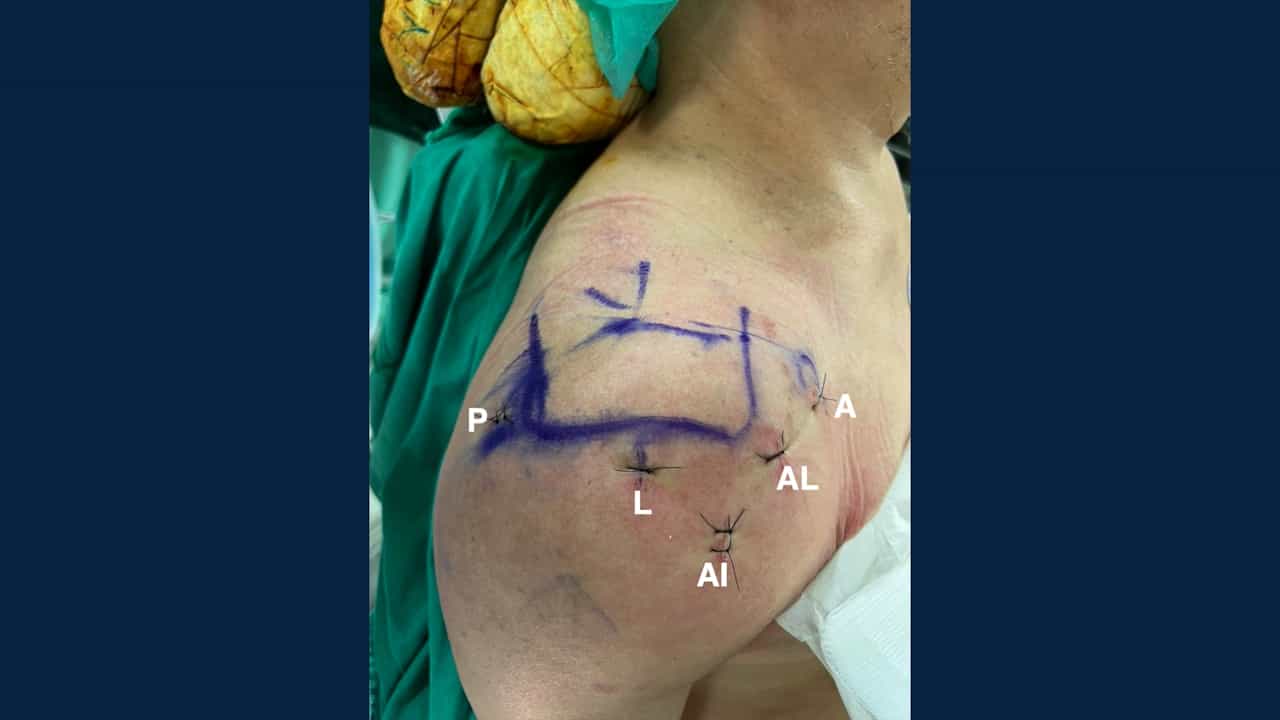
Modified Long Head of Biceps Tendon Rerouting and Fixation as Partial Capsular Reconstruction for Massive Irreparable Rotator Cuff Tears
Published on: March 6, 2026
 05:25
Knotless Independent Double-Row Repair and Biceps Augmentation for Anterosuperior Rotator Cuff Tears
Published on: January 23, 2026