Related Experiment Video
Updated: Apr 22, 2026


A Method to Study the C924T Polymorphism of the Thromboxane A2 Receptor Gene
Published on: April 1, 2019
Association of common polymorphisms in β1-adrenergic receptor with antihypertensive response to carvedilol
Dayong Si1, Juan Wang, Ying Xu
1*School of Life Science, Jilin University, Changchun, China; †Key-Lab for Evolution of Past Life and Environment in Northeast Asia, Ministry of Education, Jilin University, Changchun, China; ‡Division of Nephrology, The First Hospital of Jilin University, Changchun, China; and §Department of Cardiology, China-Japan Union Hospital of Jilin University, Changchun, China.

Insights
Genetic variations in the beta-1 adrenergic receptor (ADRB1) significantly impact carvedilol
Area of Science:
- Pharmacogenomics
- Cardiovascular Medicine
- Genetics
Background:
- Interpatient variability in blood pressure response to carvedilol is significant.
- Carvedilol is a nonselective beta-blocker used for hypertension.
- Adrenergic receptor gene polymorphisms may influence drug efficacy.
Purpose of the Study:
- To investigate the impact of common beta-adrenergic receptor gene polymorphisms on the antihypertensive efficacy of carvedilol.
- To evaluate the role of ADRB1 and ADRB2 gene variants in carvedilol response.
Main Methods:
- A double-blind monotherapy study involving 87 essential hypertensive patients from China.
- Blood pressures were measured before and after 7 days of carvedilol treatment (10 mg/d).
- Genotyping for ADRB1 (Ser49Gly, Arg389Gly) and ADRB2 (Gly16Arg, Glu27Gln) polymorphisms using PCR-RFLP.
Main Results:
- Patients homozygous for ADRB1 Arg389 showed a significantly greater reduction in diastolic blood pressure (DBP) compared to ADRB1 Gly389 homozygotes (10.61 vs. 2.62 mm Hg, P=0.013).
- ADRB1 haplotypes predicted response; Gly49Arg389/Ser49Arg389 haplotype pairs demonstrated a 5.7-fold greater DBP reduction than Ser49Gly389 homozygotes (16.11 vs. 2.83 mm Hg, P=0.0055).
- No association was found between ADRB2 polymorphisms and carvedilol response.
Conclusions:
- ADRB1 polymorphisms are important determinants of diastolic blood pressure response to carvedilol in essential hypertension.
- This study provides evidence for the pharmacogenetic influence of ADRB1 on carvedilol efficacy.
- ADRB2 polymorphisms do not appear to influence carvedilol's antihypertensive effect.
Objectives:
Marked interpatient variability exists in the blood pressure response to carvedilol, a nonselective β-blocker. Here we evaluated the influence of 4 common polymorphisms in genes of the β-adrenergic receptor on the antihypertensive efficacy of carvedilol in patients in a double-blinded monotherapy study.
Methods:
Eighty-seven subjects with uncomplicated essential hypertensive (49% men; age = 52.2 ± 11.1 years) from Jilin province of China were enrolled in the study, and 5 of them discontinued the treatment due to adverse effects. Both systolic and diastolic blood pressures (DBPs) were measured before and after 7 days of treatment with carvedilol (10 mg/d). Genotypes of the β1-adrenergic receptor (ADRB1 Ser49Gly and Arg389Gly) and β2-adrenergic receptor (ADRB2 Gly16Arg and Glu27Gln) were determined by polymerase chain reaction with restriction fragment length polymorphism.
Results:
Patients homozygous for ADRB1 Arg389 had an approximately 4-fold greater reduction in DBPs than those homozygous for ADRB1 Gly389 (10.61 vs. 2.62 mm Hg, P = 0.013). The ADRB1 haplotype was also a significant predictor of response, as patients with the Gly49Arg389/Ser49Arg389 haplotype pair had a 5.7-fold greater reduction in DBPs than those homozygous for the Ser49Gly389 haplotype (16.11 vs. 2.83 mm Hg, P = 0.0055). An association was not found between ADRB2 polymorphism and carvedilol responsiveness in antihypertensive therapy.
Conclusions:
This study provides the first evidence to support that ADRB1 polymorphisms play an important role in the DBPs response to carvedilol treatment in patients with essential hypertension.
Related Concept Videos
 01:11
Pharmacogenetics of Drug Targets: β₂-Adrenergic Receptors, Apo E, Thymidylate Synthase
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:17
Antihypertensive Drugs: Action of β1 Blockers
 01:22
Heart Failure Drugs: β-Blockers
 01:26
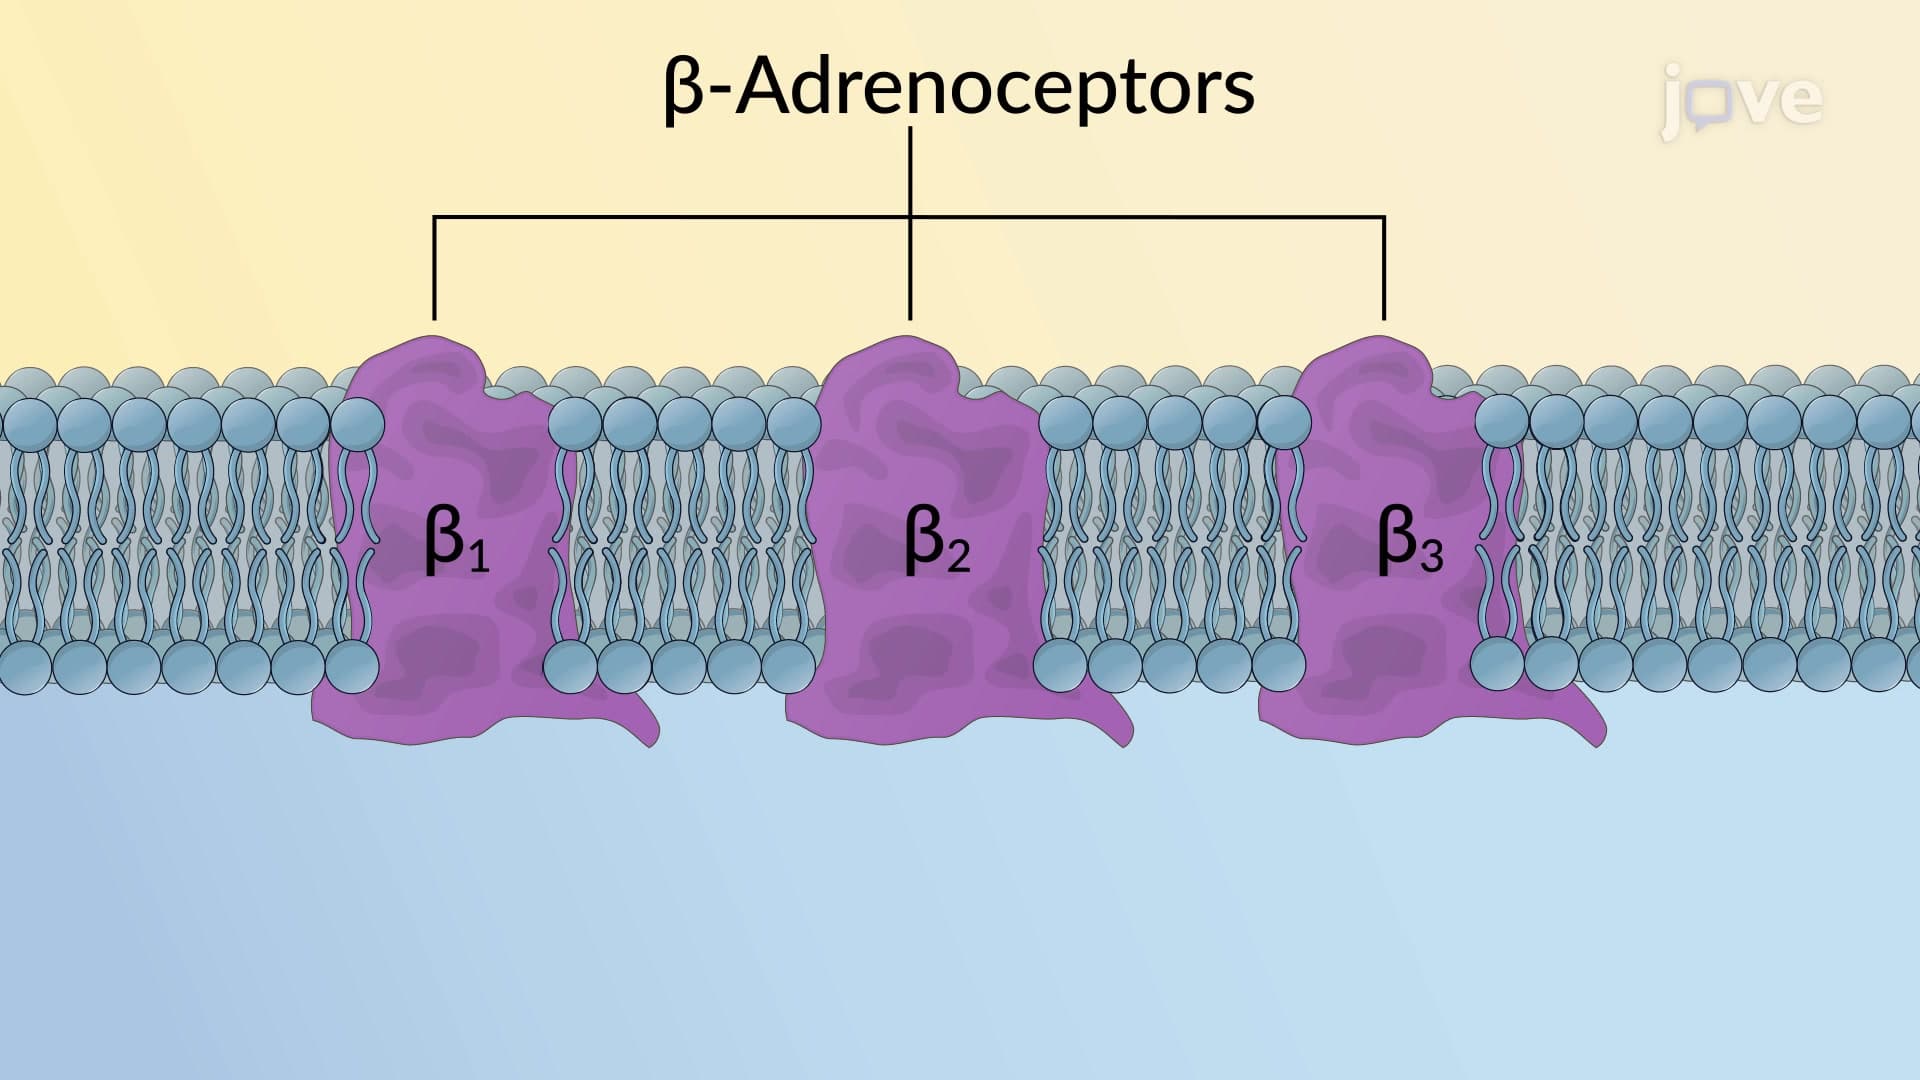
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...
 01:28
Antihypertensive Drugs: Types of β-Blockers