Related Experiment Video
Updated: Jul 15, 2026
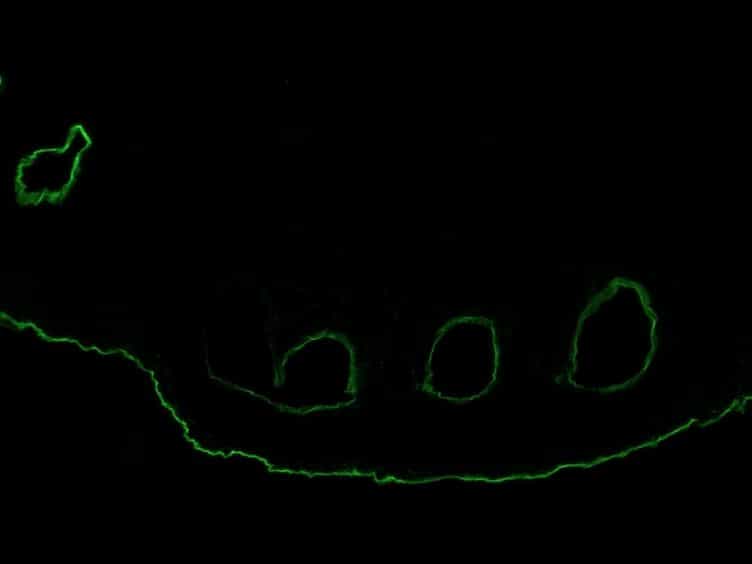

Granulocyte-dependent Autoantibody-induced Skin Blistering
Published on: October 12, 2012
The uses of intravenous immune globulin in collagen vascular disorders

Studies in our laboratory demonstrated that the long-term administration of intravenous immune serum globulin in patients with common variable hypogammaglobulinemia produced increased suppressor activity, which resulted in diminished in vitro B cell immunoglobulin synthesis. These studies suggested that intravenous immune globulin therapy might be a useful modality in altering immunoregulation in patients with collagen vascular autoimmune disease. In the present preliminary study, two groups of patients with collagen vascular disease were chosen: systemic lupus erythematosus and primary Sjögren's syndrome. Patients with systemic lupus erythematosus with mild clinical disease were chosen to minimize the risk of adverse effects on the disease process, particularly specific organ involvement (e.g., lupus nephritis). Each patient was used as his or her own clinical and laboratory control. Patients received 300 mg/kg of intravenous immune globulin every 4 weeks. As a whole the patient group did not experience any adverse effects from the intravenous immune globulin therapy. No clinical or laboratory changes were observed in one patient with systemic lupus erythematosus and one patient with Sjögren's syndrome. In the other patient with Sjögren's syndrome, there were subjective changes of improved well-being and increased energy levels without any objective changes in the sicca syndrome. There was a slight steroid-sparing effect (10 to 3 mg/day) but no effects on the sedimentation rate, the antinuclear antibody, or rheumatoid factor serologic studies. In a patient with steroid-dependent systemic lupus erythematosus, there was marked clinical improvement of the cutaneous vasculitis after the third infusion, with reduction in her oral steroid requirements from 25 to 7.5 mg/day.(ABSTRACT TRUNCATED AT 250 WORDS)
Studies in our laboratory demonstrated that the long-term administration of intravenous immune serum globulin in patients with common variable hypogammaglobulinemia produced increased suppressor activity, which resulted in diminished in vitro B cell immunoglobulin synthesis. These studies suggested that intravenous immune globulin therapy might be a useful modality in altering immunoregulation in patients with collagen vascular autoimmune disease. In the present preliminary study, two groups of patients with collagen vascular disease were chosen: systemic lupus erythematosus and primary Sjögren's syndrome. Patients with systemic lupus erythematosus with mild clinical disease were chosen to minimize the risk of adverse effects on the disease process, particularly specific organ involvement (e.g., lupus nephritis). Each patient was used as his or her own clinical and laboratory control. Patients received 300 mg/kg of intravenous immune globulin every 4 weeks. As a whole the patient group did not experience any adverse effects from the intravenous immune globulin therapy. No clinical or laboratory changes were observed in one patient with systemic lupus erythematosus and one patient with Sjögren's syndrome. In the other patient with Sjögren's syndrome, there were subjective changes of improved well-being and increased energy levels without any objective changes in the sicca syndrome. There was a slight steroid-sparing effect (10 to 3 mg/day) but no effects on the sedimentation rate, the antinuclear antibody, or rheumatoid factor serologic studies. In a patient with steroid-dependent systemic lupus erythematosus, there was marked clinical improvement of the cutaneous vasculitis after the third infusion, with reduction in her oral steroid requirements from 25 to 7.5 mg/day.(ABSTRACT TRUNCATED AT 250 WORDS)
Related Concept Videos
 01:11
Fibril-associated Collagen
For example, the type II collagen fibrils in cartilage have covalently bound type IX fibril-associated collagens at regular intervals. Other types of fibril-associated collagens are...
 01:05
Type IV Collagen of Basal Lamina
A type IV collagen molecule has six alpha chains which can exist in...
 01:29
Drugs for Treatment of Crohn's Disease in IBD Using Immunomodulatory Agents
 01:24
Drugs for Treatment of Crohn's Disease in IBD Using Biologic Agents: Anti-TNF
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management