Related Experiment Video
Updated: Apr 22, 2026
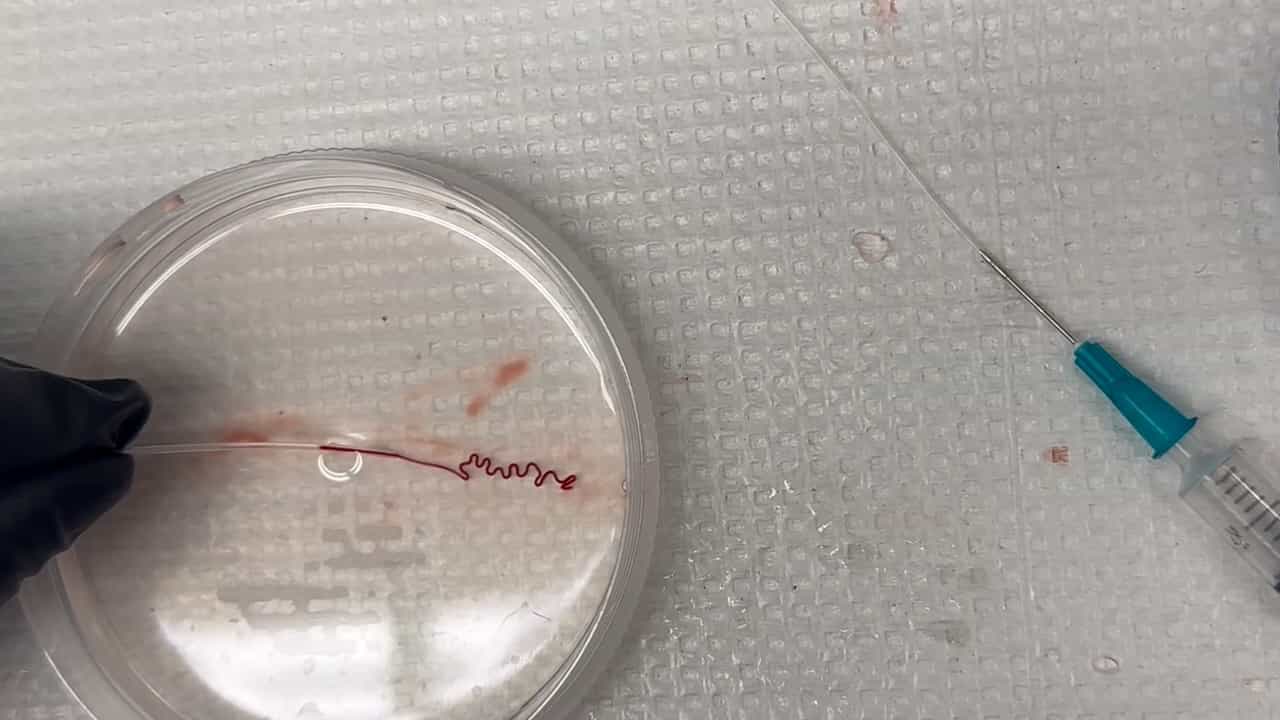

The Stroke Preclinical Assessment Network Multi-Laboratory Model of Thromboembolic Stroke with Thrombolysis: TE-MCAo
Published on: December 19, 2025
Derivation and external validation of a case mix model for the standardized reporting of 30-day stroke mortality
Benjamin D Bray1, James Campbell2, Geoffrey C Cloud2
1From the Division of Health and Social Care Research, King's College London, London, United Kingdom (B.D.B., C.D.A.W., A.G.R.); Clinical Effectiveness Unit, Royal College of Physicians, London, United Kingdom (J.C., A.H.); Stroke Unit, St George's NHS Trust, London, United Kingdom (G.C.C.); Stroke Unit, Royal Devon and Exeter NHS Foundation Trust, Exeter, United Kingdom (M.J.); Stroke Unit, Salford Royal NHS Foundation Trust, Salford, United Kingdom (P.J.T.); and National Institute for Health Research Comprehensive Biomedical Research Centre, Guy's and St Thomas' NHS Foundation Trust, London, United Kingdom (C.D.A.W., A.G.R.). benjamin.bray@kcl.ac.uk.

Background And Purpose:
Case mix adjustment is required to allow valid comparison of outcomes across care providers. However, there is a lack of externally validated models suitable for use in unselected stroke admissions. We therefore aimed to develop and externally validate prediction models to enable comparison of 30-day post-stroke mortality outcomes using routine clinical data.
Methods:
Models were derived (n=9000 patients) and internally validated (n=18 169 patients) using data from the Sentinel Stroke National Audit Program, the national register of acute stroke in England and Wales. External validation (n=1470 patients) was performed in the South London Stroke Register, a population-based longitudinal study. Models were fitted using general estimating equations. Discrimination and calibration were assessed using receiver operating characteristic curve analysis and correlation plots.
Results:
Two final models were derived. Model A included age (<60, 60-69, 70-79, 80-89, and ≥90 years), National Institutes of Health Stroke Severity Score (NIHSS) on admission, presence of atrial fibrillation on admission, and stroke type (ischemic versus primary intracerebral hemorrhage). Model B was similar but included only the consciousness component of the NIHSS in place of the full NIHSS. Both models showed excellent discrimination and calibration in internal and external validation. The c-statistics in external validation were 0.87 (95% confidence interval, 0.84-0.89) and 0.86 (95% confidence interval, 0.83-0.89) for models A and B, respectively.
Conclusions:
We have derived and externally validated 2 models to predict mortality in unselected patients with acute stroke using commonly collected clinical variables. In settings where the ability to record the full NIHSS on admission is limited, the level of consciousness component of the NIHSS provides a good approximation of the full NIHSS for mortality prediction.
