Related Experiment Video
Updated: Apr 22, 2026


Homogeneous Time-resolved Förster Resonance Energy Transfer-based Assay for Detection of Insulin Secretion
Published on: May 10, 2018
Genotype-based treatment of type 2 diabetes with an α2A-adrenergic receptor antagonist
Yunzhao Tang1, Annika S Axelsson2, Peter Spégel2
1Department of Clinical Sciences, Lund University, SE-20502 Malmö, Sweden. 2011 Collaborative Innovation Center of Tianjin for Medical Epigenetics (Ministry of Health), Key Laboratory of Hormones and Development, Metabolic Diseases Hospital & Tianjin Institute of Endocrinology, Tianjin Medical University, Tianjin 300070, China.

Abstract:
The feasibility of exploiting genomic information for individualized treatment of polygenic diseases remains uncertain. A genetic variant in ADRA2A, which encodes the α(2A)-adrenergic receptor (α(2A)AR), was recently associated with type 2 diabetes. This variant causes receptor overexpression and impaired insulin secretion; thus, we hypothesized that blocking α(2A)AR pharmacologically could improve insulin secretion in patients with the risk genotype. A total of 50 type 2 diabetes patients were recruited on the basis of ADRA2A genotype for a randomized placebo-controlled intervention study with the α(2A)AR antagonist yohimbine. The patients received 0, 10, or 20 mg of yohimbine at three separate visits. The primary endpoint was insulin secretion at 30 min (Ins30) during an oral glucose tolerance test (OGTT). Patients with the risk variant had 25% lower Ins30 than those without risk genotype. After administration of 20 mg of yohimbine, Ins30 was enhanced by 29% in the risk group, making secretion similar to patients carrying the low-risk allele. The corrected insulin response and disposition index in individuals with the high-risk (but not low-risk) allele were improved by 59 ± 18% and 43 ± 14%, respectively. The beneficial effect of yohimbine was not a consequence of improved insulin sensitivity. In summary, the data show that the insulin secretion defect in patients carrying the ADRA2A risk genotype can be corrected by α(2A)AR antagonism. The findings show that knowledge of genetic risk variants can be used to guide therapeutic interventions that directly target the underlying pathophysiology and demonstrate the potential of individualized genotype-specific treatment of type 2 diabetes.


Related Concept Videos
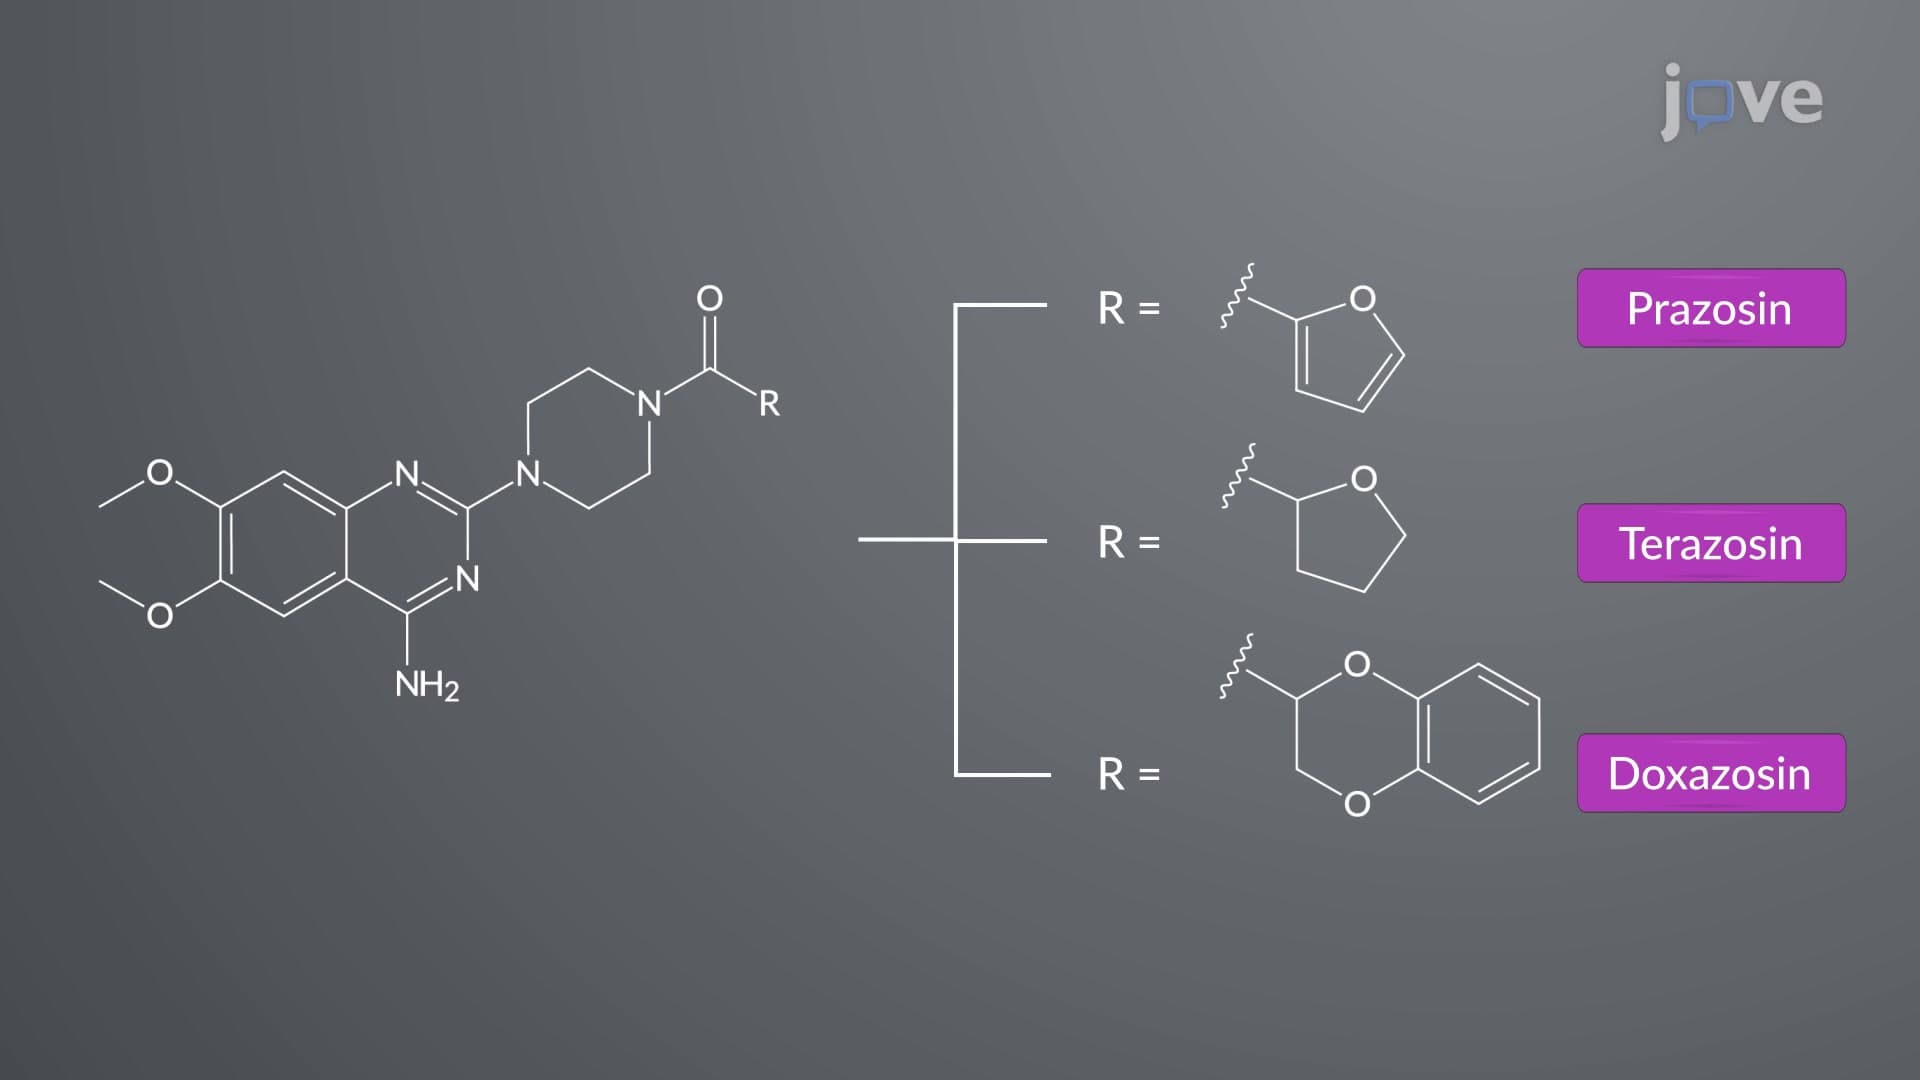 01:17
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline...
 01:26
Oral Hypoglycemic Agents: Biguanides and Glitazones
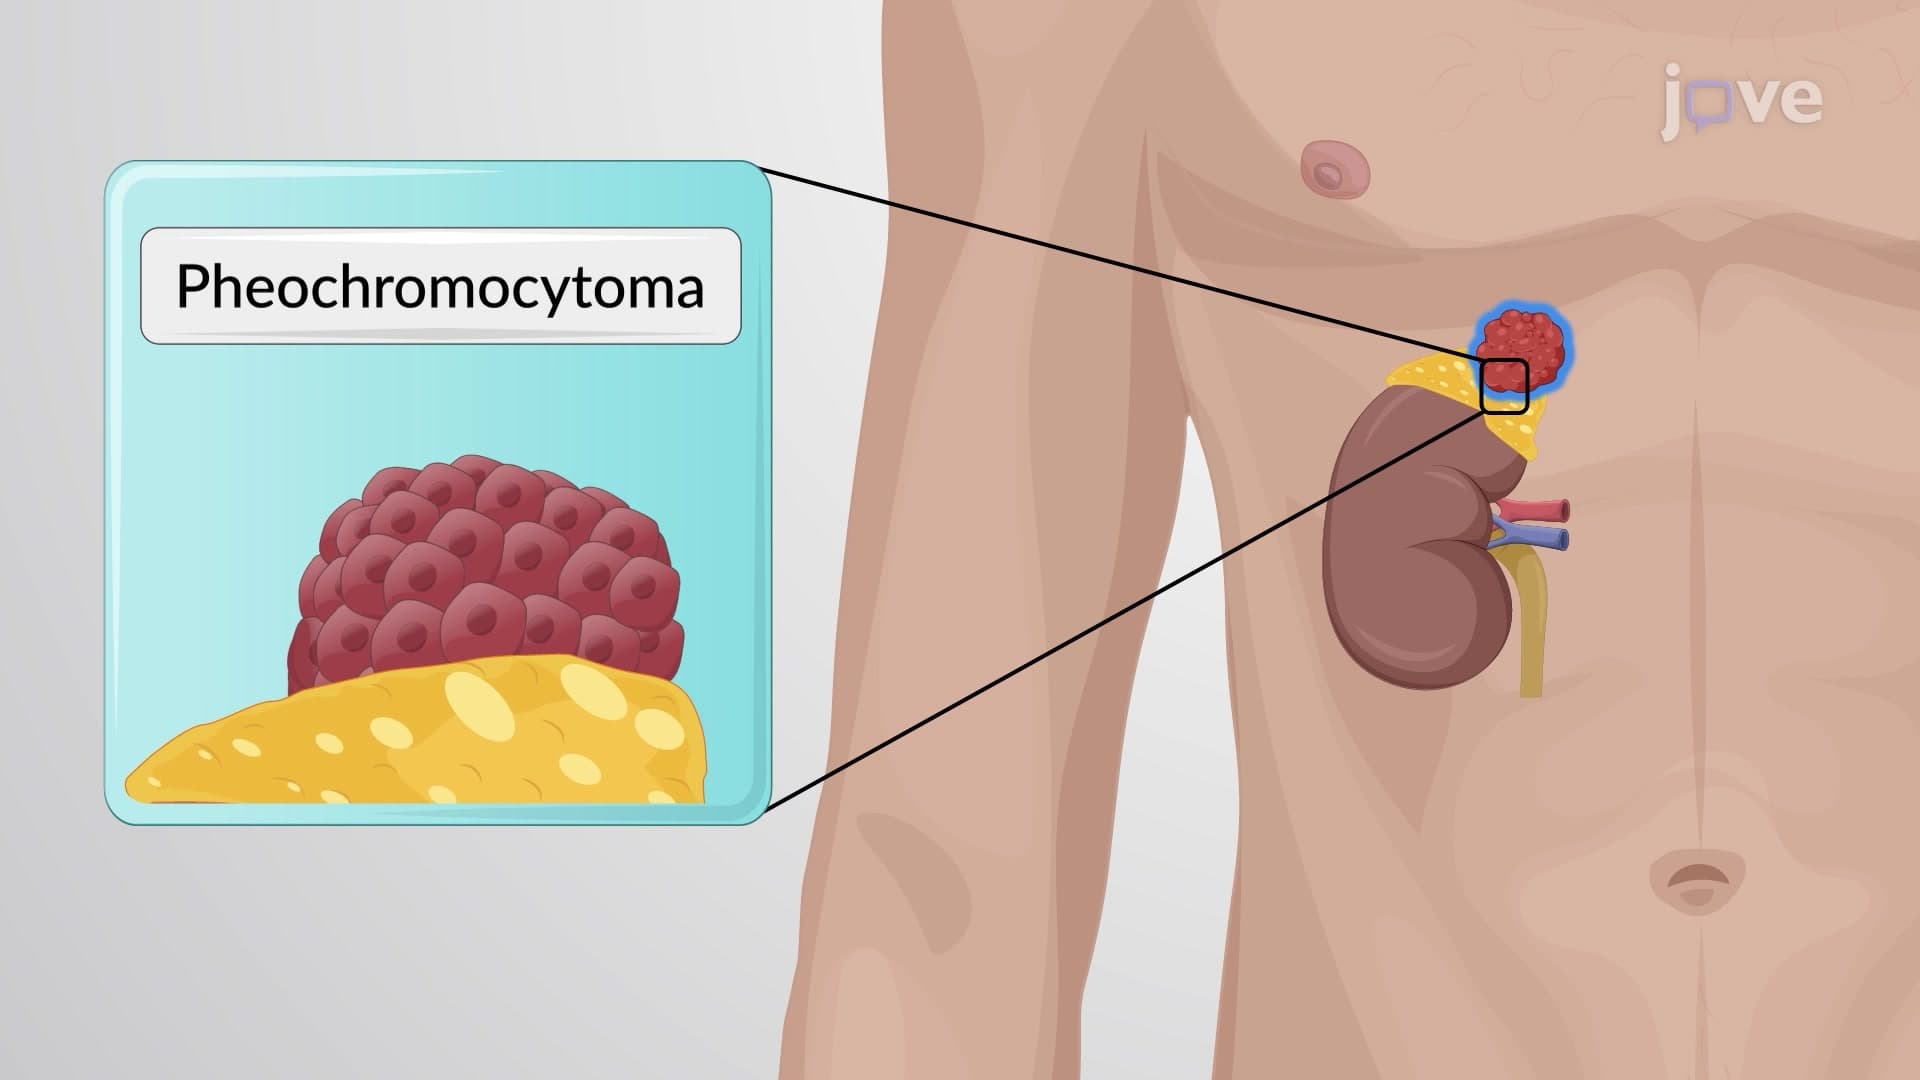 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...
 01:24
Glucagon-like Receptor Agonists
GLP-1, when administered in high doses intravenously, triggers insulin secretion, inhibits glucagon release, slows gastric emptying, reduces food intake, and restores normal insulin secretion. However, its rapid inactivation by...
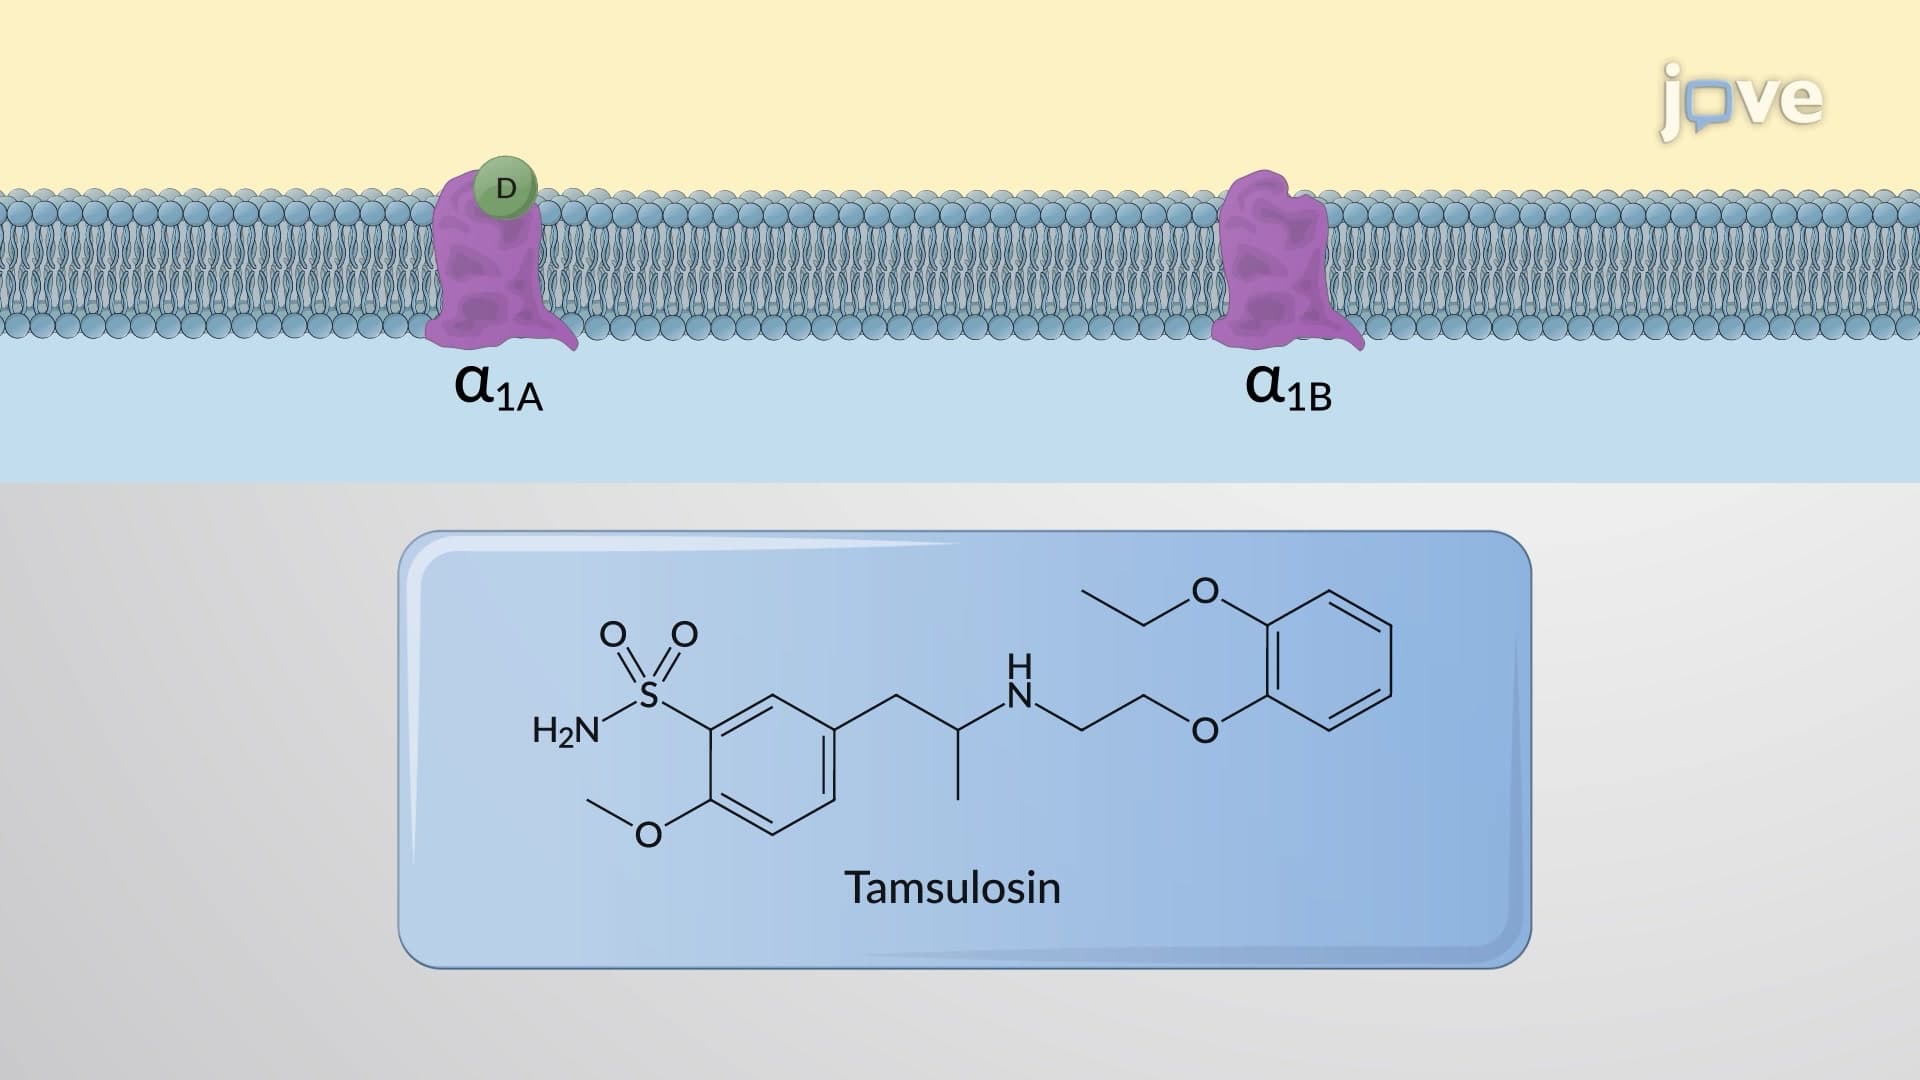 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
 01:15
Diabetes: Management and Pharmacotherapy
Insulin remains the cornerstone of treatment for most patients with type 1 and many...