Related Experiment Video
Updated: Apr 22, 2026
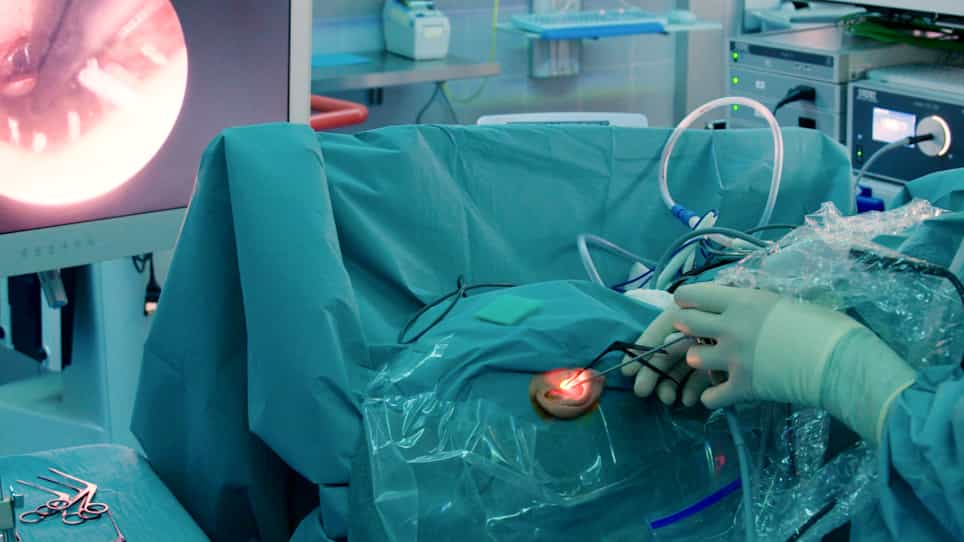

Endoscopic Cholesteatoma Surgery
Published on: January 19, 2022
Pediatric cholesteatoma surgery using a single-staged canal wall down approach: results of a 5-year longitudinal
Aaron Trinidade1, Andrew Skingsley, Matthew W Yung
1*Department of Otolaryngology, Ipswich General Hospital, Ipswich; and †Department of Medicine, Imperial College, London, United Kingdom.

Insights
This 5-year study on pediatric cholesteatoma surgery using the canal wall down (CWD) approach with obliteration found a low recurrence rate. The CWD technique with obliteration offers a safe and effective long-term solution for extensive cholesteatoma in children.
Area of Science:
- Otolaryngology
- Pediatric Surgery
- Surgical Innovation
Background:
- Cholesteatoma in children presents unique surgical challenges.
- The canal wall down (CWD) approach with obliteration is utilized for extensive cholesteatoma.
- Longitudinal data on this specific technique in pediatric populations is limited.
Purpose of the Study:
- To evaluate the 5-year outcomes of pediatric cholesteatoma surgery using a CWD approach with mastoid obliteration.
- To assess residual/recurrent cholesteatoma rates, postoperative hearing, ear waterproofing, and re-operation risks.
Main Methods:
- Prospective longitudinal study of children (<16 years) undergoing CWD surgery for cholesteatoma.
- Follow-up duration of 5 years, with analysis of residual/recurrent disease, otorrhea, waterproofing, and hearing.
- Kaplan-Meier survival analysis and cross-sectional analysis were employed.
Main Results:
- At 5 years, the residual cholesteatoma rate was 9.9%, with no recurrences detected.
- Postoperative otorrhea risk was 0%, and definitive waterproofing was achieved in 94.8% of cases.
- Hearing outcomes varied, with 62.5% maintaining hearing within 10 dB, and a 17.2% re-operation risk within 5 years.
Conclusions:
- The CWD approach with obliteration is effective for extensive pediatric cholesteatoma.
- This surgical technique leads to a low recurrence rate and a high rate of a 'trouble-free' ear long-term.
- The findings support the CWD approach with obliteration as a viable treatment option for extensive cholesteatoma in children.
Objective:
To present the results of a 5-year longitudinal study in a pediatric population undergoing surgery for extensive cholesteatoma using a canal wall down (CWD) approach with obliteration.
Study Design:
Prospective longitudinal study.
Patients:
Children (<16 years) undergoing surgery for cholesteatoma (58 ears) between 1999 and 2013.
Interventions:
Therapeutic.
Setting:
District general hospital.
Main Outcome Measures:
(1) Residual, recurrence, and recidivist cholesteatoma rates at 5 years post-surgery; (2) postoperative hearing; (3) postoperative waterproofing of the ear; (4) number of subsequent ear surgery required.
Results:
Fifty-five children (58 ears) contributed to the study. At 5 years, 16 of 58 (27.6%) had been lost to follow-up. Using Kaplan-Meier survival analysis, the residual rate after 5 years was 9.9% (95% CI: 3.8-24.4%), representing four residual cholesteatomas, and there were no recurrences detected. Using a cross-sectional analysis at 12 months of follow-up, the otorrhea risk was 0% and the risk of definitive waterproofing was 94.8%. There was a re-operation risk of 17.2% within 5 years which included second-stage ossiculoplasty. Regarding hearing, of the data available (n = 16), 10 children (62.5%) maintained their hearing (change between -10 and =10 dB), 2 (12.5%) had hearing gain (>10 dB), and 4 children (25%) had hearing reduction at 12 months postoperation. Four of 16 children (25%) had a postoperative hearing level of 30 dB or lower.
Conclusion:
The use of a CWD approach with obliteration of the mastoid cavity to surgically treat extensive cholesteatoma in children results in a low recurrence rate and high rate of a trouble-free ear in the long term.