
Levetiracetam pharmacokinetics in Japanese subjects with renal impairment
Junichi Yamamoto1, Nathalie Toublanc, Yuji Kumagai
1UCB Pharma, Shinjuku Grand Tower, 8-17-1 Nishi-Shinjuku, Shinjuku-ku, Tokyo, 160-0023, Japan, Junichi.Yamamoto@ucb.com.

Background And Objective:
The anti-epileptic drug levetiracetam is excreted renally. The objective of this trial was to evaluate the pharmacokinetics of levetiracetam in Japanese patients with renal impairment including end-stage renal disease (ESRD) to confirm that existing dosing instructions-based on data from European patients-are appropriate in a Japanese population.
Methods:
This was a nonrandomised, open-label trial. Six participants were allocated to each of five groups (normal renal function, mild, moderate and severe renal impairment and ESRD); 30 participants in total. Participants received a single dose of levetiracetam 500 mg (normal or mild), 250 mg (moderate or severe), or 500 mg followed by 250 mg post-haemodialysis (ESRD). Blood and urine samples were obtained serially for levetiracetam and metabolite determinations. Noncompartmental pharmacokinetic parameters were calculated and steady-state profiles were simulated using the superposition method.
Results:
In this trial, levetiracetam total clearance decreased proportionally with creatinine clearance: 52, 31, 25, 20 and 11 mL/min/1.73 m(2) in healthy controls and in patients with mild, moderate, severe renal impairment, and ESRD, respectively. Simulated levetiracetam plasma profiles using the recommended dose adjustments were within the range for normal renal function. Overall, results from this trial were consistent with historical European data.
Conclusion:
These findings confirm that the dosing instructions are appropriate for Japanese patients with renal impairment including ESRD.
More Related Videos
 09:02
A Large Animal Model for Acute Kidney Injury by Temporary Bilateral Renal Artery Occlusion
Published on: February 2, 2021
 08:28
Microsurgical Skills of Establishing Permanent Jugular Vein Cannulation in Rats for Serial Blood Sampling of Orally Administered Drug
Published on: December 14, 2021
Related Concept Videos
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:25
Drug Dosing in Renal Diseases: Measurement of Serum Creatinine Concentration and Clearance
 01:28
Drug Dosing in Renal Diseases: Estimation of Glomerular Filtration Rate Based on Serum Creatinine Concentration
 01:28
Renal Drug Excretion: Tubular Secretion
 01:15
Renal Drug Excretion: Overview
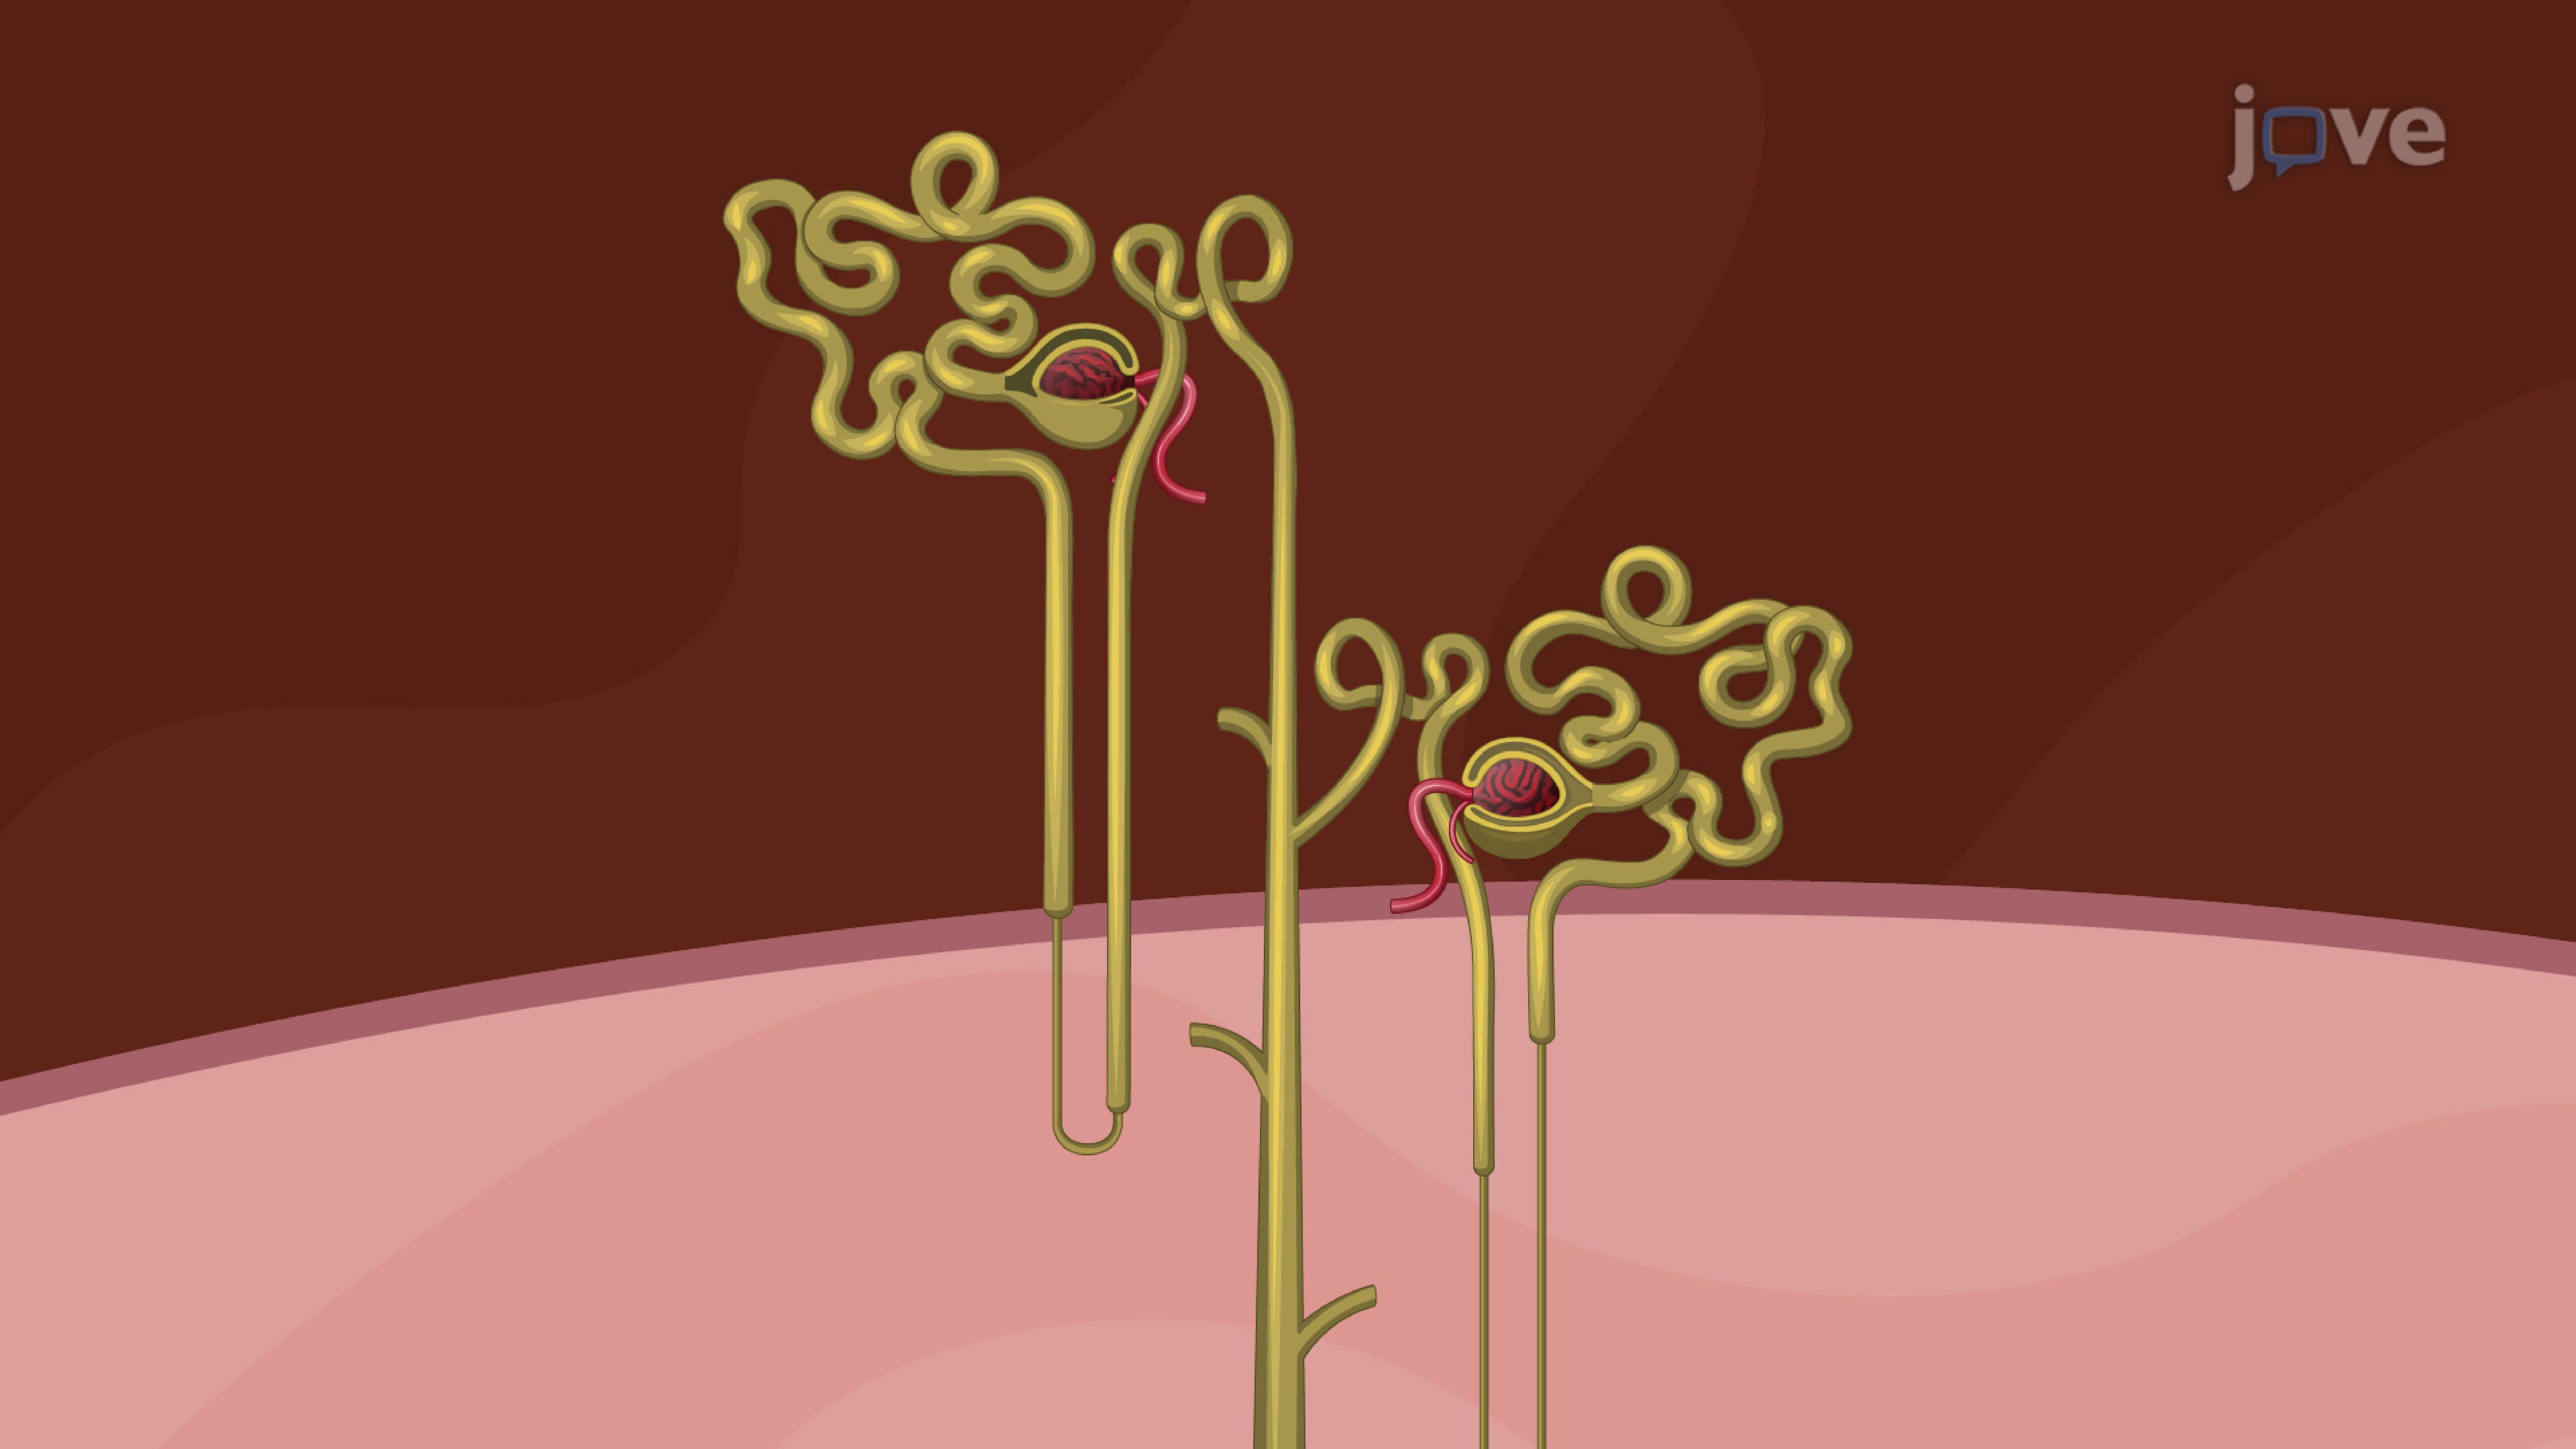
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules...
 01:08
Effect of Hepatic Disease on Pharmacokinetics: Dose Adjustments Due to Hepatic Impairment