Related Experiment Video For Endometrial cancer
Updated: Apr 22, 2026


An Orthotopic Endometrial Cancer Model with Retroperitoneal Lymphadenopathy Made From In Vivo Propagated and Cultured VX2 Cells
Published on: September 12, 2019
Clinically significant endometrial cancer risk following a diagnosis of complex atypical hyperplasia
Anthony B Costales1, Kathleen M Schmeler2, Russell Broaddus3
1Department of Obstetrics and Gynecology, The University of Texas Medical School at Houston, Houston, Texas.

Objectives:
Because of the frequent detection of carcinoma in surgical specimens after hysterectomy for endometrial complex atypical hyperplasia (CAH), it has been suggested that patients with a preoperative diagnosis of CAH be referred to gynecologic oncology for potential lymphadenectomy. However, the risk of lymph node metastasis in such patients is unknown. We sought to determine the risk of endometrial cancer and to estimate the risk of lymphatic spread in women with a preoperative diagnosis of CAH.
Study Design:
We retrospectively reviewed the medical records of 150 consecutive patients with a preoperative diagnosis of CAH who subsequently underwent hysterectomy. Clinical characteristics and pathologic information were abstracted. Risk of lymphatic spread was modeled using previously published criteria and nomograms.
Results:
Fifty-five of the 150 patients (36.7%) had an incidental endometrial carcinoma at the time of hysterectomy. Among patients with a preoperative office biopsy compared to dilation and curettage, the rate of an incidental finding of cancer was 43.5% and 28.1%, respectively (p=0.054). Of patients with cancer, 1 (1.8%) had a grade 3 endometrial carcinoma, 4 (7.3%) had lymphovascular space involvement, and 6 (10.9%) had deep (>50%) myometrial invasion. For the 10 patients who underwent lymphadenectomy, one (10%) had lymph node metastases. Based on multiple models, the estimated risk of lymph node spread was 1.6%-2.1% for all women with a preoperative diagnosis of CAH and 4.4%-6.8% for the 55 women with endometrial cancer.
Conclusions:
Given the high rates of underlying endometrial cancer and the potential need for lymphadenectomy, care for patients with a preoperative diagnosis of CAH desiring definitive management with hysterectomy should be referred to a gynecologic oncologist.
More Related Videos

Related Concept Videos
 01:24
Disorders of the Female Reproductive System
 01:24
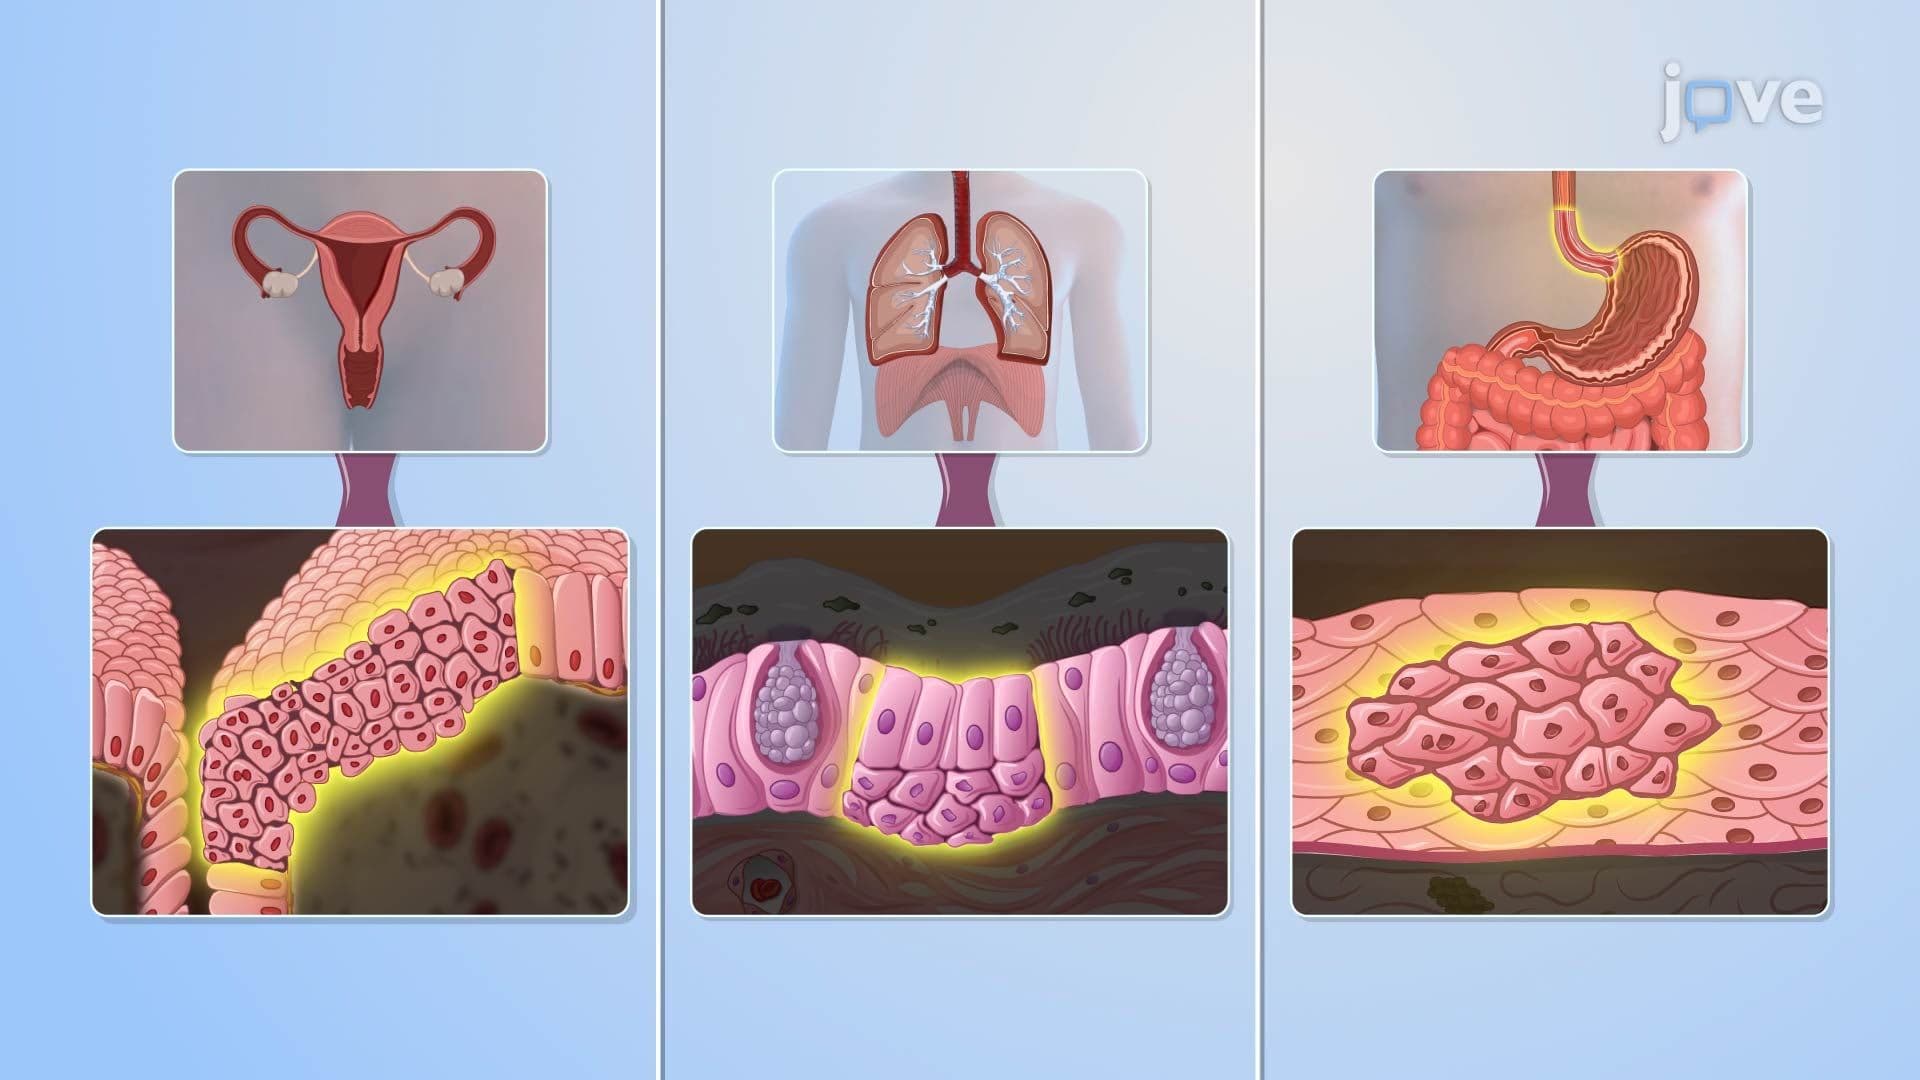
Cellular Adaptation IV: Dysplasia and Metaplasia