
[Retroiridal iris claw lens as routine procedure]
H Häberle1, S Schiedel1, D-T Pham1
1Klinik für Augenheilkunde, Vivantes Klinikum Neukölln, Berlin.

Background:
Absence of capsular support or extended zonulolysis is today the main indication for retroiridal enclavation of the unfoldable PMMA iris claw lens (Verisyse®/Artisan®) if there is sufficient iris support. Contraindications are uveitis or ischaemic retinopathies.
Patients And Methods:
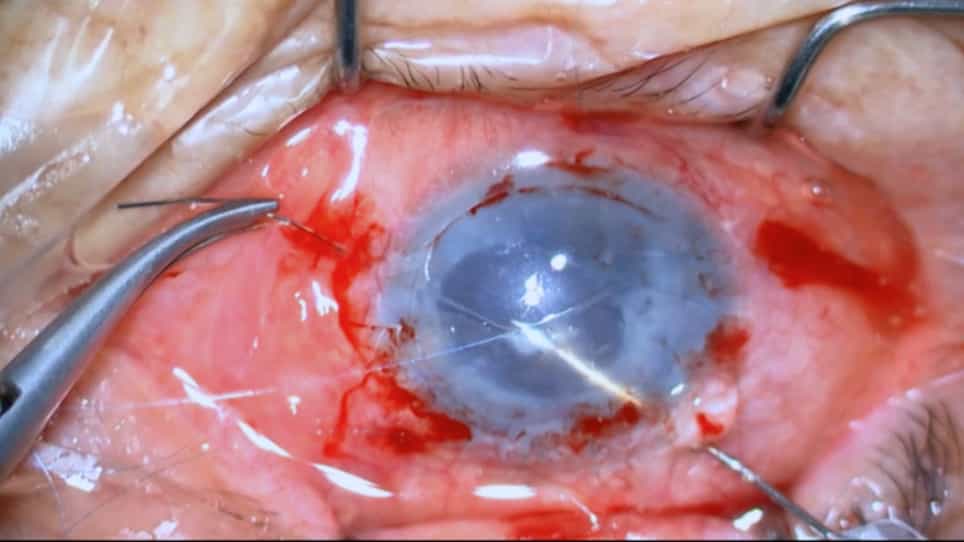
'In-the-bag' IOL dislocation due to PEX zonulopathy usually occurring 8 years after phacoemulsification is the main indication. For complicated phacoemulsification with extended zonular defect the retroiridal iris claw lens (Verisyse®/Artisan®) has become the stand-by IOL of first choice. A rare indication for Verisyse is optical rehabilitation after lens luxation into the vitreous in combination with vitrectomy.
Results:
81 eyes were analysed. With laseroptic biometry target refraction was within 1 D for 100 % of the 'in-the-bag' luxation cases and in 62 % for the other more complicated cases. Wavefront analysis showed no significant difference for optical quality between retroiridal iris claw lens and a endocapsular fixated spherical for scotopic 5 mm pupil. Iris pigment atrophies of the enclavation site had no clinical significance. Risk for cystoid macular oedema is lower compared to sclera suture-fixated posterior chamber lenses. Intra- and postoperative complications were rare. Spontaneous or traumatic de-enclavation due to haptic defects may occur. After vitrectomy instable refraction may be caused by hypermobile iris diaphragma.
Conclusions:
Retroiridal iris claw lenses can be implanted atraumatically under topical anaesthesia. IOL related complications are minimal.