Related Experiment Video
Updated: Apr 21, 2026
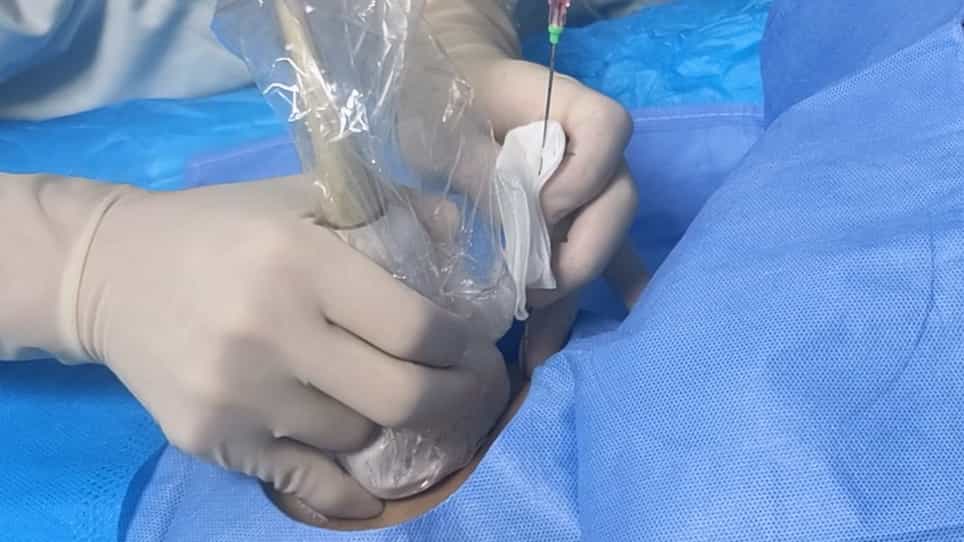

A Two-Step Method for Percutaneous Transhepatic Choledochoscopic Lithotomy
Published on: September 13, 2022
Agomelatine-induced liver injury in a patient with choledocholithiasis
Piotr Eder1, Agnieszka Permoda-Osip2, Przemyslaw Majewski3
11Department of Gastroenterology,Human Nutrition and Internal Diseases,Poznan University of Medical Sciences,Poznan,Poland.

Objective:
A case of agomelatine-induced hepatotoxicity is described in a 47-year female patient who has received the drug, 25 mg/day, for 4 months, for the treatment of depression.
Methods:
The patient was admitted to the Department of Gastroenterology because of fatigue and nausea, with concomitant elevation of alanine aminotransferase (ALT), 550 U/L, and asparagine aminotransferase (AST), 300 U/L.
Results:
Liver biopsy showed diffuse lymphocyte infiltration in the dilated portal spaces without lesion of hepatic lobules. Several weeks after stopping agomelatine, the liver enzymes returned to normal. Subsequently, small gallstones in common bile duct were detected and removed by the endoscopic sphincterotomy.
Conclusions:
It is hypothesized that choledocholithiasis could theoretically increase a risk of developing agomelatine-induced hepatotoxicity in this patient. Any pre-existing liver disease should be a contraindication for treatment with agomelatine.

Related Concept Videos
 01:20
Cholecystitis
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:24
Drugs for Peptic Ulcer Disease: Sucralfate as Mucosal Protective Agents
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...
 01:14
Prevention of Further Absorption of Poison
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:26
Gastritis II: Pathophysiology