Related Experiment Video
Updated: Apr 21, 2026

Investigating the Effects of Probiotics on Pneumococcal Colonization Using an In Vitro Adherence Assay
Published on: April 28, 2014
Probiotics for preventing ventilator-associated pneumonia
Lulong Bo1, Jinbao Li, Tianzhu Tao
1Department of Anaesthesiology and Intensive Care Medicine, Changhai Hospital, Second Military Medical University, 14th Floor, 168 Changhai Rd, Shanghai, China, 200433.

Background:
Ventilator-associated pneumonia (VAP) is common in intensive care units (ICUs). Some evidence indicates that probiotics may reduce the incidence of VAP. Several additional published studies have demonstrated that probiotics are safe and efficacious in preventing VAP in ICUs. We aimed to systematically summarise the results of all available data to generate the best evidence for the prevention of VAP.
Objectives:
To evaluate the effectiveness and safety of probiotics for preventing VAP.
Search Methods:
We searched CENTRAL (2014, Issue 8), MEDLINE (1948 to September week 1, 2014) and EMBASE (2010 to September 2014).
Selection Criteria:
Randomised controlled trials (RCTs) comparing probiotics with placebo or another control (excluding RCTs that use probiotics in both study groups) to prevent VAP.
Data Collection And Analysis:
Two review authors independently assessed eligibility and the quality of trials, and extracted data.
Main Results:
We included eight RCTs, with 1083 participants. All studies compared a form of probiotic (Lactobacillus casei rhamnosus; Lactobacillus plantarum; Synbiotic 2000FORTE; Ergyphilus; combination Bifidobacterium longum + Lactobacillus bulgaricus + Streptococcus thermophilus) versus a control group (placebo; glutamine; fermentable fibre; peptide; chlorhexidine). The analysis of all RCTs showed that the use of probiotics decreased the incidence of VAP (odds ratio (OR) 0.70, 95% confidence interval (CI) 0.52 to 0.95, low quality evidence). However, the aggregated results were uncertain for ICU mortality (OR 0.84, 95% CI 0.58 to 1.22 very low quality evidence), in-hospital mortality (OR 0.78, 95% CI 0.54 to 1.14, very low quality evidence), incidence of diarrhoea (OR 0.72, 95% CI 0.47 to 1.09, very low quality evidence), length of ICU stay (mean difference (MD) -1.60, 95% CI -6.53 to 3.33, very low quality evidence), duration of mechanical ventilation (MD -6.15, 95% CI -18.77 to 6.47, very low quality evidence) and antibiotic use (OR 1.23, 95% CI 0.51 to 2.96, low quality evidence). Antibiotics for VAP were used for a shorter duration (in days) when participants received probiotics in one small study (MD -3.00, 95% CI -6.04 to 0.04). However, the CI of the estimated effect was too wide to exclude no difference with probiotics. There were no reported events of nosocomial probiotic infections in any included study.The overall methodological quality of the included studies, based on our 'Risk of bias' assessments, was moderate with half of the included studies rated as a 'low' risk of bias; however, we rated four included studies as a 'high' risk of bias across one or more of the domains. The study limitations, differences in probiotics administered and participants, and small sample sizes across the included studies mean that the power to detect a trend of overall effect may be limited and chance findings cannot be excluded.To explore the influence of some potential confounding factors in the studies, we conducted an intention-to-treat (ITT) analysis, which did not change the inference of per-protocol analysis. However, our sensitivity analysis did not indicate a significant difference between groups for instances of VAP.
Authors' Conclusions:
Evidence suggests that use of probiotics is associated with a reduction in the incidence of VAP. However, the quality of the evidence is low and the exclusion of the one study that did not provide a robust definition of VAP increased the uncertainty in this finding. The available evidence is not clear regarding a decrease in ICU or hospital mortality with probiotic use. Three trials reported on the incidence of diarrhoea and the pooled results indicate no clear evidence of a difference. The results of this meta-analysis do not provide sufficient evidence to draw conclusions on the efficacy and safety of probiotics for the prevention of VAP in ICU patients.
Related Concept Videos
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:22
Probiotics
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:29
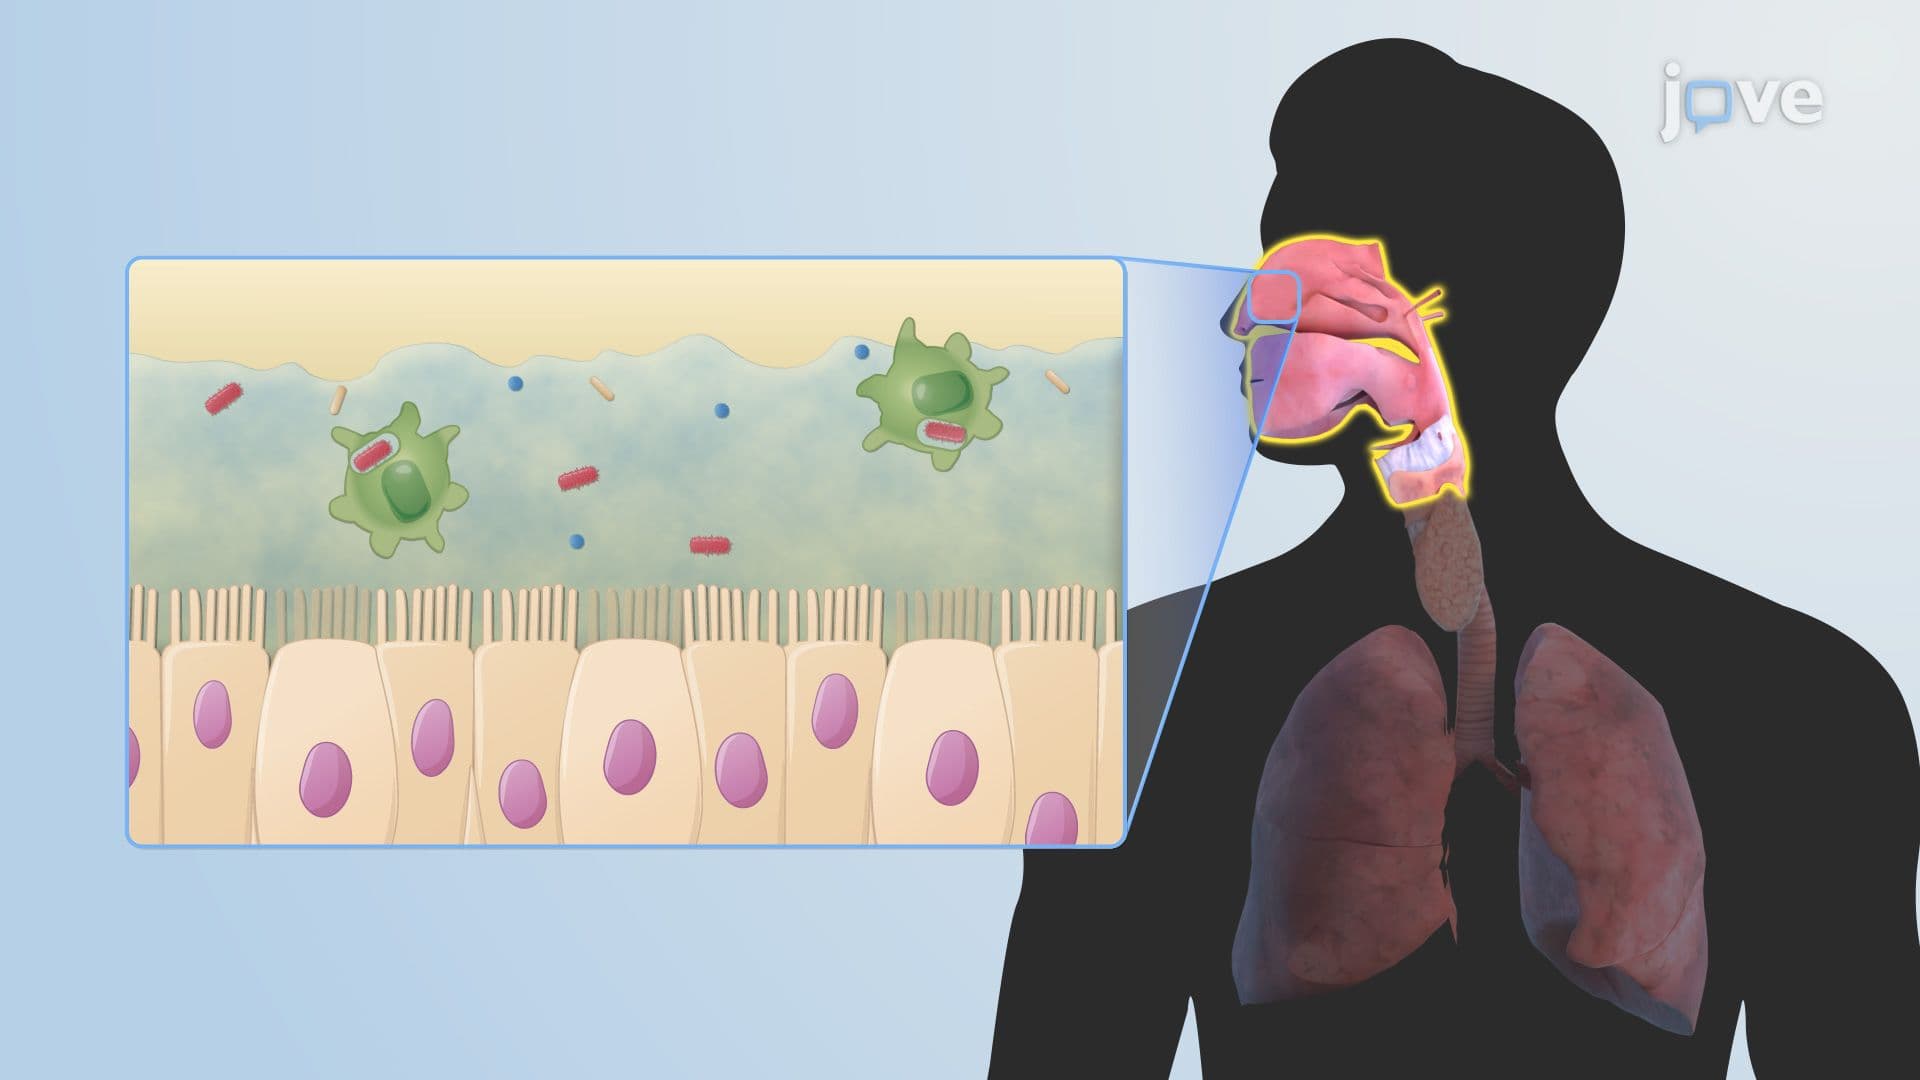
Microbiota of the Respiratory Tract
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:25
Transmission-based Precautions II: Airborne and Protective Environment
Airborne precautions:
Use airborne precautions when treating patients known or suspected to have diseases that spread through the air—for example, tuberculosis or measles. These organisms are present in smaller droplets expelled by an infected person and...