Related Experiment Video
Updated: Apr 21, 2026
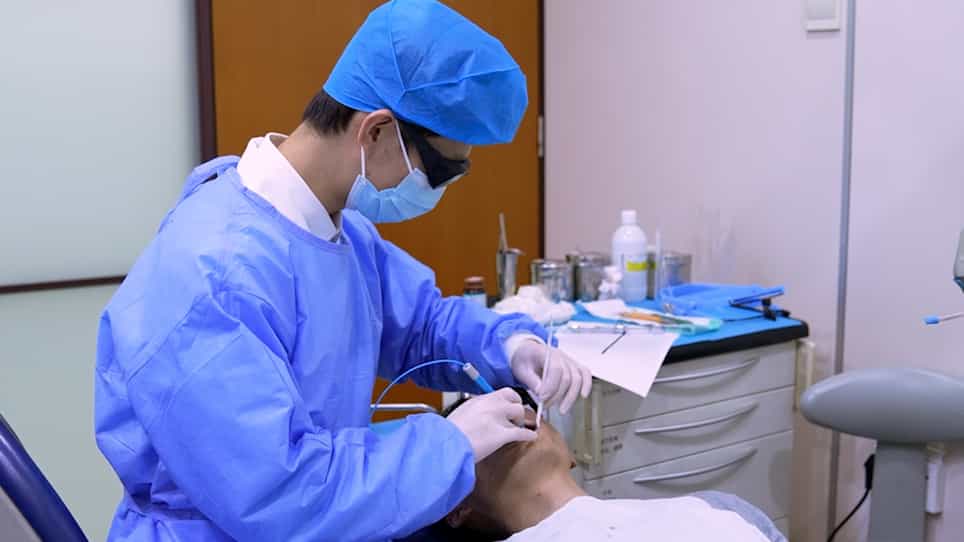

Adjunctive Diode Laser Therapy and Probiotic Lactobacillus Therapy in the Treatment of Periodontitis and Peri-Implant Disease
Published on: May 9, 2022
The treatment of chronic recurrent oral aphthous ulcers
Andreas Altenburg1, Nadine El-Haj, Christiana Micheli
1Departments of Dermatology, Venereology, Allergology and Immunology, Dessau Medical Center, Pharmacy, Dessau Medical Center, Department of Dermatology and Andrology, Faculty of Medicine, Ain Shams University, Cairo (Egypt).

Background:
Chronic recurrent oral aphthous ulcers are the most common type of inflammatory efflorescence of the oral mucosa, with a prevalence of 2% to 10% in Caucasian populations. To treat them properly, physicians should know their clinical appearance and course, conditioning factors, underlying causes, and differential diagnosis.
Method:
This review is based on pertinent articles that were retrieved by a selective search in PubMed and in the Cochrane Central Register of Controlled Trials.
Results:
Hard, acidic, and salty foods and toothpastes containing sodium lauryl sulfate should be avoided, along with alcohol and carbonated drinks. In Germany, the only drugs that have been approved to treat oral aphthous ulcers are corticosteroids, topical antiseptic/anti-inflammatory agents such as triclosan and diclofenac, and local anesthetics such as lidocaine. Antiseptic agents and local anesthetics should be tried first; if these are ineffective, topical cortico steroids should be used. In severe cases, local measures can be combined with systemic drugs, e.g., colchicine, pentoxifylline, or prednisolone. The efficacy of systemic treatment is debated. Other immunosuppressive agents should be given systemically only for refractory or particularly severe oral aphthous ulcers due to Adamantiades-Behçet disease.
Conclusion:
The treatment of chronic recurrent oral aphthous ulcers is symptomatic, mainly with topically applied agents. It is tailored to the severity of the problem in the individual case, i.e., the frequency of ulcers, the intensity of pain, and the responsiveness of the lesions to treatment. Effective treatment relieves pain, lessens functional impairment, and lowers the frequency and severity of recurrences.
Related Concept Videos
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current...
 01:24
Drugs for Peptic Ulcer Disease: Sucralfate as Mucosal Protective Agents
In this scenario, mucosal protective agents like sucralfate play an essential role. Sucralfate, a complex of sulfated sucrose and aluminum hydroxide, demonstrates its usefulness in acidic conditions,...
 01:16
Treating Helicobacter pylori in Peptic Ulcers: Antimicrobial Therapy
 01:30
Acute Pharyngitis
Acute pharyngitis is the inflammation of the back of the throat (pharynx), commonly resulting in a sore throat. It is a frequently encountered condition that prompts individuals to seek medical advice.
Classification
Acute pharyngitis can be categorized based on its underlying cause:
 01:23
Gastritis III: Clinical Manifestations and Management
Clinical manifestations of acute gastritis
The patient with acute gastritis may have a rapid onset of symptoms, such as epigastric pain or discomfort, dyspepsia, anorexia, hiccups, or nausea and vomiting, which can last from a few hours to a few days. Erosive or hemorrhagic gastritis may cause bleeding, which may manifest as blood in vomit or as...
 01:31
Acid Suppressive Drugs for Peptic Ulcer Disease: Antacids
However, this neutralization reaction between...