Related Experiment Video
Updated: Apr 21, 2026

Modeling Ascending Vaginal Infection, Preterm Birth, and Neonatal Morbidity in Mice
Published on: October 10, 2025
[Increased risk of stillbirth in older mothers--a rationale for induction of labour before term?]
1Gynäkologie und Geburtshilfe, Medizinische Fakultät, Universitätsklinikum Aachen, Aachen.

The average age of childbearing has risen markedly in Germany and other high-income countries during the past 2 decades. Women aged 35 years or older have an increase in pregnancy complications and in preexisting medical conditions including obesity, diabetes and hypertension as well as a significant increase in the gestational age-related rate of stillbirth compared to younger mothers. Additional individual risk factors for stillbirth are primiparity, body mass index>30 and smoking. After exclusion of risk factors the absolute risk of stillbirth in women aged≥40 years old is 2-fold higher (1 in 503 maternities) at 39/40 weeks of gestation compared to women aged<35 years (1 in 1 020 maternities) at the same gestational age. Women aged 40 years or older have a similar stillbirth risk at 39 weeks of gestation to 25-29-year-olds at 41 weeks gestation. The underlying mechanism for the excess risk of stillbirth in women of advanced maternal age after exclusion of congenital anomalies is unknown. Independent of maternal age the cumulative probability of perinatal death increases from 1.8/1 000 deliveries at 38 weeks of gestation to 9.3/1 000 deliveries at 42 weeks of gestation. Whether on the basis of these data induction of labour at 39 weeks of gestation should be recommended in women of advanced maternal age has recently been discussed in a Scientific Impact Paper of the Royal College of Obstetricians and Gynaecologists. In this context it should be taken into account that the rate of Caesarean sections in women aged 40 years or over is 40%, and, in particular, older nulliparous may request elective Caesaran section rather than elective induction of labour. Recent metaanalyses have shown that elective induction of labour before or after term is not associated with an increase of the Caesarean section rate compared to expectant management. Up to now no randomised controlled trials exist and consequently no -recommendations from current guidelines regarding induction of labour in women of advanced maternal age can be given. In any case, a careful consultation and an individual risk-benefit analysis regarding the obstetric management is mandatory, and the final decision should be made in agreement between the pregnant women and the obstetrician. Currently a randomised controlled trial in the U.K. comparing induction of labour at 39 weeks of gestation with expectant management in nulliparous women aged over 35 years is recruiting, with the aim to determine intrapartum complications and perinatal morbidity and mortality in both managements.
The average age of childbearing has risen markedly in Germany and other high-income countries during the past 2 decades. Women aged 35 years or older have an increase in pregnancy complications and in preexisting medical conditions including obesity, diabetes and hypertension as well as a significant increase in the gestational age-related rate of stillbirth compared to younger mothers. Additional individual risk factors for stillbirth are primiparity, body mass index>30 and smoking. After exclusion of risk factors the absolute risk of stillbirth in women aged≥40 years old is 2-fold higher (1 in 503 maternities) at 39/40 weeks of gestation compared to women aged<35 years (1 in 1 020 maternities) at the same gestational age. Women aged 40 years or older have a similar stillbirth risk at 39 weeks of gestation to 25-29-year-olds at 41 weeks gestation. The underlying mechanism for the excess risk of stillbirth in women of advanced maternal age after exclusion of congenital anomalies is unknown. Independent of maternal age the cumulative probability of perinatal death increases from 1.8/1 000 deliveries at 38 weeks of gestation to 9.3/1 000 deliveries at 42 weeks of gestation. Whether on the basis of these data induction of labour at 39 weeks of gestation should be recommended in women of advanced maternal age has recently been discussed in a Scientific Impact Paper of the Royal College of Obstetricians and Gynaecologists. In this context it should be taken into account that the rate of Caesarean sections in women aged 40 years or over is 40%, and, in particular, older nulliparous may request elective Caesaran section rather than elective induction of labour. Recent metaanalyses have shown that elective induction of labour before or after term is not associated with an increase of the Caesarean section rate compared to expectant management. Up to now no randomised controlled trials exist and consequently no -recommendations from current guidelines regarding induction of labour in women of advanced maternal age can be given. In any case, a careful consultation and an individual risk-benefit analysis regarding the obstetric management is mandatory, and the final decision should be made in agreement between the pregnant women and the obstetrician. Currently a randomised controlled trial in the U.K. comparing induction of labour at 39 weeks of gestation with expectant management in nulliparous women aged over 35 years is recruiting, with the aim to determine intrapartum complications and perinatal morbidity and mortality in both managements.


Related Concept Videos
 01:07
Teratogenicity
 02:57
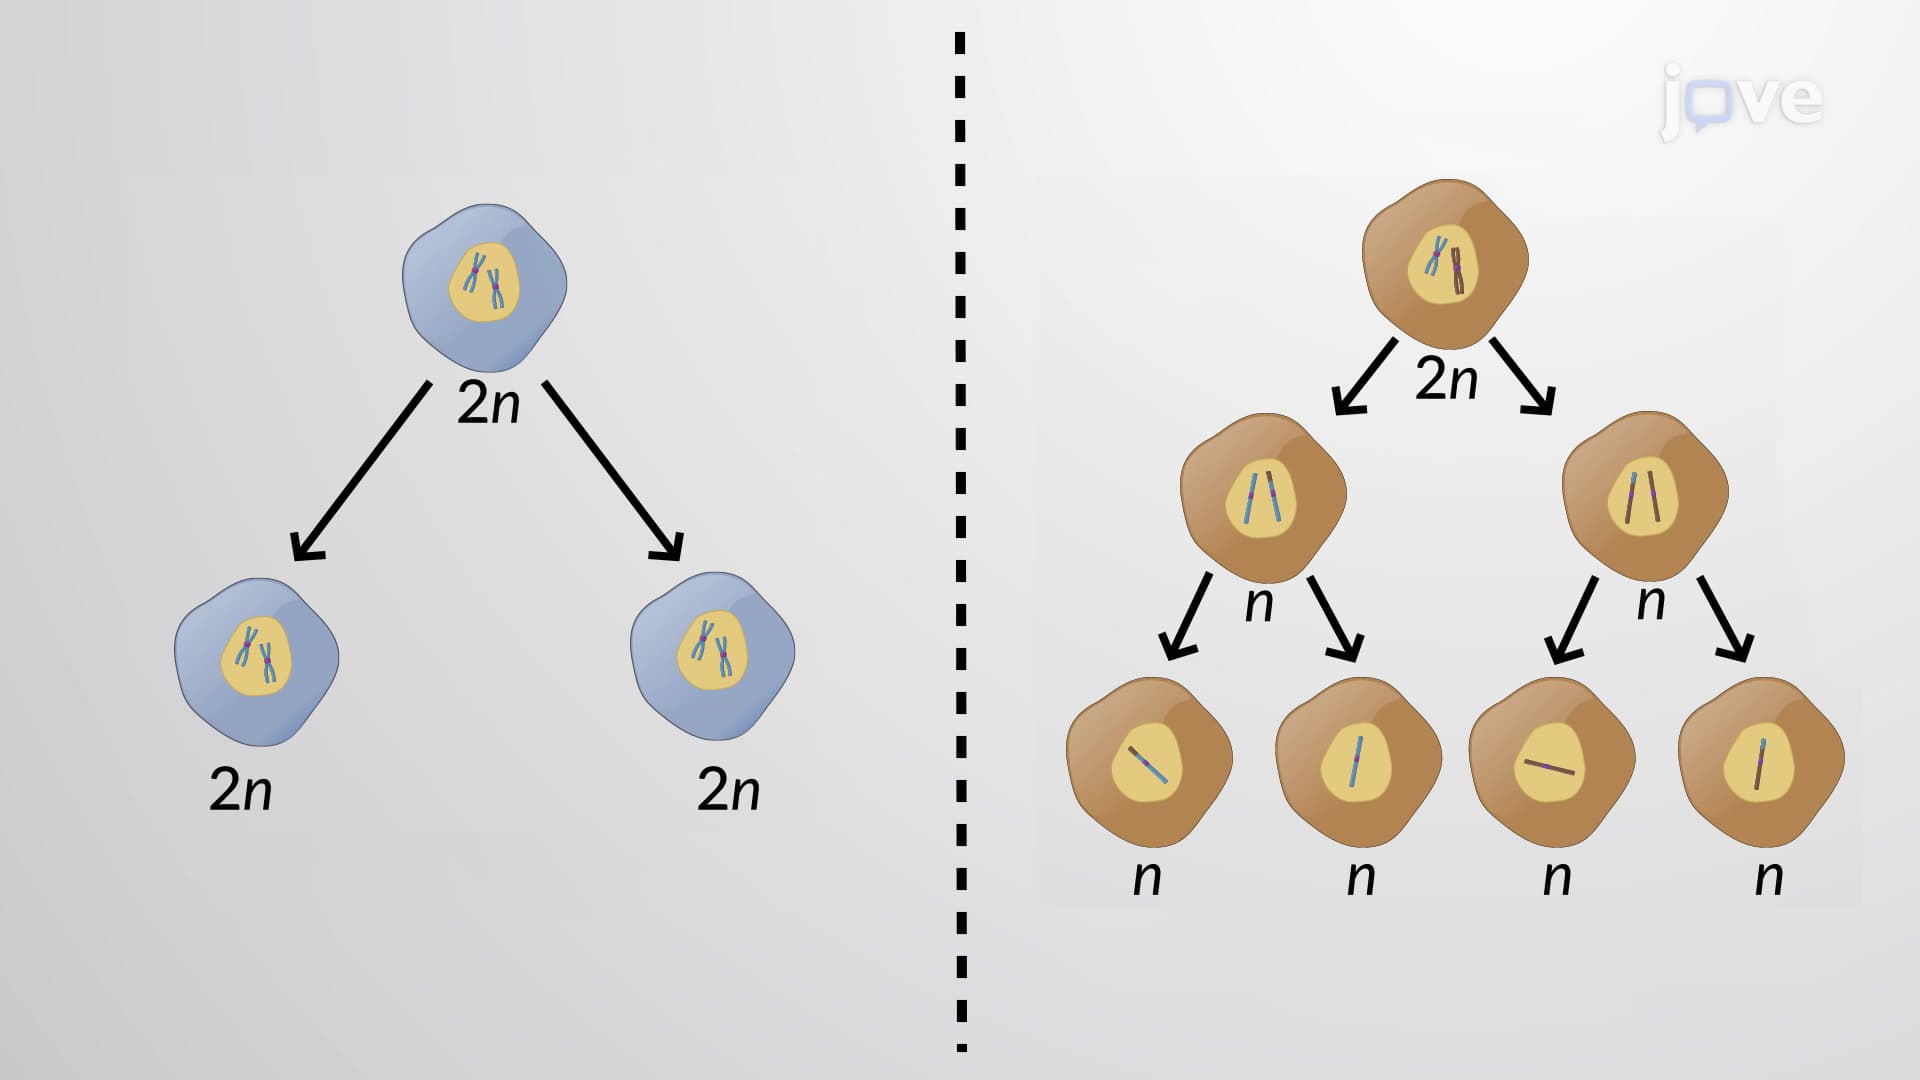
Meiosis vs. Mitosis
Before the start of mitosis and meiosis I, the cell synthesizes DNA, resulting in two homologous copies of each chromosome. DNA synthesis is...
 01:19
Mitral Valve Prolapse III: Nursing Management
 01:21
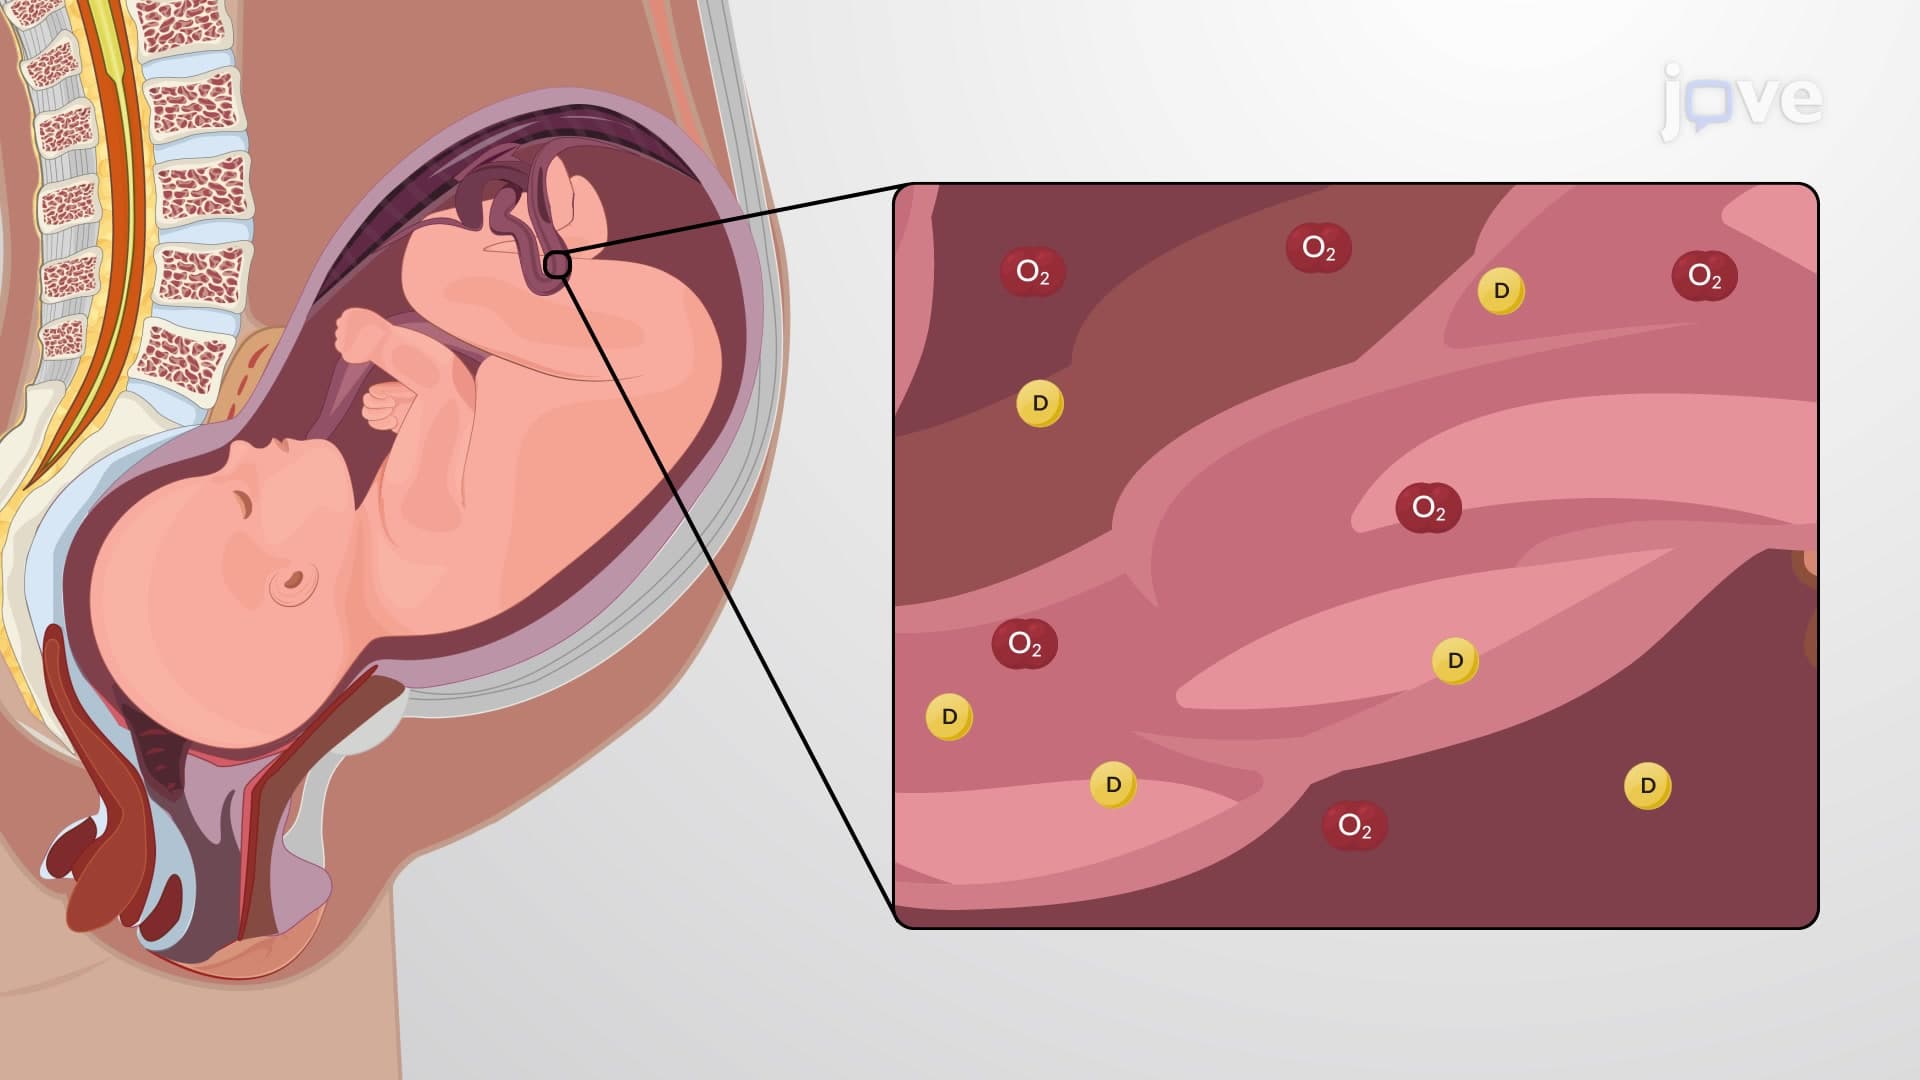
Factors Affecting Drug Response: Overview
 01:29
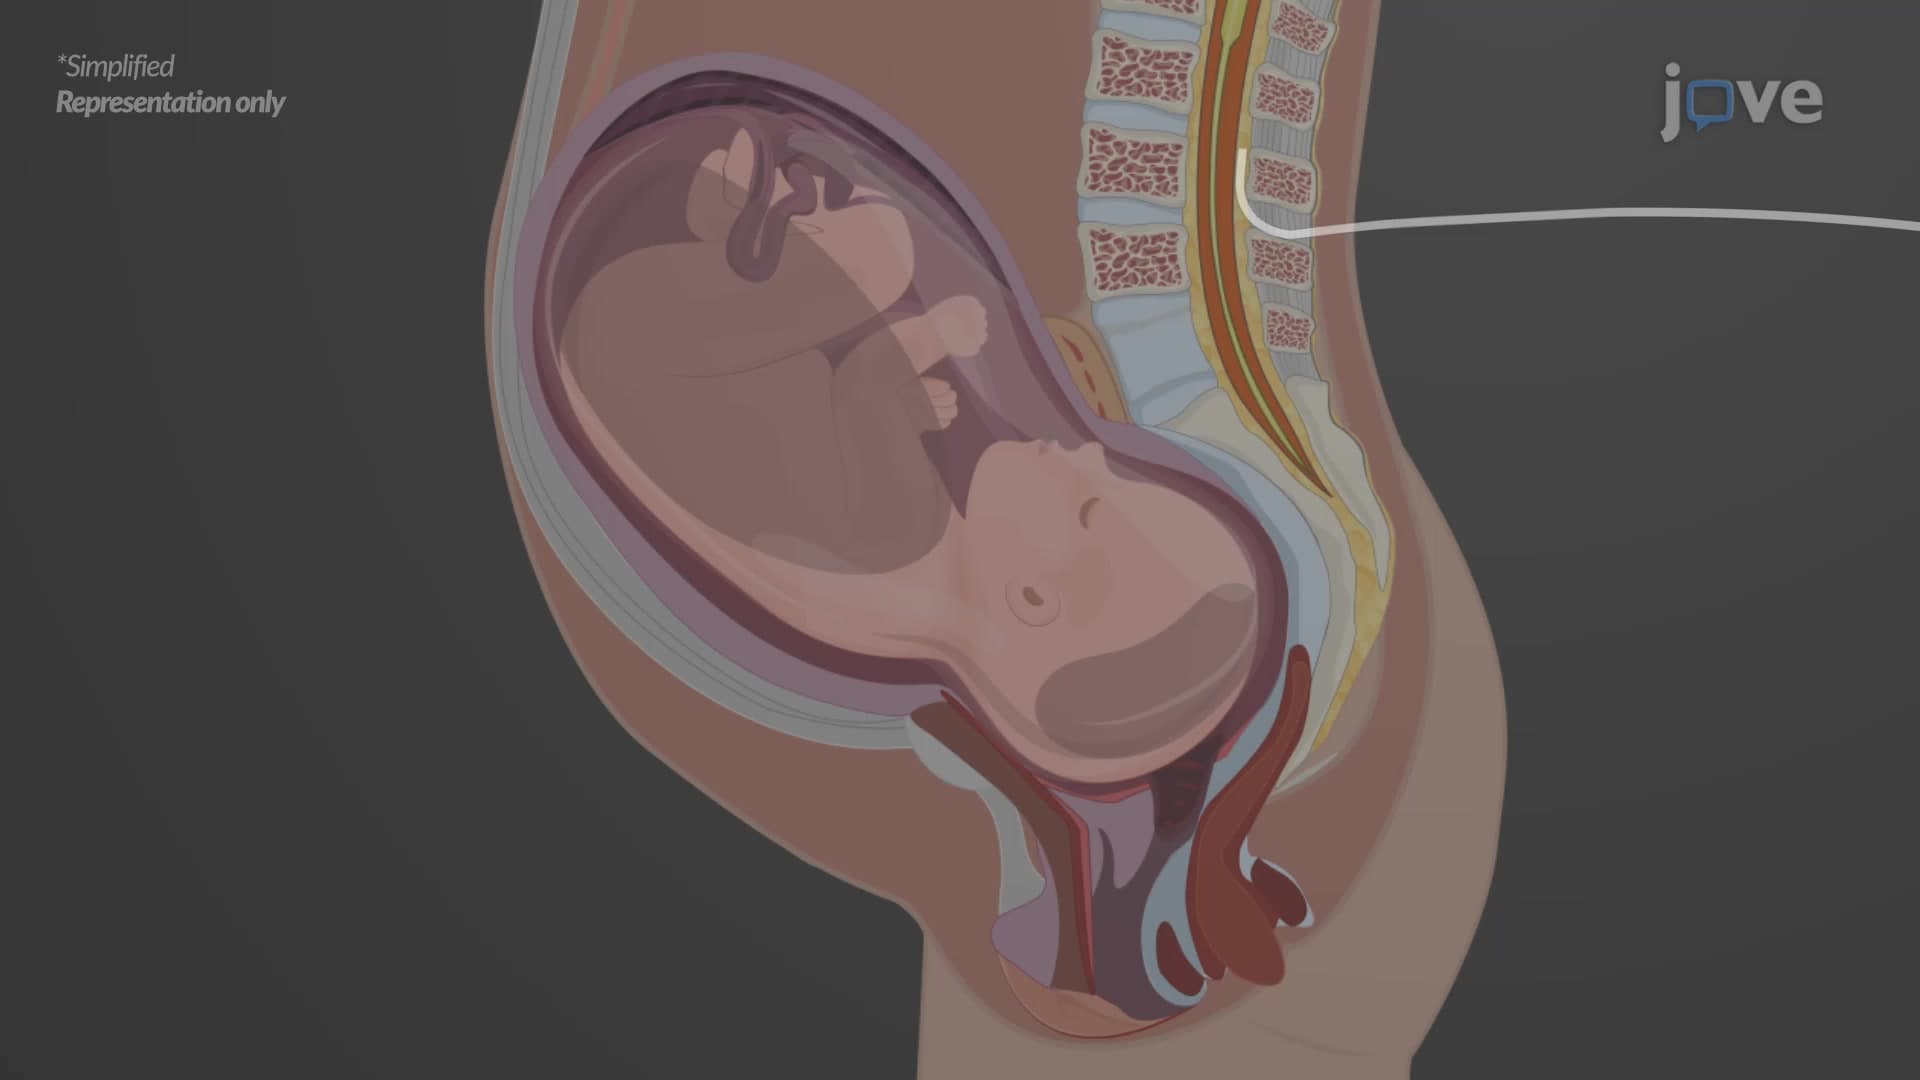
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...
 01:22
Diabetes Mellitus: Type 2 and Gestational