Related Experiment Video
Updated: Apr 21, 2026

Laparoscopic Repair of Para-Esophageal Hernia Using Absorbable Biosynthetic Mesh
Published on: September 11, 2021
A rare case of oesophageal rupture: Boerhaave's syndrome
Gerben van der Weg1, Marald Wikkeling2, Maarten van Leeuwen3
1Department of Emergency Medicine, Medical Centre Leeuwarden, Henry Dunantweg 2, Leeuwarden 8934, BR, the Netherlands.

Abstract:
A 70-year-old patient was referred to our emergency department with severe retrosternal pain after forceful vomiting. Computed tomography (CT) scan revealed a left-sided oesophageal rupture with accompanying pneumomediastinum and bilateral pleural effusions. Conservative treatment with cessation of oral intake, intravenous broad-spectrum antibiotics, parenteral fluids and nutrition and left sided tube thoracostomy was initiated initially. After 5 days, however, the patient deteriorated. Follow-up CT scan demonstrated a mediastinal fluid collection as well as loculated pleural empyema. Open thoracotomy with mediastinal debridement and pleural drainage was performed, after which he made a slow but full recovery. Spontaneous oesophageal rupture due to an abrupt rise in intraluminal pressure caused by vomiting is also known as Boerhaave's syndrome. It is a rare but potentially life-threatening condition. Many patients present with atypical symptoms, and therefore, physicians should have a high index of suspicion in any patient presenting with vomiting and retrosternal pain. When Boerhaave's syndrome is suspected, a CT scan of the thorax and upper abdomen should be performed since treatment depends on clinical and radiological findings. Conservative management (cessation of oral intake, nasogastric decompression, administration of intravenous fluids and parenteral nutrition, intravenous broad-spectrum antibiotics and proton pump inhibitors and tube thoracostomies) may only be considered in patients with a contained rupture without systematic symptoms of infection. In these patients, endoscopic bridging of the tear with a self-expandable stent is also an option. Primary surgical repair (either by thoracotomy or by video assisted thoracoscopy (VATS)) should be considered when patients present with sepsis and/or large non-contained leaks or with severe mediastinal decontamination.


Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:24
Esophageal Varices-I: Introduction
 01:25
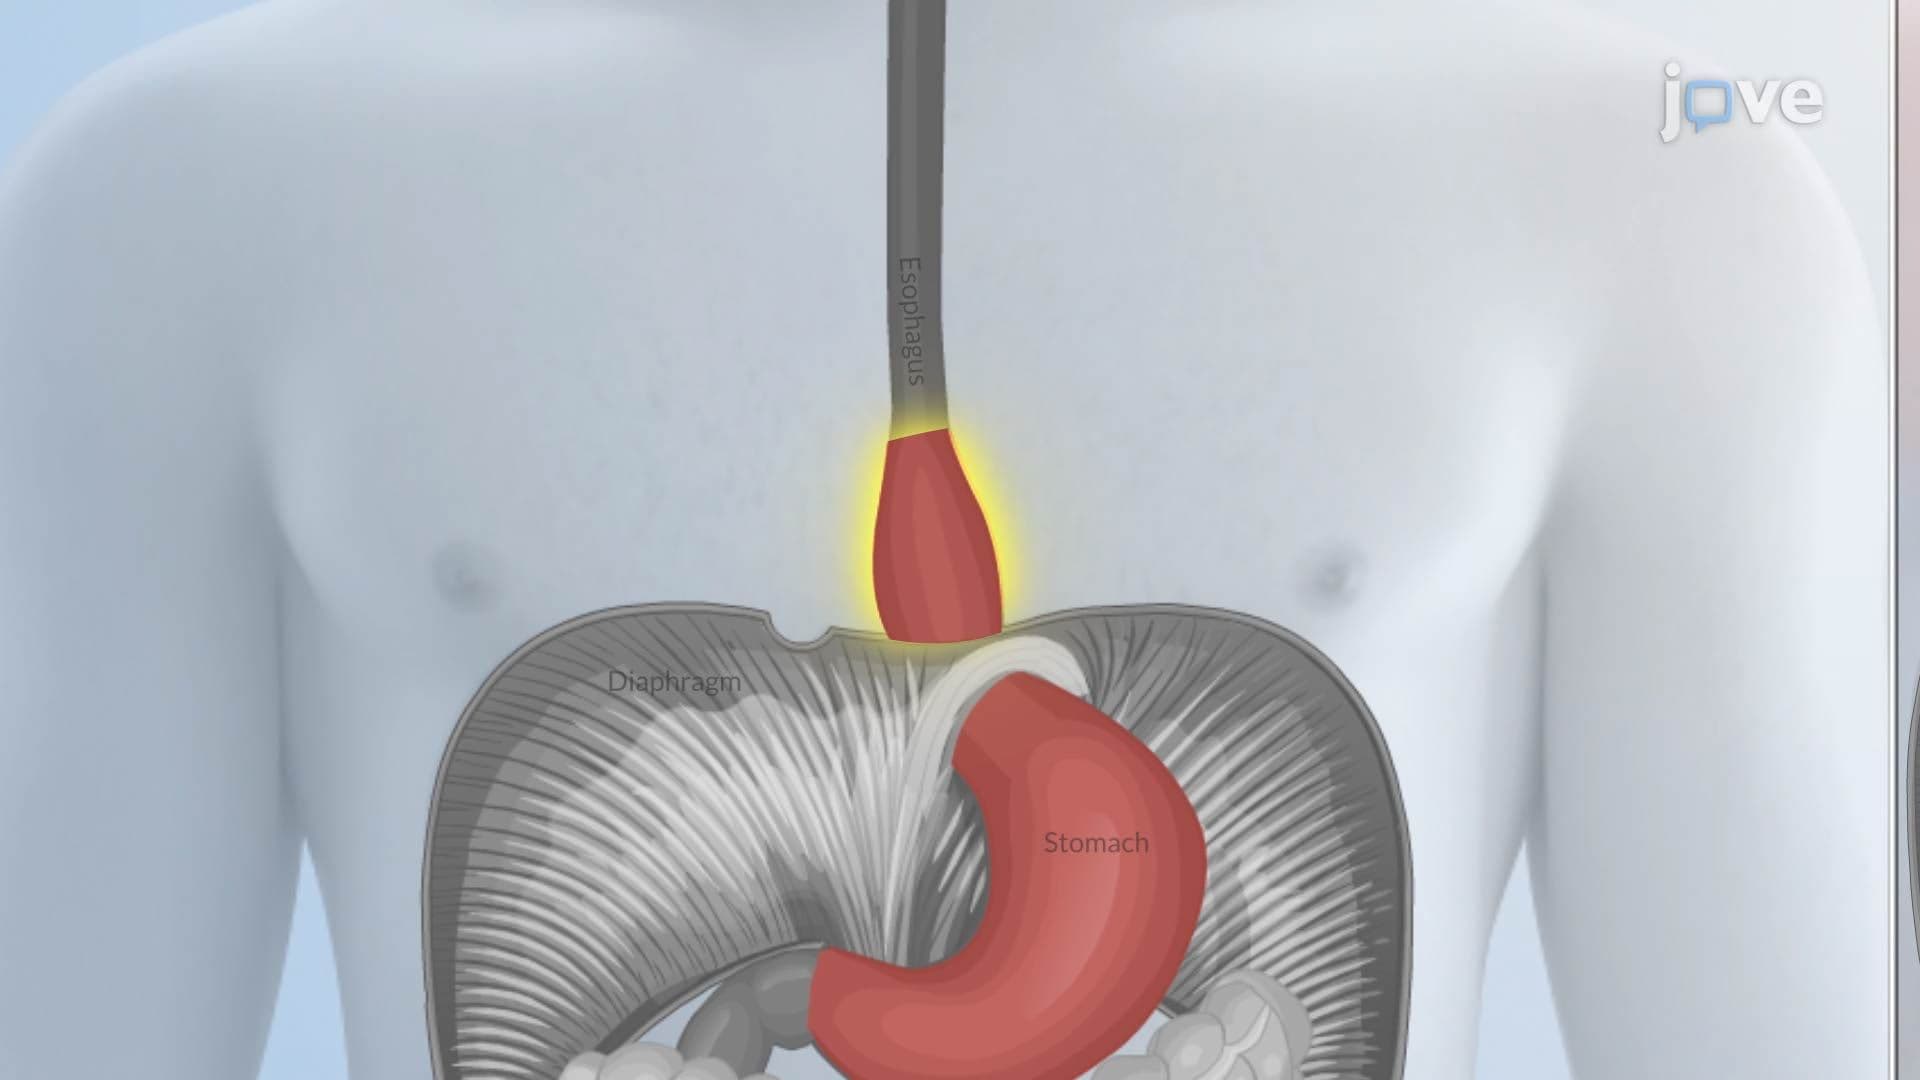
Hiatal Hernia
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure...