Balancing ischaemia and bleeding risks with novel oral anticoagulants
Related Experiment Video
Updated: Apr 21, 2026

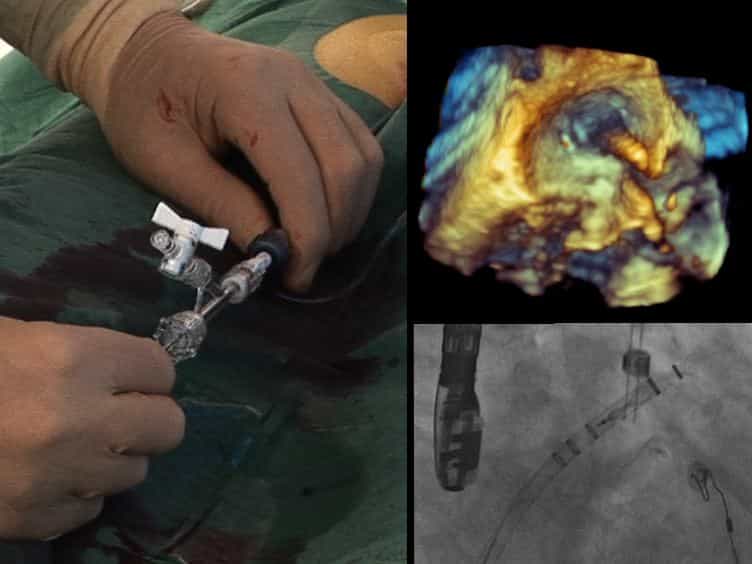
The WATCHMAN Left Atrial Appendage Closure Device for Atrial Fibrillation
Published on: February 28, 2012
Usman Baber1, Ioannis Mastoris1, Roxana Mehran1
1Icahn School of Medicine at Mount Sinai, One Gustave L. Levy Place, PO Box 1030, New York, NY 10029, USA.

Vitamin K antagonists (VKAs) have long been the standard of care for treatment of venous thromboembolism (VTE), and thromboprophylaxis in atrial fibrillation (AF). Despite their efficacy, their use requires frequent monitoring and is complicated by drug-drug interactions and the need to maintain a narrow therapeutic window. Since 2009, novel oral anticoagulants (NOACs), including the direct thrombin inhibitor dabigatran and the direct factor Xa inhibitors apixaban, edoxaban, and rivaroxaban, have become alternative options to VKAs owing to their predictable and safe pharmacological profiles. The overall clinical effect of these drugs, which is a balance between ischaemic benefit and bleeding harm, varies according to the clinical scenario. As adjunctive therapy to dual antiplatelet therapy in patients with acute coronary syndrome, NOACs are associated with incremental bleeding risks and modest benefits. For treatment of VTE, NOACs have a safer profile than VKAs and a similar efficacy. In thromboprophylaxis in AF, NOACs are associated with the greatest benefits by reducing both ischaemic events and haemorrhagic complications and might reduce mortality compared with VKAs. The role of NOACs continues to evolve as these drugs are evaluated in different patient populations, including those with renal impairment or with AF and undergoing percutaneous coronary intervention.
Vitamin K antagonists (VKAs) have long been the standard of care for treatment of venous thromboembolism (VTE), and thromboprophylaxis in atrial fibrillation (AF). Despite their efficacy, their use requires frequent monitoring and is complicated by drug-drug interactions and the need to maintain a narrow therapeutic window. Since 2009, novel oral anticoagulants (NOACs), including the direct thrombin inhibitor dabigatran and the direct factor Xa inhibitors apixaban, edoxaban, and rivaroxaban, have become alternative options to VKAs owing to their predictable and safe pharmacological profiles. The overall clinical effect of these drugs, which is a balance between ischaemic benefit and bleeding harm, varies according to the clinical scenario. As adjunctive therapy to dual antiplatelet therapy in patients with acute coronary syndrome, NOACs are associated with incremental bleeding risks and modest benefits. For treatment of VTE, NOACs have a safer profile than VKAs and a similar efficacy. In thromboprophylaxis in AF, NOACs are associated with the greatest benefits by reducing both ischaemic events and haemorrhagic complications and might reduce mortality compared with VKAs. The role of NOACs continues to evolve as these drugs are evaluated in different patient populations, including those with renal impairment or with AF and undergoing percutaneous coronary intervention.

Related Concept Videos
 01:18
Anticoagulant Drugs: Vitamin K Antagonists and Direct Oral Anticoagulants
Warfarin, a prominent vitamin K antagonist family member, exerts its effect by inhibiting the enzyme VKORC1 (vitamin K epoxide reductase complex 1). By hindering this enzyme, warfarin...
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:29
Venous Thrombosis III: Interprofessional Care
 01:20
Antiplatelet Drugs: Prostaglandin Synthesis, P2Y12 and Glycoprotein IIb/IIIa Inhibitors
Prostaglandin synthesis inhibitors, exemplified by the widely known aspirin, wield their power by irreversibly acetylating...
 01:30
Venous Thrombosis IV: Nursing Management
 01:25
Antianginal Drugs: Calcium Channel Blockers and Ranolazine
CCBs, a diverse class that includes dihydropyridines (nifedipine) and diphenylalkylamines (verapamil and diltiazem), exert their effect by blocking calcium channels in cardiac and smooth muscle cells. This...