Related Experiment Video
Updated: Apr 21, 2026


An Obstructive Chronic Pancreatitis Model Established Through Electrocoagulation
Published on: October 31, 2025
Genetic and electrophysiological characteristics of recurrent acute pancreatitis
Steven Werlin1, Fred M Konikoff, Zamir Halpern
1*Medical College of Wisconsin, Milwaukee †Hadassah Hebrew University Medical Center, Jerusalem ‡Meir Medical Center, Kfar-Saba §Souraski Medical Center, Tel-Aviv ||Soroka Medical Center, Ben Gurion University of the Negev, Beer-Sheva ¶Assaf Harofe Medical Center, Tzrifin #Schneider Children's Medical Center, Petach-Tikva **Meyer Children's Medical Center, Haifa, Israel ††Beaujon Hospital, Clichy ‡‡CHU de Brest, Brest, France.

Objectives:
The aim was to present the workup of patients with acute recurrent pancreatitis (ARP) for genetic analysis and electrophysiological testing.
Methods:
Patients with ARP with unknown etiology were referred for genetic testing and evaluation of cystic fibrosis transmembrane conductor regulator (CFTR) function by nasal potential difference (NPD) testing.
Results:
A total of 67 patients were evaluated. The mean age was 23 ± 17 years (median 17.0 years, range 1.5-72 years); 90% were Jewish and 10% Arab. Ten (15%) patients carried PRSS1 gene mutation (K23R(7), R122H(2), and D21A(1)). One patient had K172E/- (chymotrypsin C [CTRC]) mutation, 1 had I42M (serine protease inhibitor Kazal type 1 [SPINK1])/V235I (CTRC) together with ΔF508/5T, 1 patient had R67H (SPINK1)/V235I (CTRC), and 1 patient had V235I (CTRC)/-. Ten of 67 (15%) patients submitted for CFTR gene testing carried mutations (ΔF508/L997F, ΔF508/5T(11TG), W1282/5T(12TG), W1282X/Y1014C, ΔF508/R31C, R117H/-, R117H/Y1014C, D1152H/-, 5T(11TG)/-, and L997F/-). Fifty-four (80%) patients underwent sweat testing. Of these, 5 had sweat chloride ≥60 mEq/L, and 22 patients had sweat chloride from 40 to 60 mEq/L. Of the 56 (83%) patients had nasal potential difference testing, 4 (6%) with abnormal results.
Conclusions:
One-third (34%) of patients with ARP carry mutations for hereditary pancreatitis including rare mutations (K23R), and 12.5% have evidence of cftr mutations and 10% had CFTR dysfunction underscoring the importance of genetic and functional workup of these patients.


Related Concept Videos
 01:21
Chronic Pancreatitis II: Pathophysiology
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
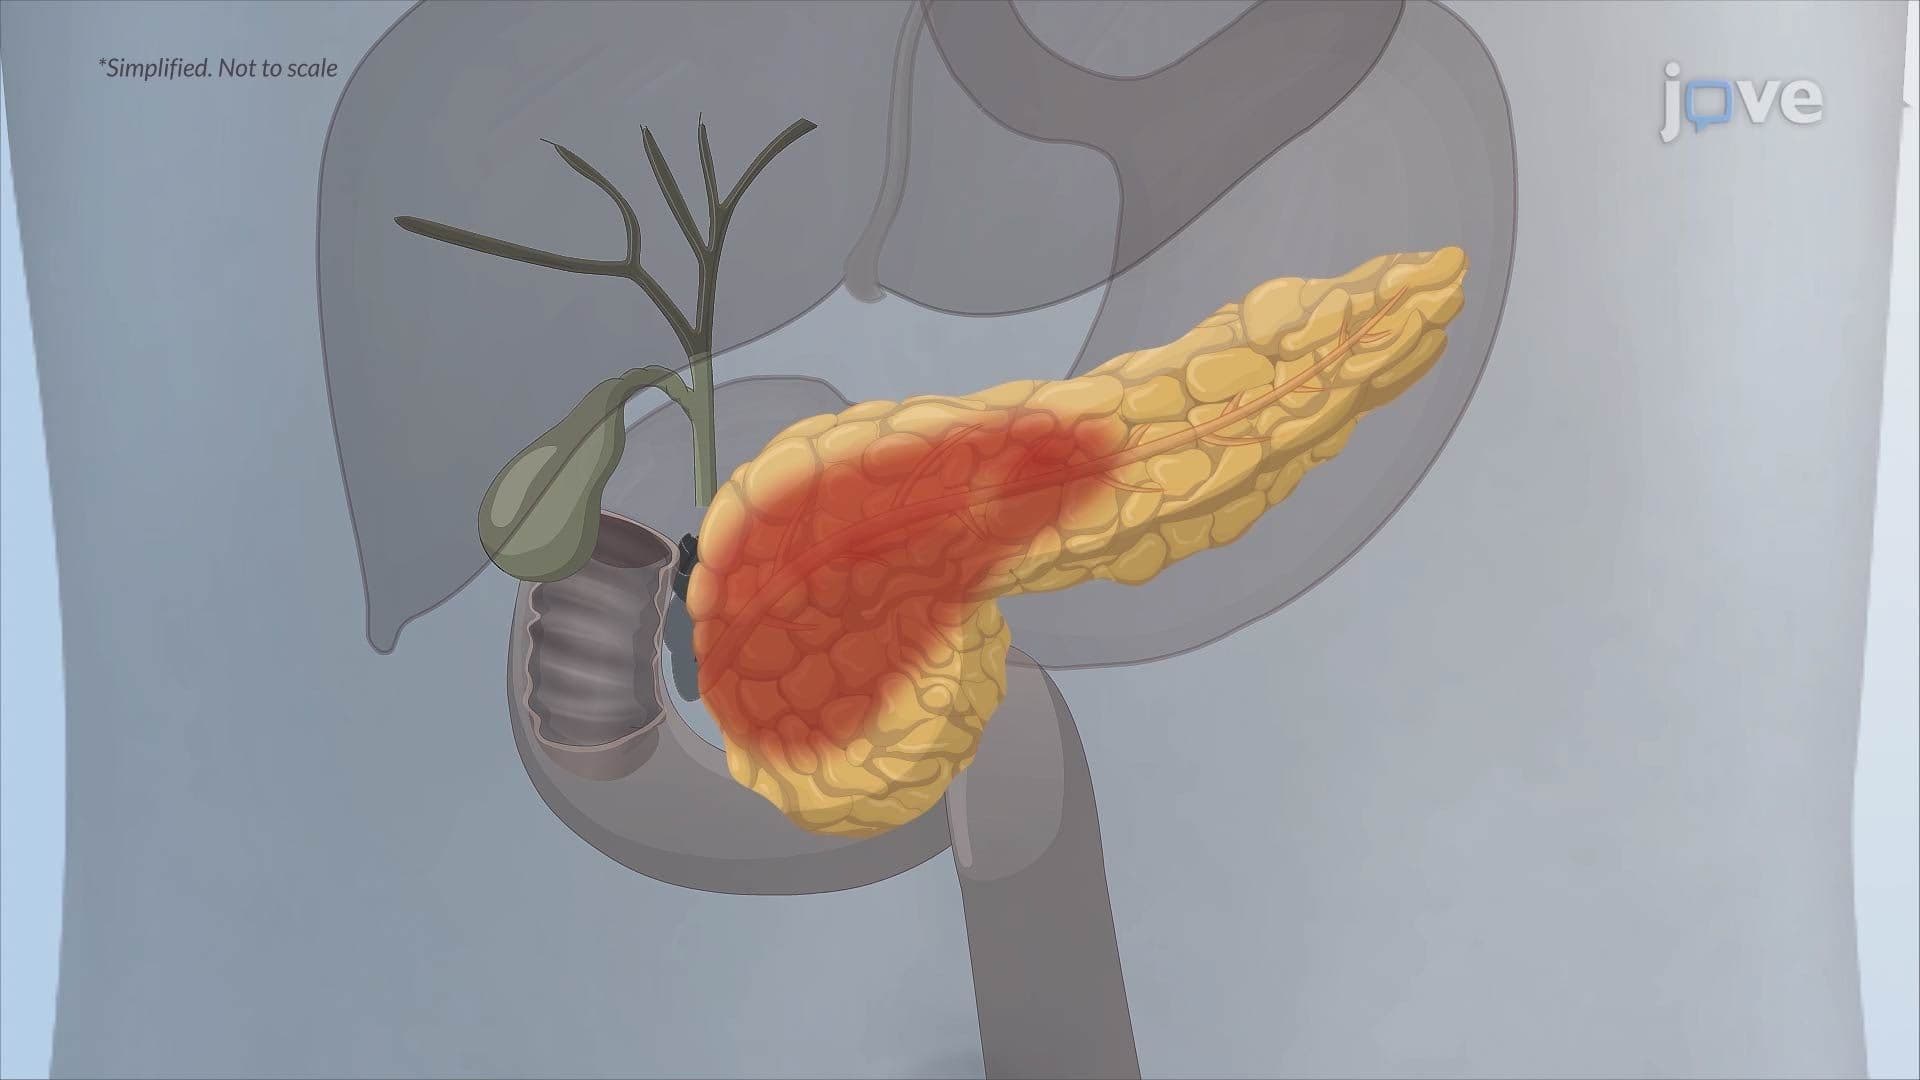
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include: