Related Experiment Video
Updated: Apr 21, 2026


Quantification of Levator Ani Hiatus Enlargement by Magnetic Resonance Imaging in Males and Females with Pelvic Organ Prolapse
Published on: April 17, 2019
Dutch evidence statement for pelvic physical therapy in patients with anal incontinence
L C M Berghmans1, J A M Groot, I C van Heeswijk-Faase
1Pelvic Care Center Maastricht, Maastricht University Medical Centre (MUMC), P.O. Box 5800, 6202 AZ, Maastricht, The Netherlands, bary.berghmans@maastrichtuniversity.nl.

Introduction And Hypothesis:
To promote agreement among and support the quality of pelvic physiotherapists' skills and clinical reasoning in The Netherlands, an Evidence Statement Anal Incontinence (AI) was developed based on the practice-driven problem definitions outlined. We present a summary of the current state of knowledge and formulate recommendations for a methodical assessment and treatment for patients with AI, and place the evidence in a broader perspective of current developments.
Methods:
Electronic literature searches were conducted in relevant databases with regard to prevalence, incidence, costs, etiological and prognostic factors, predictors of response to therapy, prevention, assessment, and treatment. The recommendations have been formulated on the basis of scientific evidence and where no evidence was available, recommendations were consensus-based.
Results:
The evidence statement incorporates a practice statement with corresponding notes that clarify the recommendations, and accompanying flowcharts, describing the steps and recommendations with regard to the diagnostic and therapeutic process. The diagnostic process consists of history-taking and physical examination supported by measurement instruments. For each problem category for patients with AI, a certain treatment plan can be distinguished dependent on the presence of pelvic floor dysfunction, awareness of loss of stools, comorbidity, neurological problems, adequate anorectal sensation, and (in)voluntary control. Available evidence and expert opinion support the use of education, pelvic floor muscle training, biofeedback, and electrostimulation in selected patients.
Conclusions:
The evidence statement reflects the current state of knowledge for a methodical and systematic physical therapeutic assessment and treatment for patients with AI.


Related Concept Videos
 01:26
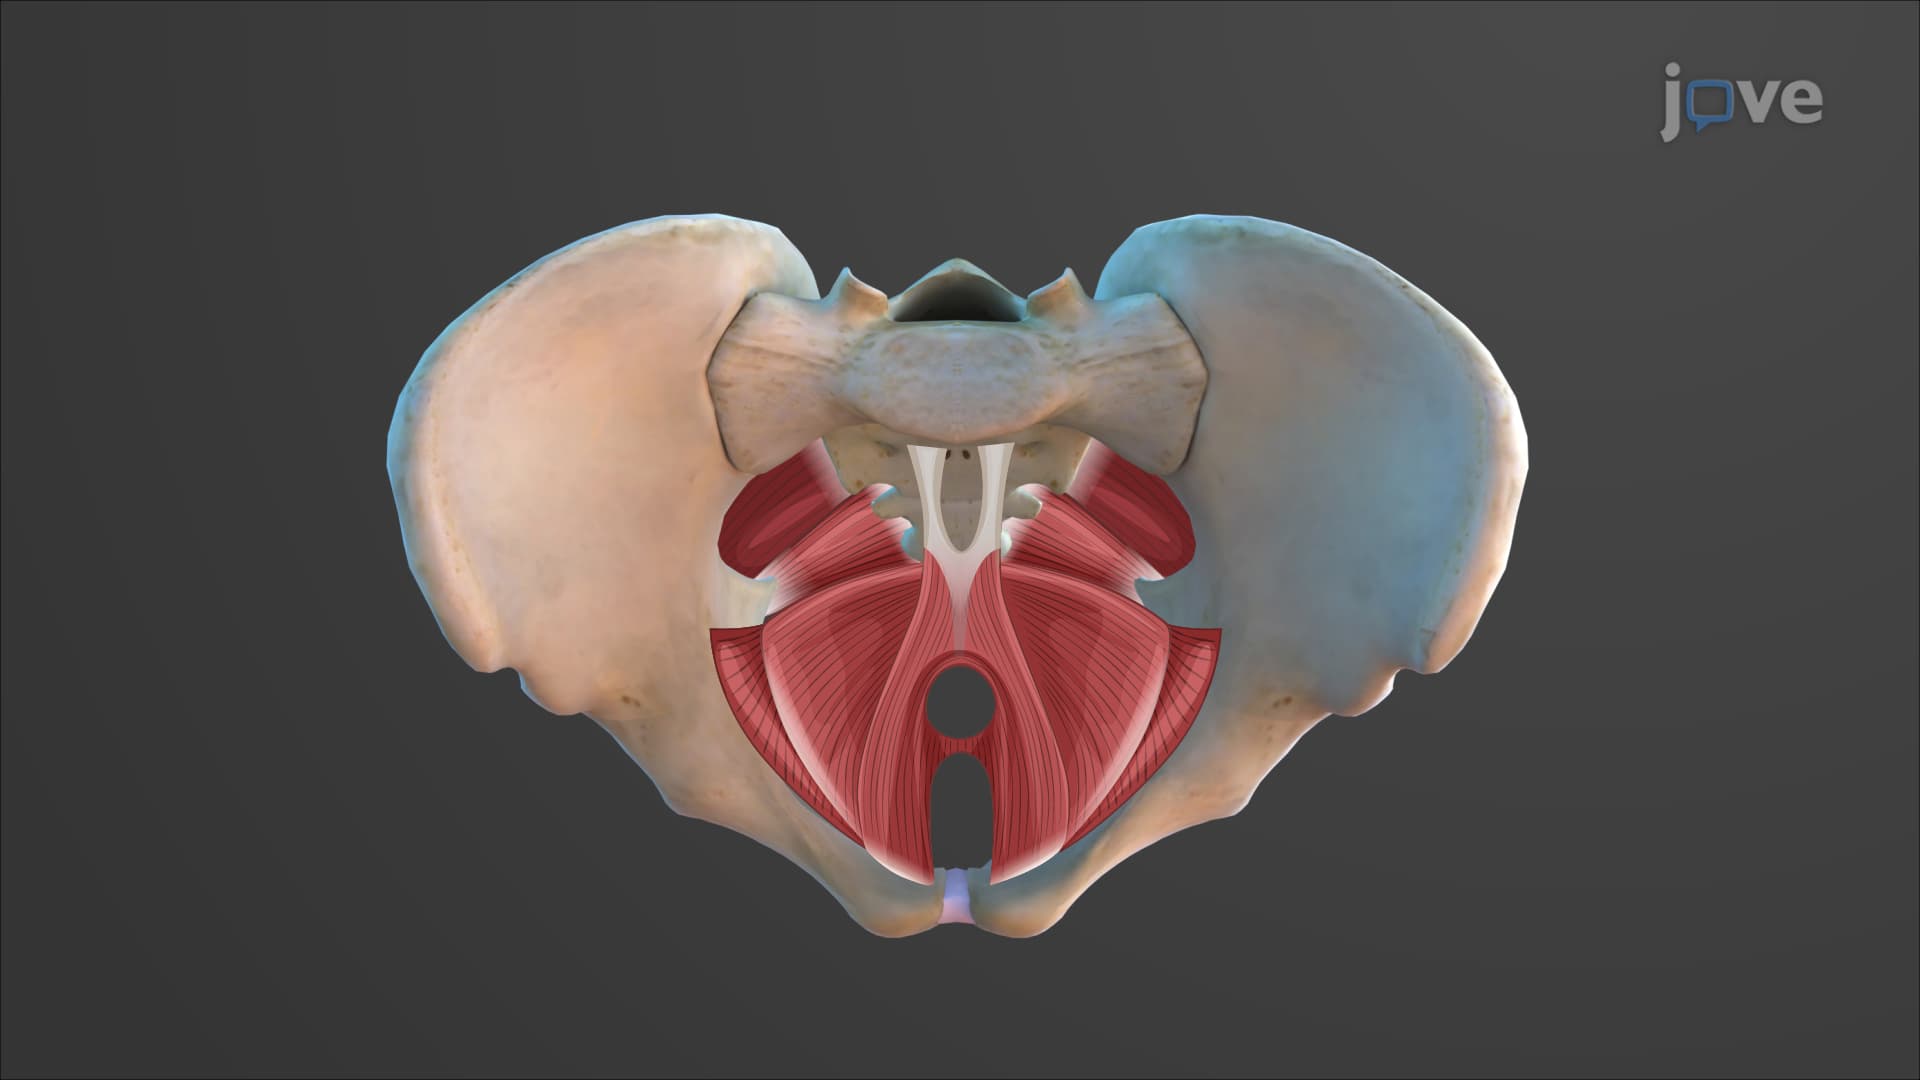
Muscles of the Pelvic Floor and Perineum
Perineal Layer
The perineum is a diamond-shaped area below the pelvic diaphragm, divided into an anterior urogenital triangle that contains the external genitals and a posterior anal triangle housing the anus. The urogenital...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:26
Psychosexual Stages of Personality: Anal
 01:24
Chest Physiotherapy
Purpose
CPT is primarily used for patients with excessive bronchial secretions who have difficulty clearing...
 01:23
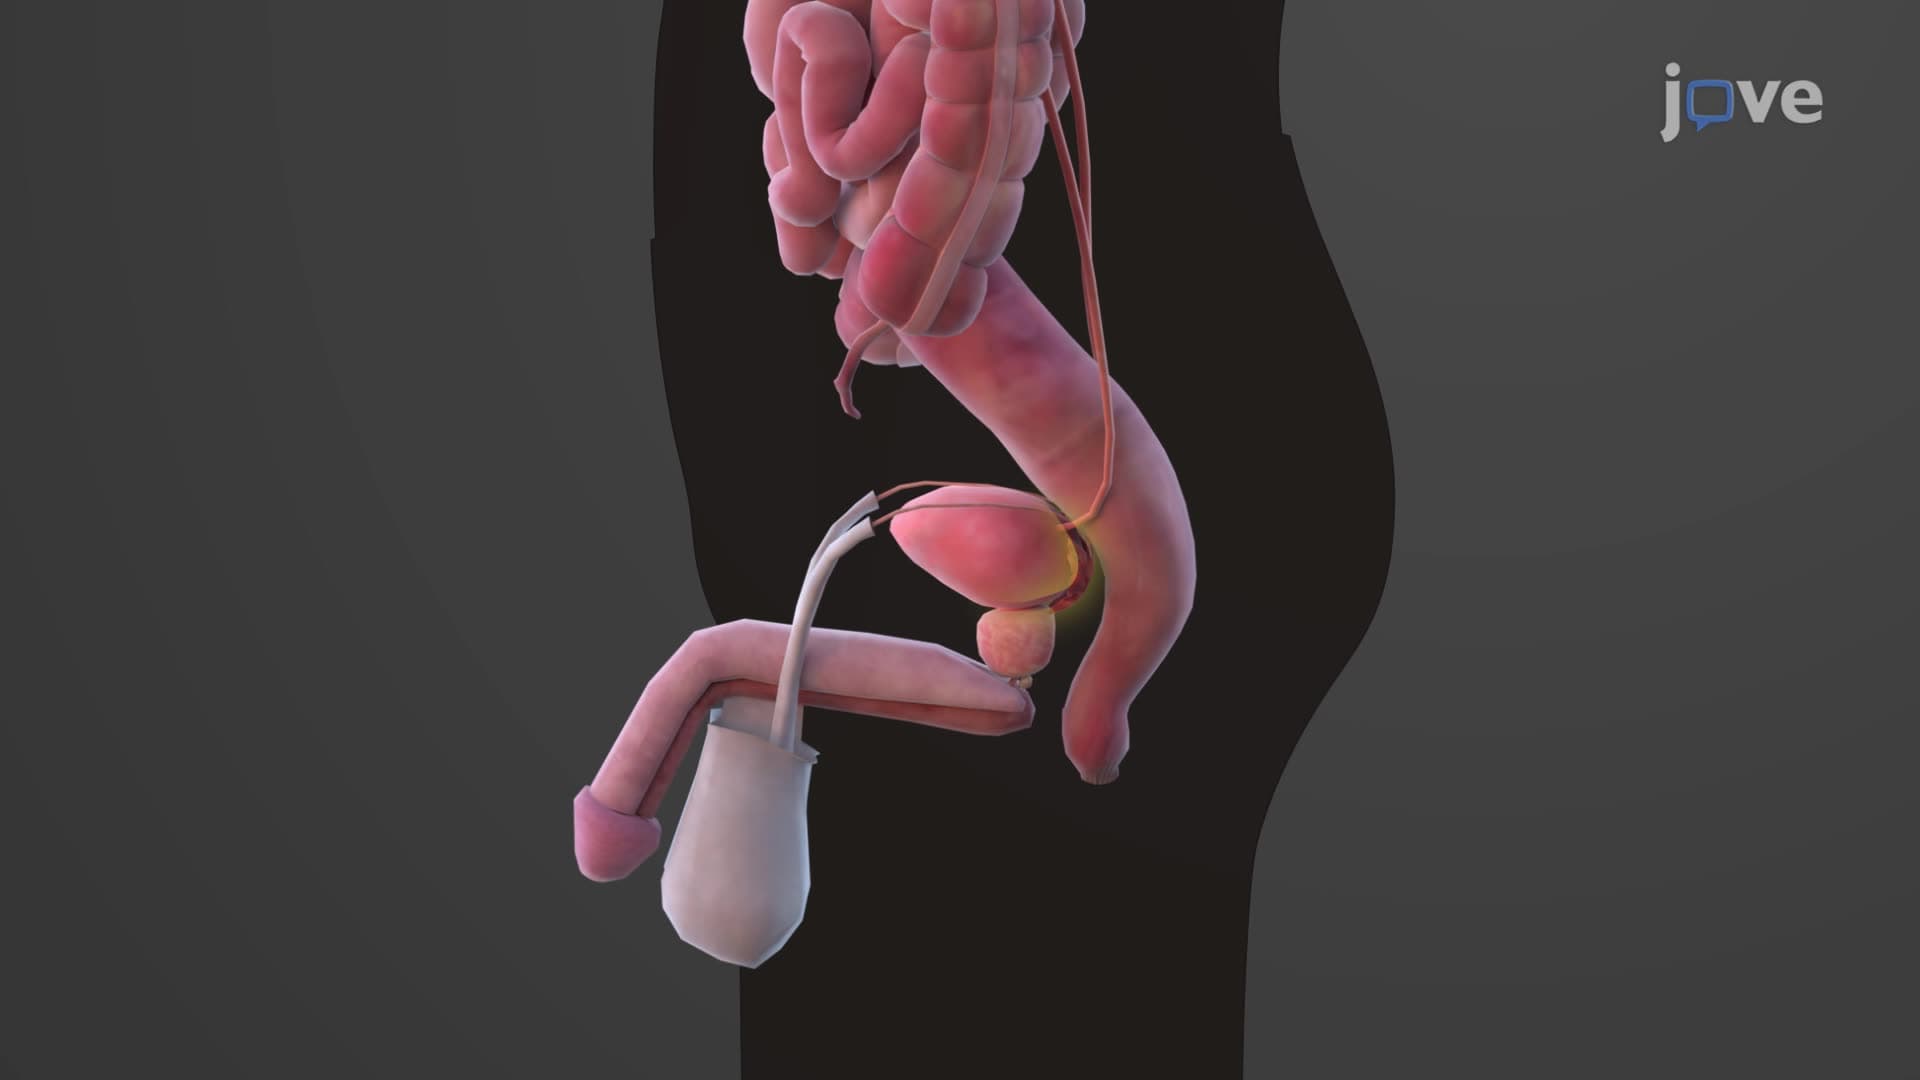
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:26
The Micturition Reflex
The process begins with bladder filling, where the bladder wall stretches as urine accumulates. This stretching activates the urine storage reflex, mediated by the sacral spinal segments and the pontine storage center. Efferent sympathetic impulses stimulate the detrusor muscle to relax and the internal urethral sphincter to contract, facilitating...