The A3 adenosine receptor: history and perspectives
Related Experiment Video
Updated: Apr 21, 2026

Author Spotlight: Advancing Cellular and Protein Engineering to Control Biological Functions and Develop Novel Therapies
Published on: September 27, 2024
Pier Andrea Borea1, Katia Varani2, Fabrizio Vincenzi1
1Department of Medical Sciences, Pharmacology Section (P.A.B., K.V., F.V., S.M., S.G.), and Department of Pharmaceutical Sciences, University of Ferrara, Italy (P.G.B., M.A.T.).

Abstract:
By general consensus, the omnipresent purine nucleoside adenosine is considered a major regulator of local tissue function, especially when energy supply fails to meet cellular energy demand. Adenosine mediation involves activation of a family of four G protein-coupled adenosine receptors (ARs): A(1), A(2)A, A(2)B, and A(3). The A(3) adenosine receptor (A(3)AR) is the only adenosine subtype to be overexpressed in inflammatory and cancer cells, thus making it a potential target for therapy. Originally isolated as an orphan receptor, A(3)AR presented a twofold nature under different pathophysiologic conditions: it appeared to be protective/harmful under ischemic conditions, pro/anti-inflammatory, and pro/antitumoral depending on the systems investigated. Until recently, the greatest and most intriguing challenge has been to understand whether, and in which cases, selective A(3) agonists or antagonists would be the best choice. Today, the choice has been made and A(3)AR agonists are now under clinical development for some disorders including rheumatoid arthritis, psoriasis, glaucoma, and hepatocellular carcinoma. More specifically, the interest and relevance of these new agents derives from clinical data demonstrating that A(3)AR agonists are both effective and safe. Thus, it will become apparent in the present review that purine scientists do seem to be getting closer to their goal: the incorporation of adenosine ligands into drugs with the ability to save lives and improve human health.
More Related Videos

Related Concept Videos
 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase...
 01:17
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline...
 01:27
Adrenergic Receptors (Adrenoceptors): Classification
α-Adrenoceptors
α-Adrenoceptors are classified into two main subtypes: α1 and α2. The α1 adrenoceptors,...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...
 01:16
Adrenergic Agonists: Chemistry and Structure-Activity Relationship
Aromatic ring substitutions: Substituting the aromatic ring with –OH groups at positions 3 and 4 yields catecholamines (e.g., epinephrine), which have a high affinity for adrenoceptors. Hydrogen bonding between –OH groups and receptors enhances adrenergic activity.
Separation of...
 01:26
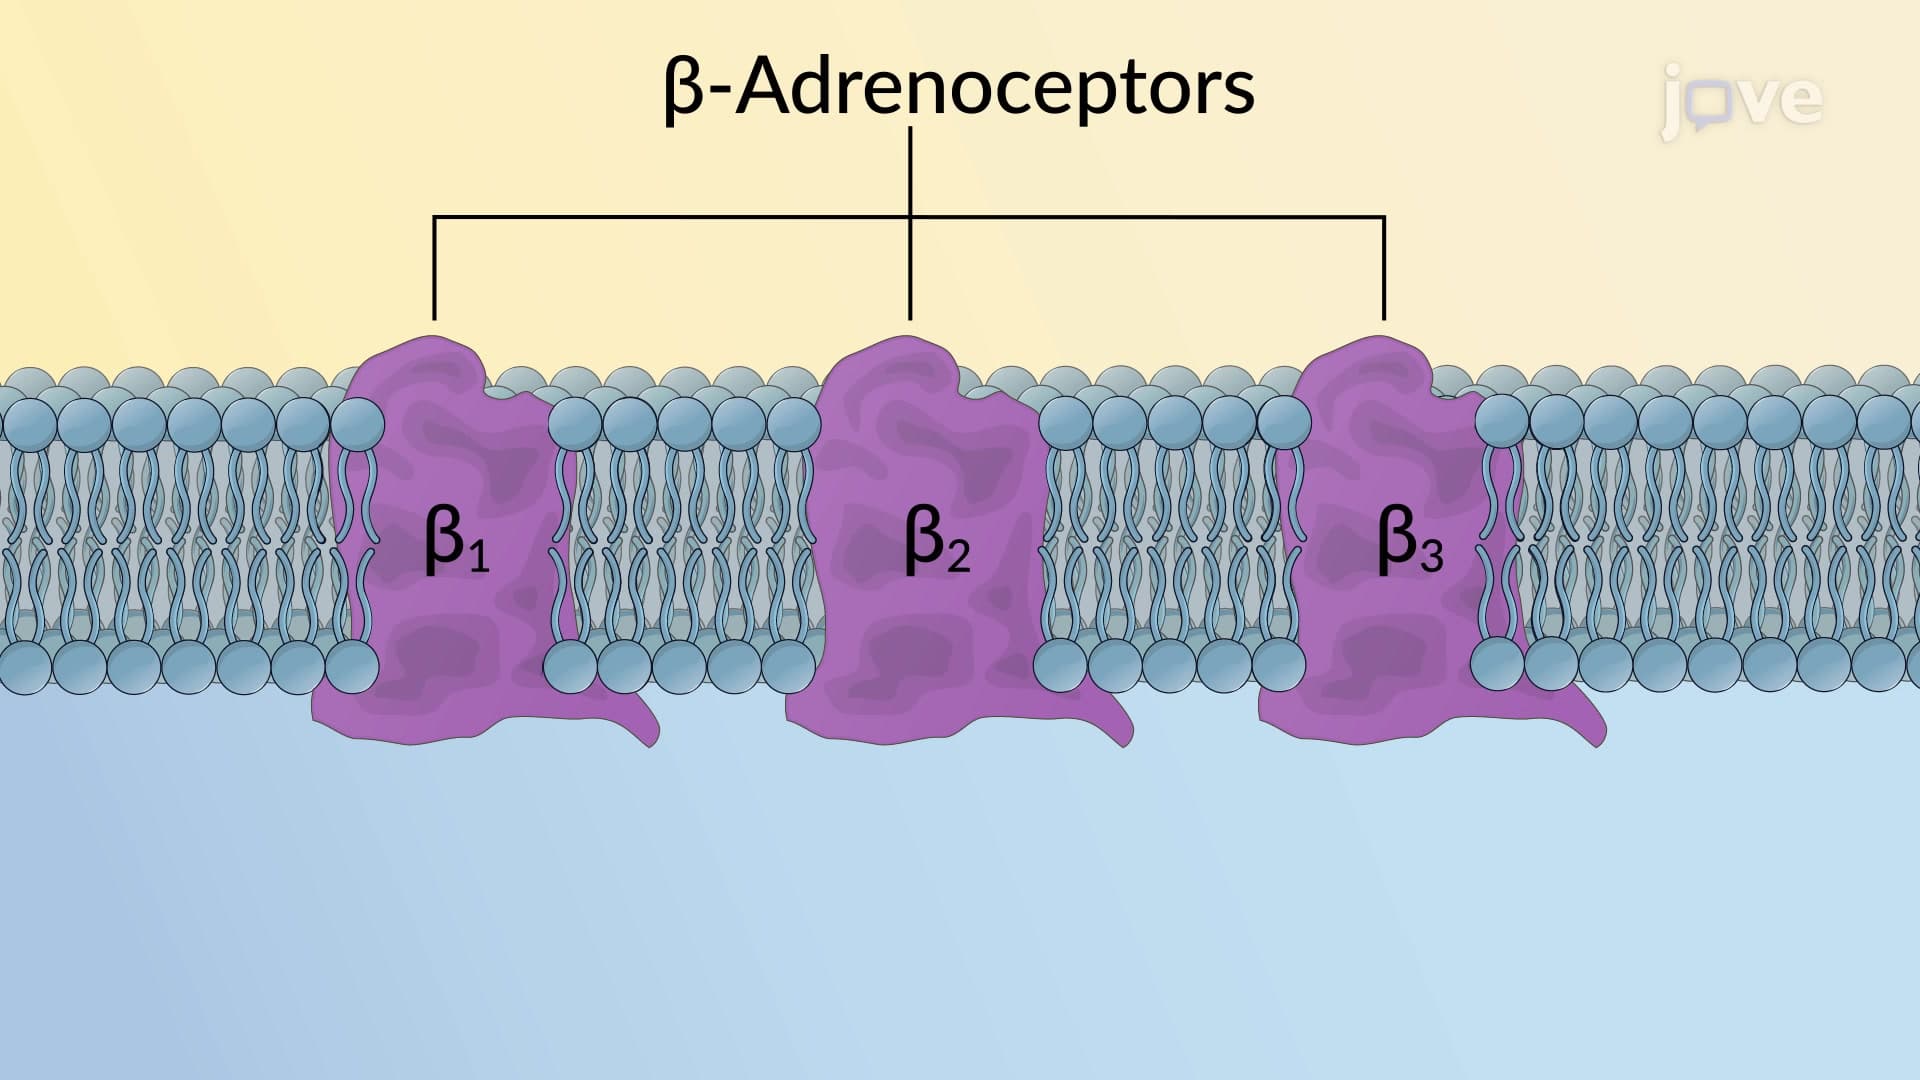
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors...