Related Experiment Video
Updated: Apr 20, 2026
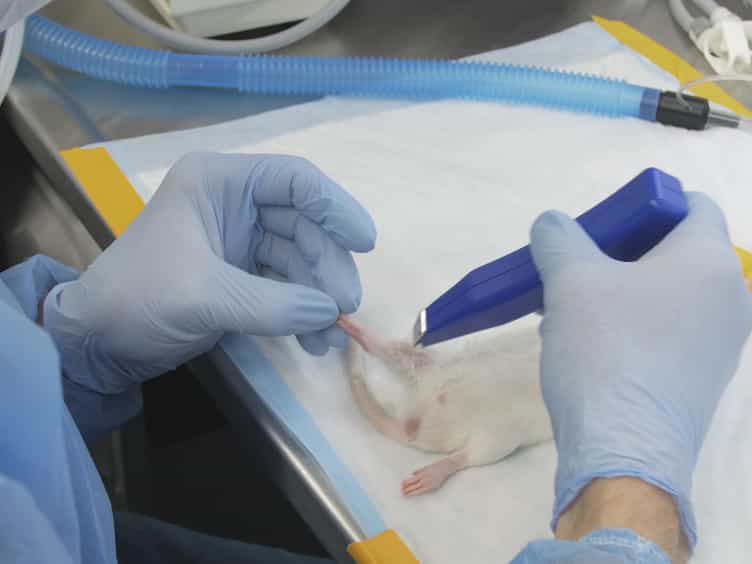
A Rat Tibial Growth Plate Injury Model to Characterize Repair Mechanisms and Evaluate Growth Plate Regeneration Strategies
Published on: July 4, 2017
[Growth behavior after epiphyseal plate injury: importance of "watertight" osteosynthesis]
1-, Badenerstr. 6, 5445, Eggenwil, Schweiz, lutzvl@bluewin.ch.

Background:
The frequency figures for epiphyseal plate injuries of long bones given in the literature are inexact and they probably occur with a frequency of 15% of all fractures of the growing skeleton. In order to be able to give correct figures in the future a classification system, such as the LiLa classification should be used, which does not attempt to be oriented to an assumed growth prognosis but is oriented to therapy and makes a strict differentiation between shaft and joint fractures. For epiphyseal joint fractures a differentiation must be made between those where the epiphysis is still open and those where the epiphysis has begun to close, in order to be able to incorporate all epiphyseal joint fractures and differentiate them from epiphyseal shaft fractures (epiphysiolysis).
Clinical Aspects:
The growth prognosis encompasses stimulatory and inhibitory growth disorders as well as spontaneous correction of residual axial deviations. The prognosis is fundamentally dependent on the biological age of the patient by fracture, on the localization in the skeleton and the localization in the segment because the growth components of epiphyses are asymmetrically distributed in the segment. Stimulatory growth disorders in the actual growth phase < 10 years of age are the obligatory growth disorders which lead to overgrowth of the section of the skeleton affected. In an age over 10 years they lead to an also obligatory premature closure of adjacent or affected epiphyses which is expressed as a slight shortening. Asymmetrical stimulations are most common in the upper extremities following intra-articular fractures of the radial condyle as the obligatory growth disorder at this site. Asymmetrical stimulation is rare in the lower extremities after extra-articular metaphyseal valgus fractures of the proximal and distal tibia. Asymmetrical premature closure of the epiphysis in the upper extremities is rare in contrast to partial stimulation with less than 5% after extra-articular fractures of the distal radius and proximal humerus. Conversely, asymmetrical inhibitory growth disorders are found significantly more often in the lower extremities after extra-articular and intra-articular fractures of the distal femur, proximal tibia and distal tibia between 50% and 20%. "Spontaneous corrections" of residual axial deviations and side to side shifts after epiphyseal shaft fractures occur reliably without resulting in growth disorders, provided the patient is young enough.
Therapeutic Targets:
In cases of displacement the aim of therapy in epiphyseal shaft fractures is to reconstitute age-related and tolerable axes. For displaced epiphyseal joint fractures the aim is to reconstruct the joint surfaces. The basic principles of an efficient and targeted diagnostics and the therapeutic options for diminishing the clinical sequelae of growth disorders are discussed.
Conclusion:
No growth disorders, which are to be expected as a result of every epiphyseal injury, can primarily be therapeutically avoided; however, better foundations can be achieved to reduce the clinical sequelae of growth disorders. Therapy can only follow the differentiation into shaft and joint (and not an assumed growth prognosis) and should integrate a scientifically proven and reasonable spontaneous correction for the patient. A classification must achieve a therapy-related uncoupling of the epiphyseal injuries into shaft and joint fractures.
More Related Videos
 07:35
Creating Rigidly Stabilized Fractures for Assessing Intramembranous Ossification, Distraction Osteogenesis, or Healing of Critical Sized Defects
Published on: April 11, 2012
 06:38
Establishment of a Segmental Femoral Critical-size Defect Model in Mice Stabilized by Plate Osteosynthesis
Published on: October 12, 2016
Related Concept Videos
 01:27
Fractures: Bone Repair
Minor fractures with no bone displacement are treated by immobilizing the fractured bone using a cast or splint. However, in the case of fractures with displaced bones, the broken bones are repositioned before immobilization to ensure successful healing without deformation and loss of function. The realignment of fractured bone ends is performed through a process called reduction. If the...
 01:24
Bone Formation by Endochondral Ossification
 01:27
Growth of Cartilage and Bone Tissue
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...