Related Experiment Video
Updated: Apr 20, 2026


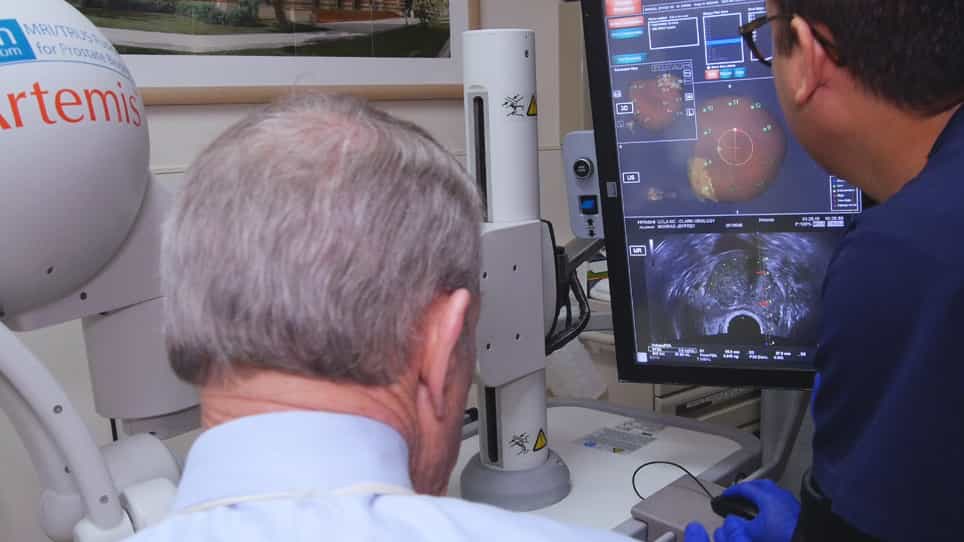
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
How accurate is multiparametric MR imaging in evaluation of prostate cancer volume?
Flavie Bratan1, Christelle Melodelima, Rémi Souchon
1From the Departments of Urinary and Vascular Radiology (F.B., O.R.), Pathology (F.M.), and Urology (S.C., M.C., A.G.), Hospices Civils de Lyon, Hôpital Edouard Herriot, 5 place d'Arsonval, 69437 Lyon Cedex 03, France; Université de Lyon, Lyon, France (F.B., S.C., M.C., O.R.); Université Lyon 1, Faculté de Médecine Lyon Est, Lyon, France (F.B., S.C., M.C., O.R.); Inserm, U1032, LabTau, Lyon, France (F.B., R.S., A.H.D., S.C., A.G., O.R.); Laboratoire d'Ecologie Alpine, Université Joseph Fourier, Grenoble, France (C.M.); and CNRS, UMR 5553, Grenoble, France (C.M.).

Purpose:
To assess the factors influencing multiparametric (MP) magnetic resonance (MR) imaging accuracy in estimating prostate cancer histologic volume (Vh).
Materials And Methods:
A prospective database of 202 patients who underwent MP MR imaging before radical prostatectomy was retrospectively used. Institutional review board approval and informed consent were obtained. Two independent radiologists delineated areas suspicious for cancer on images (T2-weighted, diffusion-weighted, dynamic contrast material-enhanced [DCE] pulse sequences) and scored their degree of suspicion of malignancy by using a five-level Likert score. One pathologist delineated cancers on whole-mount prostatectomy sections and calculated their volume by using digitized planimetry. Volumes of MR true-positive lesions were measured on T2-weighted images (VT2), on ADC maps (VADC), and on DCE images [VDCE]). VT2, VADC, VDCE and the greatest volume determined on images from any of the individual MR pulse sequences (Vmax) were compared with Vh (Bland-Altman analysis). Factors influencing MP MR imaging accuracy, or A, calculated as A = Vmax/Vh, were evaluated using generalized linear mixed models.
Results:
For both readers, Vh was significantly underestimated with VT2 (P < .0001, both), VADC (P < .0001, both), and VDCE (P = .02 and P = .003, readers 1 and 2, respectively), but not with Vmax (P = .13 and P = .21, readers 1 and 2, respectively). Mean, 25th percentile, and 75th percentile, respectively, for Vmax accuracy were 0.92, 0.54, and 1.85 for reader 1 and 0.95, 0.57, and 1.77 for reader 2. At generalized linear mixed (multivariate) analysis, tumor Likert score (P < .0001), Gleason score (P = .009), and Vh (P < .0001) significantly influenced Vmax accuracy (both readers). This accuracy was good in tumors with a Gleason score of 7 or higher or a Likert score of 5, with a tendency toward underestimation of Vh; accuracy was poor in small (<0.5 cc) or low-grade (Gleason score ≤6) tumors, with a tendency toward overestimation of Vh.
Conclusion:
Vh can be estimated by using Vmax in aggressive tumors or in tumors with high Likert scores.

Related Concept Videos
 01:27
Imaging Studies IV: Magnetic Resonance Imaging
 01:24
Magnetic Resonance Imaging