Related Experiment Video
Updated: Apr 20, 2026

Magnetic Resonance Elastography Methodology for the Evaluation of Tissue Engineered Construct Growth
Published on: February 9, 2012
Shear-wave elastography of the breast: value of a quality measure and comparison with strain elastography
1From the Department of Radiology, Northeastern Ohio Medical University, Rootstown, Ohio (R.G.B.); Radiology Consultants Inc, 7623 Market St, Boardman, OH 44512 (R.G.B.); and Department of Biostatistics and Center for Statistical Sciences, Brown University, Providence, RI (Z.Z.).

Purpose:
To determine whether addition of quality measure (QM) of shear-wave (SW) velocity (Vs) estimation can increase SW elastography sensitivity for breast cancer.
Materials And Methods:
With written informed consent, this institutional review board-approved, HIPAA-compliant study included 143 women (mean age, 48.5 years ± 8.7) scheduled for breast biopsy. Mean lesion size was 16.4 mm ± 11.8; 95 (66%) lesions were benign; 48 (34%), malignant. If more than one lesion was present, lesion with highest Breast Imaging Reporting and Data System (BI-RADS) category was chosen. If there were more than one with highest BI-RADS category, a lesion was randomly selected. Conventional ultrasonography (US), strain elastography, and SW elastography were performed with QM. QM assesses SW quality to provide accurate Vs. Lesions were evaluated for Vs and QM (high or low). Lesions with Vs of less than 4.5 m/sec were classified benign; lesions with Vs of 4.5 m/sec or greater, malignant. Results were correlated with pathologic findings. Vs data with or without incorporating QM were used to determine SW elastography diagnostic performance. Binomial proportions and exact 95% confidence intervals (CIs) were calculated.
Results:
In 95 benign lesions, 13 (14%) had no SW elastography signal; 77 (81%), Vs of less than 4.5 m/sec; and five (5%), Vs of 4.5 m/sec or greater. In 48 malignant lesions, eight (17%) had no SW elastography signal; 20 (42%), Vs of less than 4.5 m/sec; and 20 (42%), V of 4.5 m/sec or greater. QM was low in 17 of 20 (85%) malignant lesions with Vs of less than 4.5 m/sec. Without QM, using Vs of 4.5 m/sec or greater as test positive, SW elastography had lesion-level sensitivity of 50% (95% CI: 34%, 66%); specificity, 94% (95% CI: 86%, 98%); positive predictive value (PPV), 80% (95% CI: 59%, 93%); and negative predictive value (NPV), 79% (95% CI: 70%, 87%). Using QM where additional lesions with both low Vs and low QM were treated as test positive, SW elastography had lesion-level sensitivity of 93% (95% CI: 80%, 98%); specificity, 89% (95% CI: 80%, 95%); PPV, 80% (95% CI: 66%, 91%); and NPV, 96% (95% CI: 89%, 99%).
Conclusion:
Addition of QM can improve SW elastography sensitivity, with no significant change in specificity.
More Related Videos
 11:50
High-frequency High-resolution Echocardiography: First Evidence on Non-invasive Repeated Measure of Myocardial Strain, Contractility, and Mitral Regurgitation in the Ischemia-reperfused Murine Heart
Published on: July 9, 2010
 09:05
Transthoracic Speckle Tracking Echocardiography for the Quantitative Assessment of Left Ventricular Myocardial Deformation
Published on: October 20, 2016
Related Concept Videos
 01:20
Elastic Strain Energy for Shearing Stresses
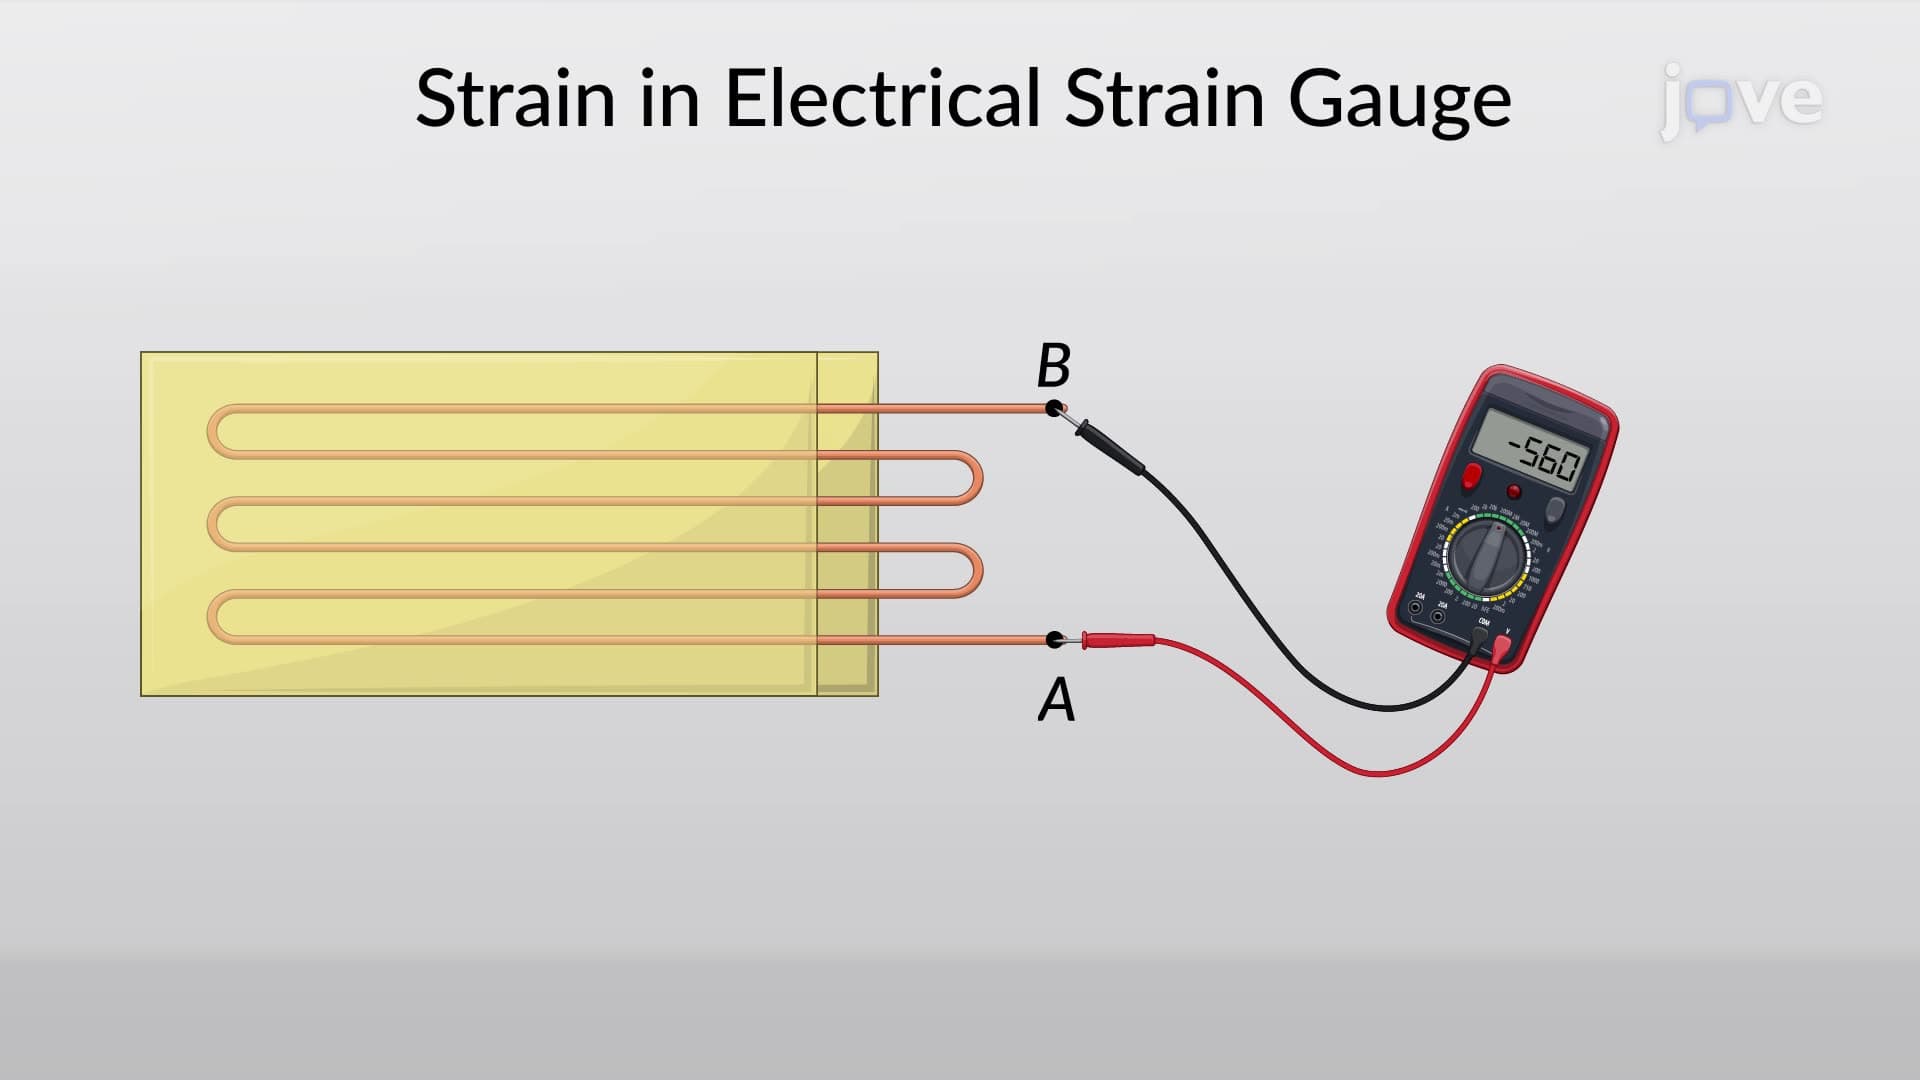 01:27
Measurements of Strain
 01:20
Shearing Strain
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
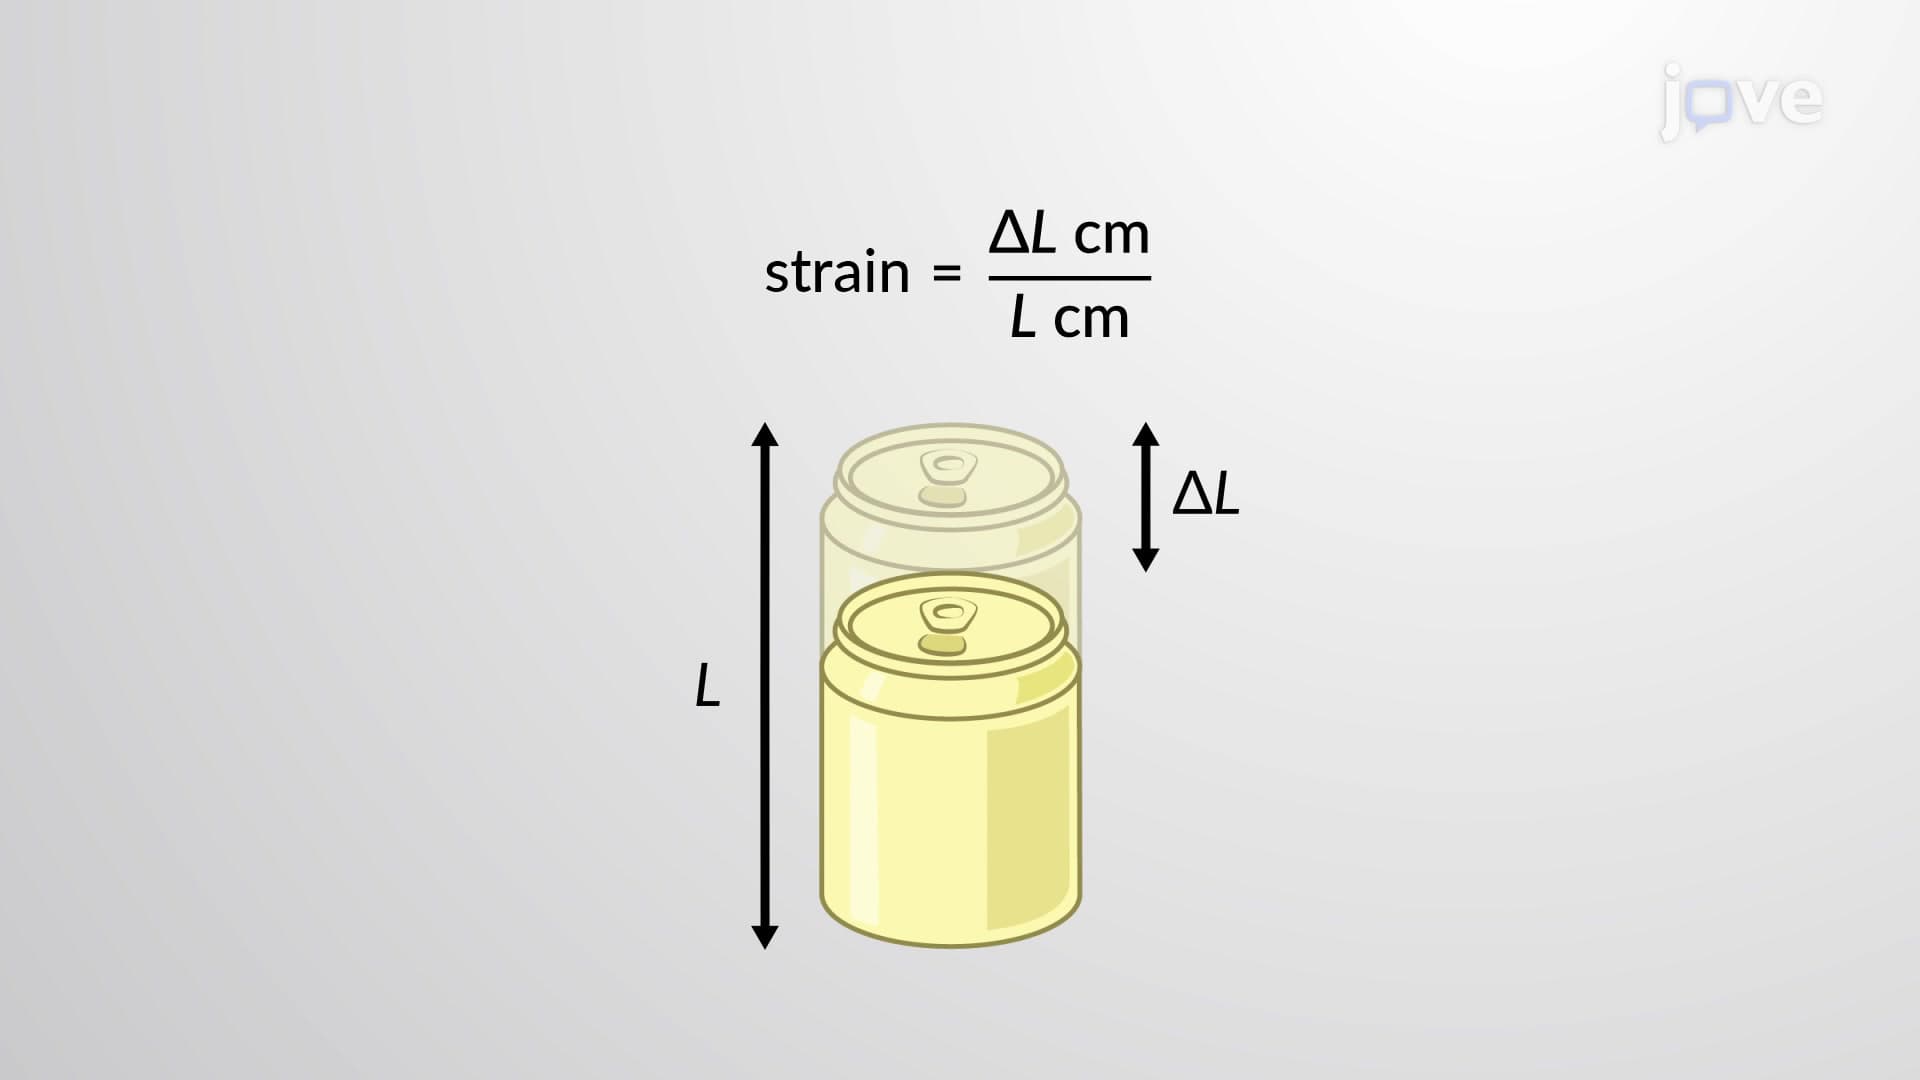 01:15
Strain and Elastic Modulus
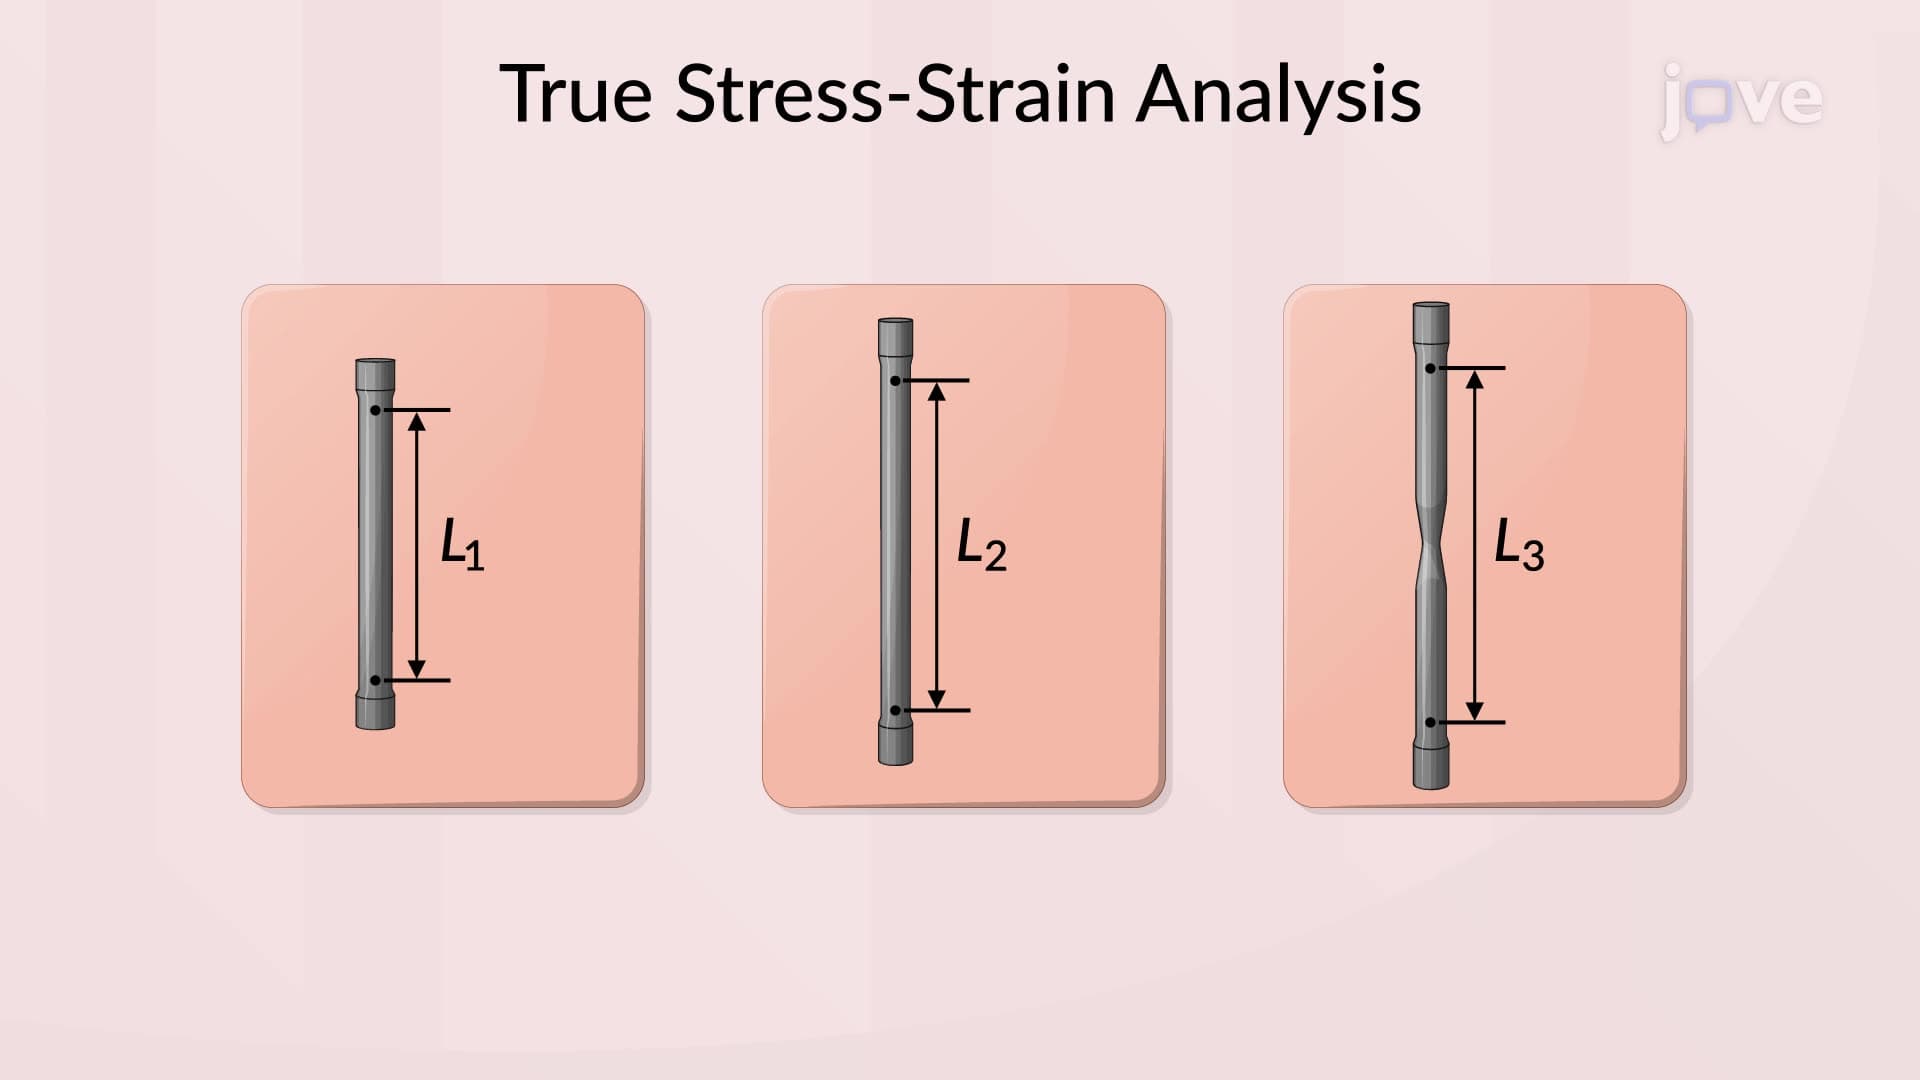 01:28
True Stress and True Strain
In contrast, true stress offers a more precise portrayal. It is computed by dividing the...