Related Experiment Video
Updated: Apr 20, 2026

Diagnosis of Hirschsprung's Disease by Immunostaining Rectal Suction Biopsies for Calretinin, S100 Protein and Protein Gene Product 9.5
Published on: April 26, 2019
Overcoming the barriers to diagnosis of Morquio A syndrome
Kaustuv Bhattacharya1, Shanti Balasubramaniam2, Yew Sing Choy3
1Genetic Metabolic Disorders Service, The Children's Hospital at Westmead, Hawkesbury Rd & Hainsworth St, Westmead, Sydney, NSW, Australia. kaustuv.bhattacharya@health.nsw.gov.au.

Background:
Morquio A syndrome is an autosomal recessive lysosomal storage disease often resulting in life-threatening complications. Early recognition and proficient diagnosis is imperative to facilitate prompt treatment and prevention of clinical complications.
Methods:
Experts in Asia Pacific reviewed medical records focusing on presenting signs and symptoms leading to a diagnosis of Morquio A syndrome.
Results:
Eighteen patients (77% female) had a mean (median; min, max) age of 77.1 (42.0; 0.0, 540.0) months at symptom onset, 78.9 (42.0; 4.5, 540.0) months at presentation and 113.8 (60.0; 7.0, 540.0) months at diagnosis. Orthopedic surgeons and pediatricians were most frequently consulted pre-diagnosis while clinical geneticists/metabolic specialists most frequently made the diagnosis. Delayed diagnoses were due to atypical symptoms for 5 patients (28%), while 4 patients (22%) experienced each of subtle symptoms, symptoms commonly associated with other diseases, or false-negative urine glycosaminoglycan analysis. Two patients (11%) each experienced overgrowth within the first year of life. Two patients with Morquio A syndrome (11%) were diagnosed with craniosynostosis and 1 (6%) for each of Legg-Calvé-Perthes disease, Leri-Weill syndrome, and pseudoachondroplasia. Early radiographic features of Morquio A syndrome led to more efficient diagnosis.
Conclusions:
Increased awareness of clinical symptomology overlapping with Morquio A syndrome is essential. Clinicians encountering patients with certain skeletal dysplasia should consider Morquio A syndrome in their differential diagnosis. Atypical or subtle symptoms should not eliminate Morquio A syndrome from the differential diagnosis, especially for patients who may have non-classical phenotype of Morquio A syndrome.


Related Concept Videos
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:30
Irritable Bowel Syndrome II: Clinical Features and Diagnostic Evaluation
Irritable Bowel Syndrome (IBS) is classified into subtypes based on the predominant bowel habits as determined by the Bristol Stool Form Scale (BSFS). The subtypes are:
 01:23
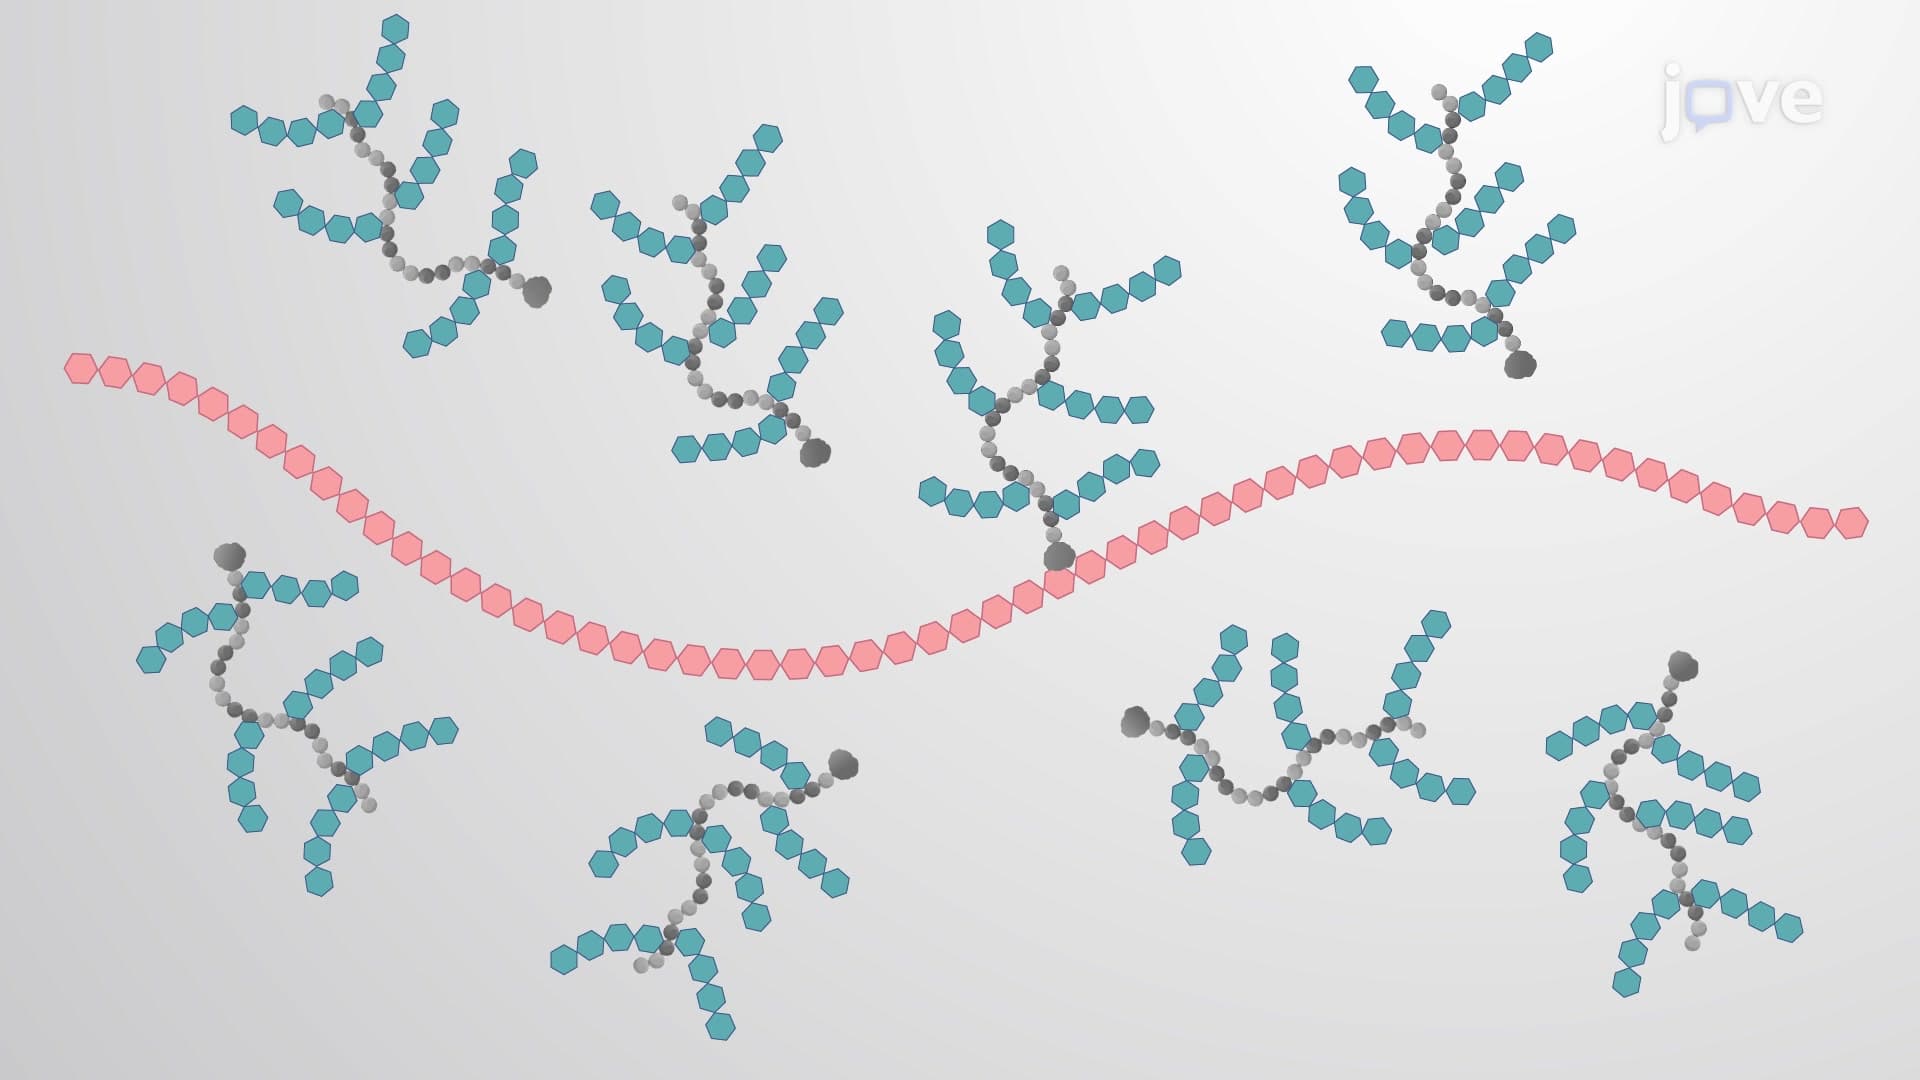
Glycosaminoglycans
GAGS are found in the extracellular matrix of vertebrates, invertebrates, and bacteria. Due to their polar nature they attract water, and serve as excellent lubricants or shock absorbers in an animal body.
Hyaluronic...