Related Experiment Video
Updated: Apr 20, 2026
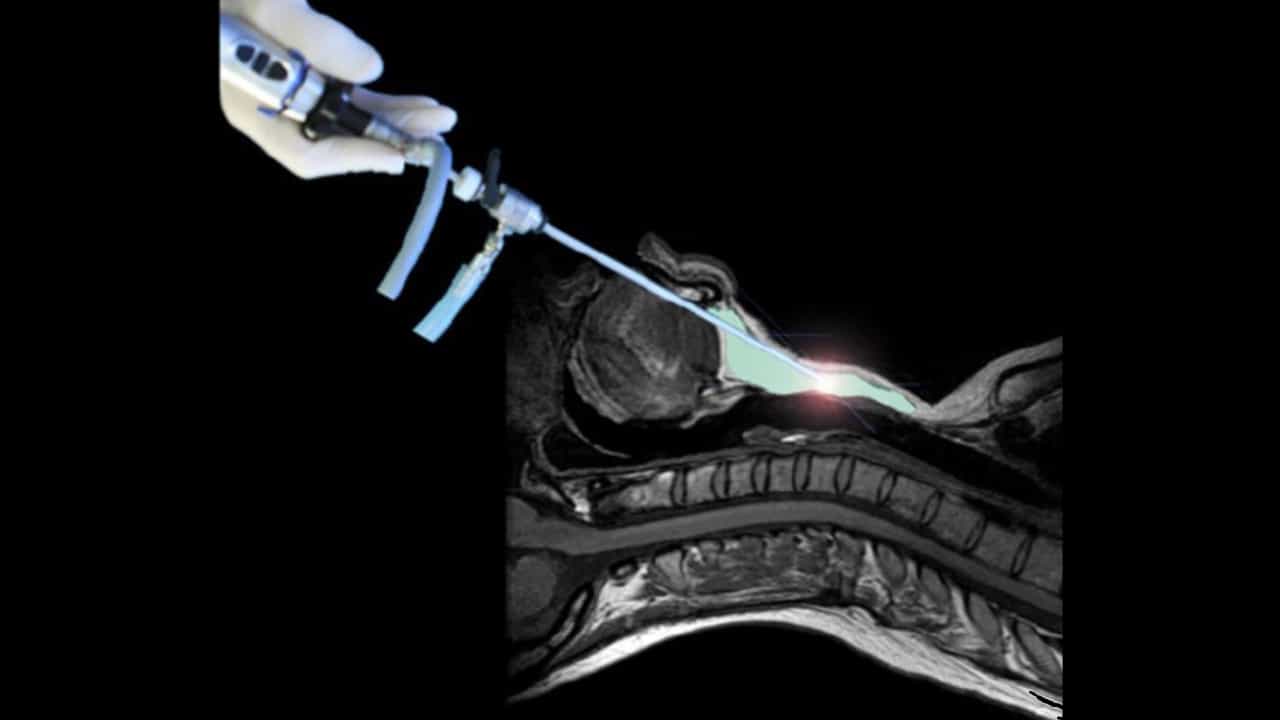

Transoral Robotic Total Thyroidectomy and Bilateral Central Regional Lymph Node Dissection for Papillary Thyroid Carcinoma
Published on: September 15, 2023
Surgical Treatment of Hashimoto's with Thyroid Microcarcinoma
Liu Tao1, H Xi-Lin2, M Xiang-Dong2
1Department of Tumor Surgery, Central Hospital of Xuzhou, Xuzhou, 221009, Jiangsu, China. liutao7802@126.com.

Abstract:
The aim of this study is to explore the surgical strategies for treating Hashimoto's disease complicated with thyroid microcarcinoma. We analyzed the clinical data of 25 patients with Hashimoto's disease with thyroid microcarcinoma who were treated in our hospital from January 1995 to September 2011. The incidence of Hashimoto's disease with thyroid microcarcinoma was 9.8 % (25/256) in our hospital. Amongst them, 19 patients had papillary thyroid carcinoma and six had follicular thyroid carcinoma. There were 24 cases (96 %) confirmed by the frozen section examination and one (4 %) after surgery. One patient did not undergo remedial surgery. The surgical approaches were determined based on preoperative examinations and intraoperative frozen pathology, including thyroid lobe and isthmus resection with contralateral lobe subtotal resection in 19 cases, and bilateral subtotal thyroid lobectomy in one case. Central lymph node dissection was conducted for all patients except one who was not diagnosed until after the surgery. No recurrence occurred during the follow-up (range: 6 months to 17 years) and all patients have survived to date. The preoperative diagnosis rate of Hashimoto's disease with thyroid cancer (in particular thyroid microcarcinomas) is low. Preoperative palpation, color Doppler ultrasound, fine needle aspiration, and the frozen section examination are helpful to improve the diagnosis rate of Hashimoto's disease with thyroid microcarcinoma. Surgery procedure is the most effective approach.
Related Concept Videos
 01:27
Hyperthyroidism II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction