Related Experiment Video
Updated: Apr 20, 2026

Simulator Training for Endovascular Neurosurgery
Published on: May 6, 2020
Practice improves performance on a coronary anastomosis simulator, attending surgeon supervision does not
Daniel H Enter1, Xiaoying Lou1, Dawn S Hui2
1Division of Cardiac Surgery, Bluhm Cardiovascular Institute of Northwestern University, Chicago, Ill.

Objectives:
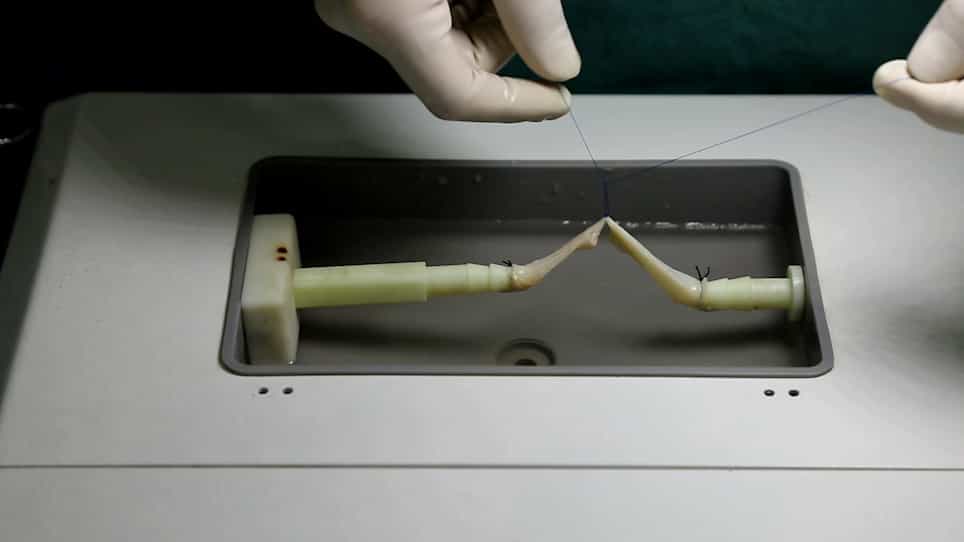
Enthusiasm for simulation early in cardiothoracic surgery training is growing, yet evidence demonstrating its utility is limited. We examined the effect of supervised and unsupervised training on coronary anastomosis performance in a randomized trial among medical students.
Methods:
Forty-five medical students were recruited for this single-blinded, randomized controlled trial using a low-fidelity simulator. After viewing an instructional video, all participants attempted an anastomosis. Subsequently, the participants were randomized to 1 of 3 groups: control (n = 15), unsupervised training (n = 15), or supervised training with a cardiothoracic surgeon or fellow (n = 15). Both the supervised and unsupervised groups practiced for 1 hour per week. After 4 weeks, the participants repeated the anastomosis. All pre- and posttraining performances were videotaped and rated independently by 3 cardiothoracic surgeons blinded to the randomization. All raters scored 13 assessment items on a 1 to 5 (low-high) scale along with an overall pass/fail rating.
Results:
After the training period, all 3 groups showed significant improvements in composite scores (control: +0.52 ± 0.69 [P = .014], unsupervised: +1.05 ± 0.48 [P < .001], and supervised: +1.10 ± 0.84 [P < .001]). Compared with control group, both supervised (P = .005) and unsupervised trainees (P = .005) demonstrated a significant improvement. Between the supervised and unsupervised groups there were no statistically significant differences in composite scores.
Conclusions:
Practice on low-fidelity simulators enabled trainees to improve on a broad range of skills; however, the additional effect of attending-level supervision is limited. In an era of increasing staff surgeon responsibilities, unsupervised practice may be sufficient for inexperienced trainees.