Related Experiment Video
Updated: Apr 20, 2026

Author Spotlight: Assessing the Cardiovascular Profile of Patients with Metabolic Syndrome
Published on: September 27, 2024
Common carotid intima-media thickness as a risk factor for outcomes in Asian patients with acute ST-elevation
Sahmin Lee1, Goo-Yeong Cho2, Hyun-Sook Kim3
1Cardiovascular Center, Seoul National University Hospital, Republic of Korea.

Insights
Carotid intima-media thickness (CIMT) predicts cardiovascular events in Asian patients with ST-elevation myocardial infarction (STEMI). Higher CIMT indicates a worse prognosis, aiding in risk stratification for these patients.
Area of Science:
- Cardiology
- Vascular Ultrasound
- Cardiovascular Disease Research
Background:
- Carotid intima-media thickness (CIMT) is a known cardiovascular disease risk factor.
- The prognostic value of CIMT in Asian patients with acute ST-elevation myocardial infarction (STEMI) was previously unclear.
Purpose of the Study:
- To investigate whether CIMT can predict the prognosis of Asian patients diagnosed with STEMI.
- To assess the association between CIMT and major adverse cardiovascular events (MACE) in this population.
Main Methods:
- Prospective study of 345 STEMI patients (mean age 59 years) undergoing emergent revascularization.
- Common CIMT measured via high-resolution ultrasonography; patients followed for a median of 583 days.
- Primary endpoint: MACE (cardiovascular death, heart failure, recurrent MI, revascularization, stroke).
Main Results:
- Mean CIMT was 0.77 ± 0.14 mm; 20.6% had carotid plaque, 11.0% experienced MACE.
- Higher CIMT tertiles (≥ 0.83 mm) were associated with increased MACE rates (19.0% vs. 4.3% for lowest tertile).
- CIMT and carotid plaque independently predicted overall MACE; CIMT tertile showed superior predictive value over other clinical factors (ROC AUC 0.69).
Conclusions:
- CIMT is a valuable prognostic marker for predicting future cardiovascular events in Asian STEMI patients.
- CIMT measurement can enhance risk stratification beyond traditional factors in this demographic.
Background:
Carotid intima-media thickness (CIMT) is associated with an increased risk of cardiovascular disease. We studied whether CIMT predicts the prognosis of Asian patients with acute ST-elevation myocardial infarction (STEMI).
Methods:
A total of 345 patients with STEMI (men, 82.9%; age, 59 ± 13 years) treated with emergent revascularization were prospectively investigated. In all patients, common CIMT was measured with high-resolution ultrasonography. The patients were followed for a median period of 583 days, and the primary end point was major adverse cardiovascular events (MACE) defined as a composite of cardiovascular death, heart failure, nonfatal recurrent MI, revascularization, and stroke.
Results:
Mean CIMT of the patients with STEMI was 0.77 ± 0.14 mm. Of the total patients, 20.6% had carotid plaque and 11.0% experienced MACE. Killip class, left ventricular (LV) function, and carotid plaque were associated with 30-day MACE, whereas CIMT and carotid plaque were related to overall MACE. After adjusting for age, the event rate was 19.0% in the third-tertile CIMT (≥ 0.83 mm) group, 12.1% in the second-tertile (0.70-0.82 mm) group, and 4.3% in the first-tertile (≤ 0.69 mm) group (P = 0.01). Carotid plaque was independently associated with a higher incidence of MACE (adjusted odds ratio [OR], 3.7; 95% confidence interval [CI], 1.327-10.234; P = 0.012). Area under the receiver operating characteristic (ROC) curve for CIMT tertile (0.69 ± 0.05) was significantly larger compared with those for door-to-balloon time (0.55 ± 0.05), LV ejection fraction (LVEF) (0.49 ± 0.05), and Killip class (0.48 ± 0.05) (P < 0.001).
Conclusions:
CIMT was a useful prognosticator to predict future cardiovascular events (CVEs) in Asian patients with STEMI.
More Related Videos
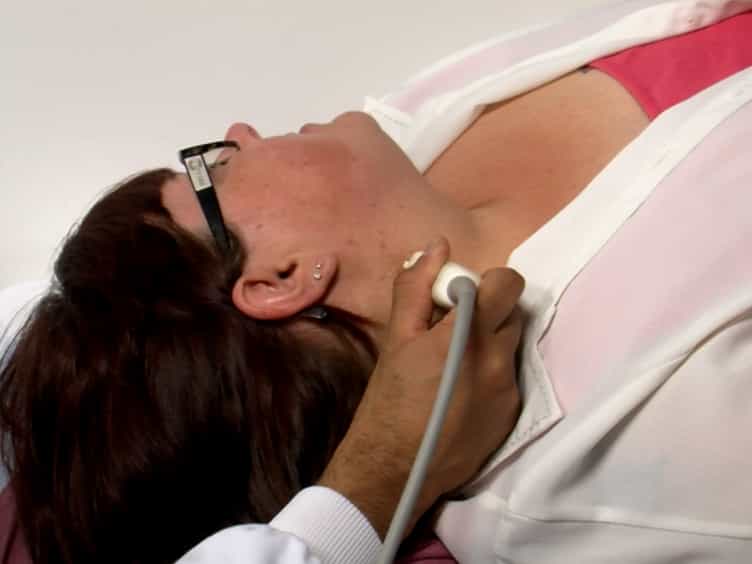 09:33
A Methodological Approach to Non-invasive Assessments of Vascular Function and Morphology
Published on: February 7, 2015
 09:36
A Magnetic Resonance Imaging-based Computational Protocol for Analysis of Plaque Morphology and Hemodynamics in Patients with Carotid Artery Stenosis
Published on: August 12, 2025
Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:26
Atherosclerosis III: Management