Related Experiment Video
Updated: Apr 20, 2026
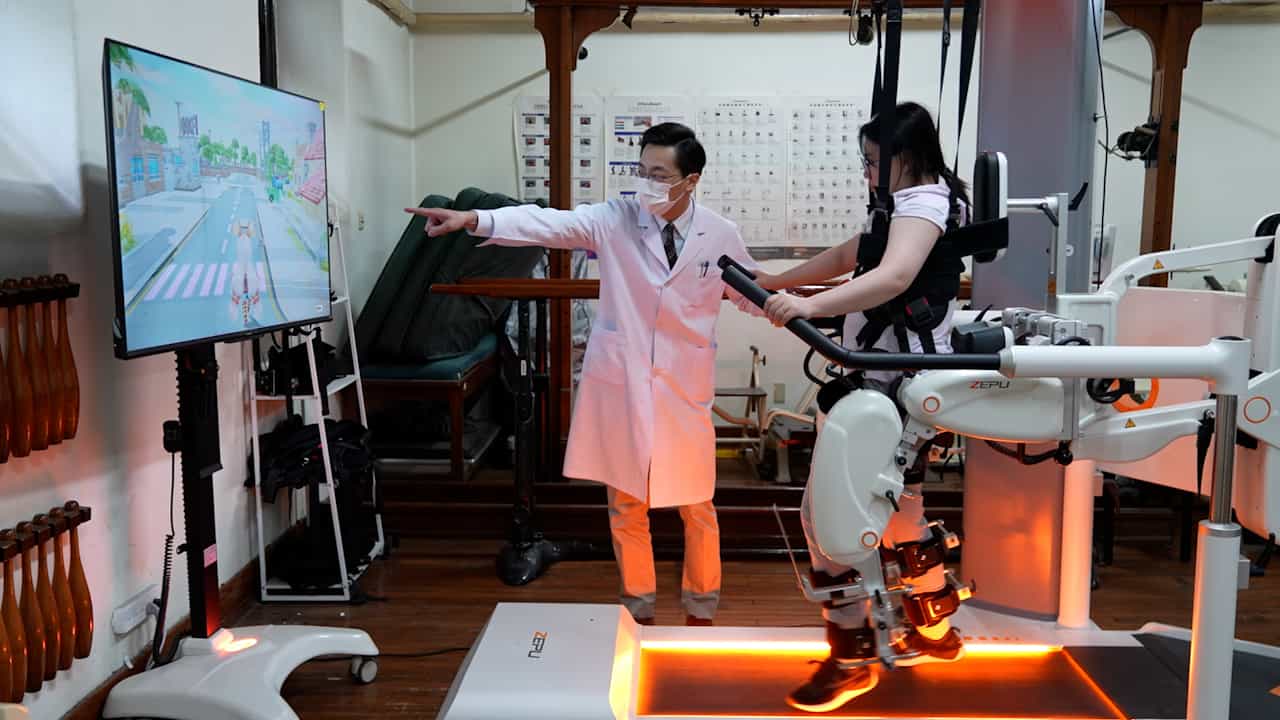

A Rehabilitation Program of Exoskeleton-assisted Body Weight-Supported Treadmill Training with Non-immersive Virtual Reality for Stroke Patients
Published on: May 16, 2025
Effectiveness, usability, and cost-benefit of a virtual reality-based telerehabilitation program for balance recovery
Roberto Lloréns1, Enrique Noé2, Carolina Colomer2
1Instituto Interuniversitario de Investigación en Bioingeniería y Tecnología Orientada al Ser Humano, Universitat Politècnica de València, Valencia, Spain; Servicio de Neurorrehabilitación y Daño Cerebral de los Hospitales NISA, Fundación Hospitales NISA, Valencia, Spain.

Objectives:
First, to evaluate the clinical effectiveness of a virtual reality (VR)-based telerehabilitation program in the balance recovery of individuals with hemiparesis after stroke in comparison with an in-clinic program; second, to compare the subjective experiences; and third, to contrast the costs of both programs.
Design:
Single-blind, randomized, controlled trial.
Setting:
Neurorehabilitation unit.
Participants:
Chronic outpatients with stroke (N=30) with residual hemiparesis.
Interventions:
Twenty 45-minute training sessions with the telerehabilitation system, conducted 3 times a week, in the clinic or in the home.
Main Outcome Measures:
First, Berg Balance Scale for balance assessment. The Performance-Oriented Mobility Assessment balance and gait subscales, and the Brunel Balance Assessment were secondary outcome measures. Clinical assessments were conducted at baseline, 8 weeks (posttreatment), and 12 weeks (follow-up). Second, the System Usability Scale and the Intrinsic Motivation Inventory for subjective experiences. Third, cost (in dollars).
Results:
Significant improvement in both groups (in-clinic group [control] and a home-based telerehabilitation group) from the initial to the final assessment in the Berg Balance Scale (ηp(2)=.68; P=.001), in the balance (ηp(2)=.24; P=.006) and gait (ηp(2)=.57, P=.001) subscales of the Tinetti Performance-Oriented Mobility Assessment, and in the Brunel Balance Assessment (control: χ(2)=15.0; P=.002; experimental: χ(2)=21.9; P=.001). No significant differences were found between the groups in any balance scale or in the feedback questionnaires. With regard to subjective experiences, both groups considered the VR system similarly usable and motivating. The in-clinic intervention resulted in more expenses than did the telerehabilitation intervention ($654.72 per person).
Conclusions:
First, VR-based telerehabilitation interventions can promote the reacquisition of locomotor skills associated with balance in the same way as do in-clinic interventions, both complemented with a conventional therapy program; second, the usability of and motivation to use the 2 interventions can be similar; and third, telerehabilitation interventions can involve savings that vary depending on each scenario.

