Related Experiment Video
Updated: Apr 20, 2026

Evaluating Postural Control and Lower-extremity Muscle Activation in Individuals with Chronic Ankle Instability
Published on: September 18, 2020
Postural control in response to altered sensory conditions in persons with dysvascular and traumatic transtibial
Prasath Jayakaran1, Gillian M Johnson1, S John Sullivan1
1Centre for Health, Activity, and Rehabilitation Research, University of Otago, Dunedin, New Zealand.

Objective:
To compare the postural control of persons with a dysvascular transtibial amputation and traumatic transtibial amputation with able-bodied adults with and without a dysvascular condition in altered sensory testing conditions.
Design:
Cross-sectional study.
Setting:
University balance clinic.
Participants:
The study participants (N=35) included: participants with a dysvascular transtibial amputation (n=9), participants with a traumatic transtibial amputation (n=9), age-matched able-bodied adults without a dysvascular condition (n=9), and able-bodied adults with a dysvascular condition (n=8).
Interventions:
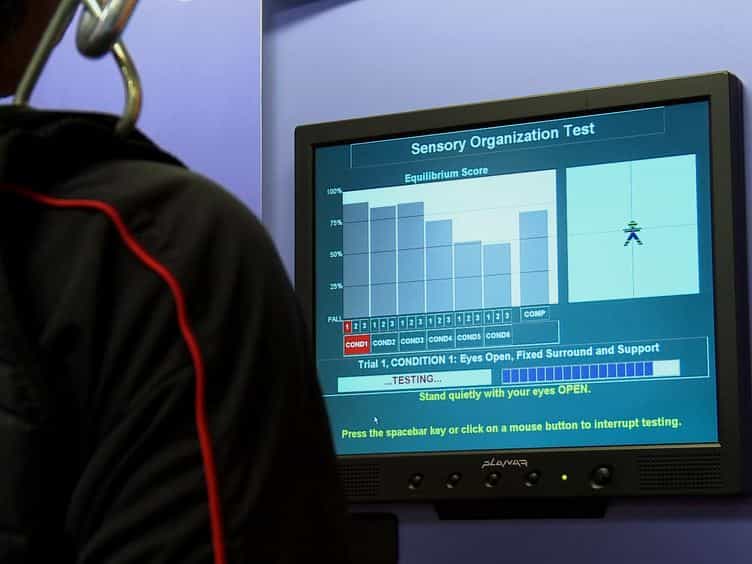
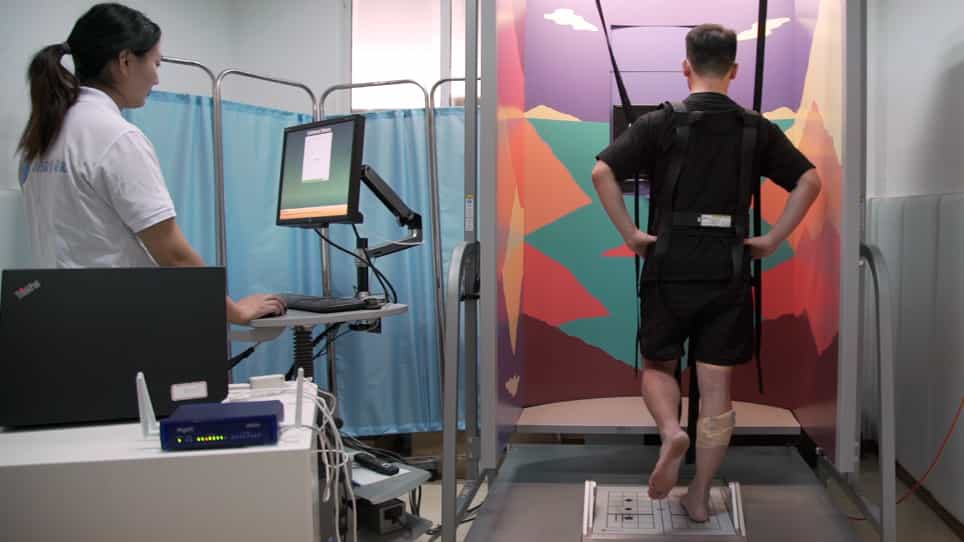
Six Sensory Organization Test (SOT) conditions, which included standing with eyes open (condition 1) and closed (condition 2) on a static force platform with visual surround; standing with eyes open on a static force platform with movable visual surround (condition 3); standing with eyes open (condition 4) and closed (condition 5) on a movable force platform with static visual surround; and standing with eyes open on a movable force platform with movable visual surround (condition 6).
Main Outcome Measures:
Bilateral anteroposterior (AP) and mediolateral (ML) center of pressure variables, namely root mean square distance (RMSD) and mean velocity (mVel), for each of the 6 SOT conditions.
Results:
The dysvascular transtibial amputation group demonstrated a higher AP RMSD (P≤.04) on the sound side than did the able-bodied adults without a dysvascular condition and the able-bodied adults with a dysvascular condition in SOT conditions 1 and 2, respectively. Both the dysvascular transtibial amputation group and the traumatic transtibial amputation group demonstrated a higher AP RMSD (P≤.002) than the able-bodied adults without a dysvascular condition in SOT conditions 3 and 4. The dysvascular transtibial amputation group showed higher AP mVel (P≤.002) on the sound side for SOT conditions 2 and 3, whereas both amputation groups showed higher AP mVel for SOT conditions 1 and 4 than the able-bodied adults with and without a dysvascular condition.
Conclusions:
Postural control of the dysvascular transtibial amputation group was not different than the traumatic transtibial amputation group in challenging sensory conditions. However, when compared with the groups of able-bodied adults with and without a dysvascular condition, postural strategies distinct with amputation etiology were observed.