Related Experiment Video
Updated: Apr 20, 2026


C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
Occipitocervical fusion: fix to C2 or C3?
Junwei Pan1, Dageng Huang1, Dingjun Hao1
1Department of Spine Surgery, Honghui Hospital, Xi'an Jiaotong University College of Medicine, No. 76 Nanguo Road, 710054 Xi'an, Shaanxi, China.

Objective:
The objective of this study was to explore the differences in clinical outcome between short-segment fixation (SSF; occiput-C2) and multi-segment fixation (MSF; occiput-C2, 3).
Methods:
From January 2008 to January 2012, patients who underwent surgery for instability at the occipitocervical junction were included in the study. Two different groups of surgeons using two different management options completed the surgeries. One group performed SSF, whereas the other group performed MSF. A total of 53 patients met the criteria (33 SSF, 20 MSF). Mean follow-up was 33.9 months (range, 12-62 months). Fusion was demonstrated by plain radiographs and computed tomography imaging. Neurological status, pillow neck pain, operative time, blood loss during operation, and perioperative complications were compared between the SSF and MSF groups.
Results:
The fusion rate was 97% in the SSF group and 100% in MSF the group. There was no statistically significant difference in the fusion rate between the two groups (P>0.05). One patient (3%) in the SSF group and two patients (10%) in the MSF group experienced perioperative complications. Of the 25 patients who had neurological symptoms, 22 (88%) showed improvement after the operation in the SSF group and 14 (87.5%) of 16 showed improvement in MSF group. In addition, patients who suffered from pillow neck pain achieved varying degrees of improvement after the operation.
Conclusion:
SSF may be the better choice for treating occipitocervical instability when no subaxial instability is present. Overall, modern instrumentation can provide the stability needed for successful clinical fusion.

Related Concept Videos
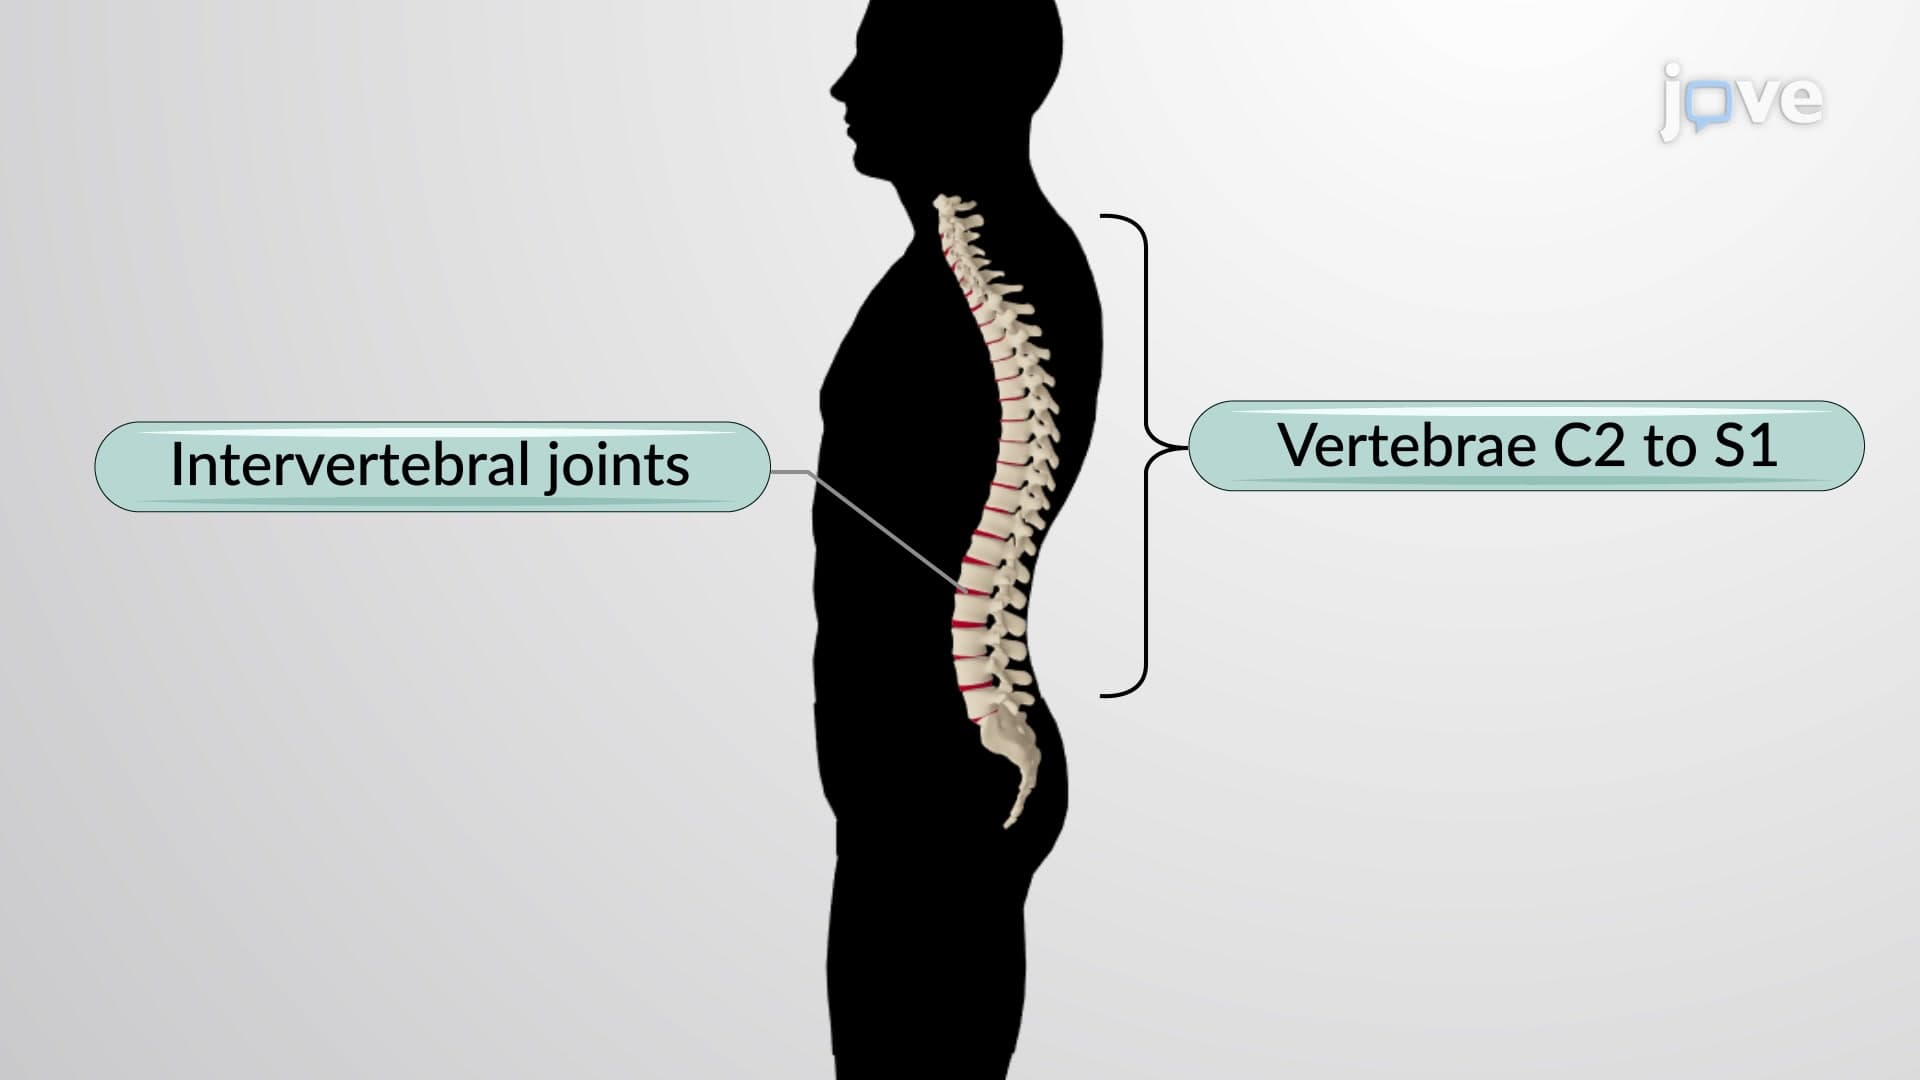 01:28
Articulations of the Vertebral Column
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:19
Muscles that Move the Head
The bilateral sternocleidomastoid, or SCM, and the suprahyoid and infrahyoid muscles are significant head flexors. The SCM muscles originate at the sternum and clavicle and attach to the mastoid process of the temporal bone. The SCM contracts bilaterally to bend the head forward, whereas...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
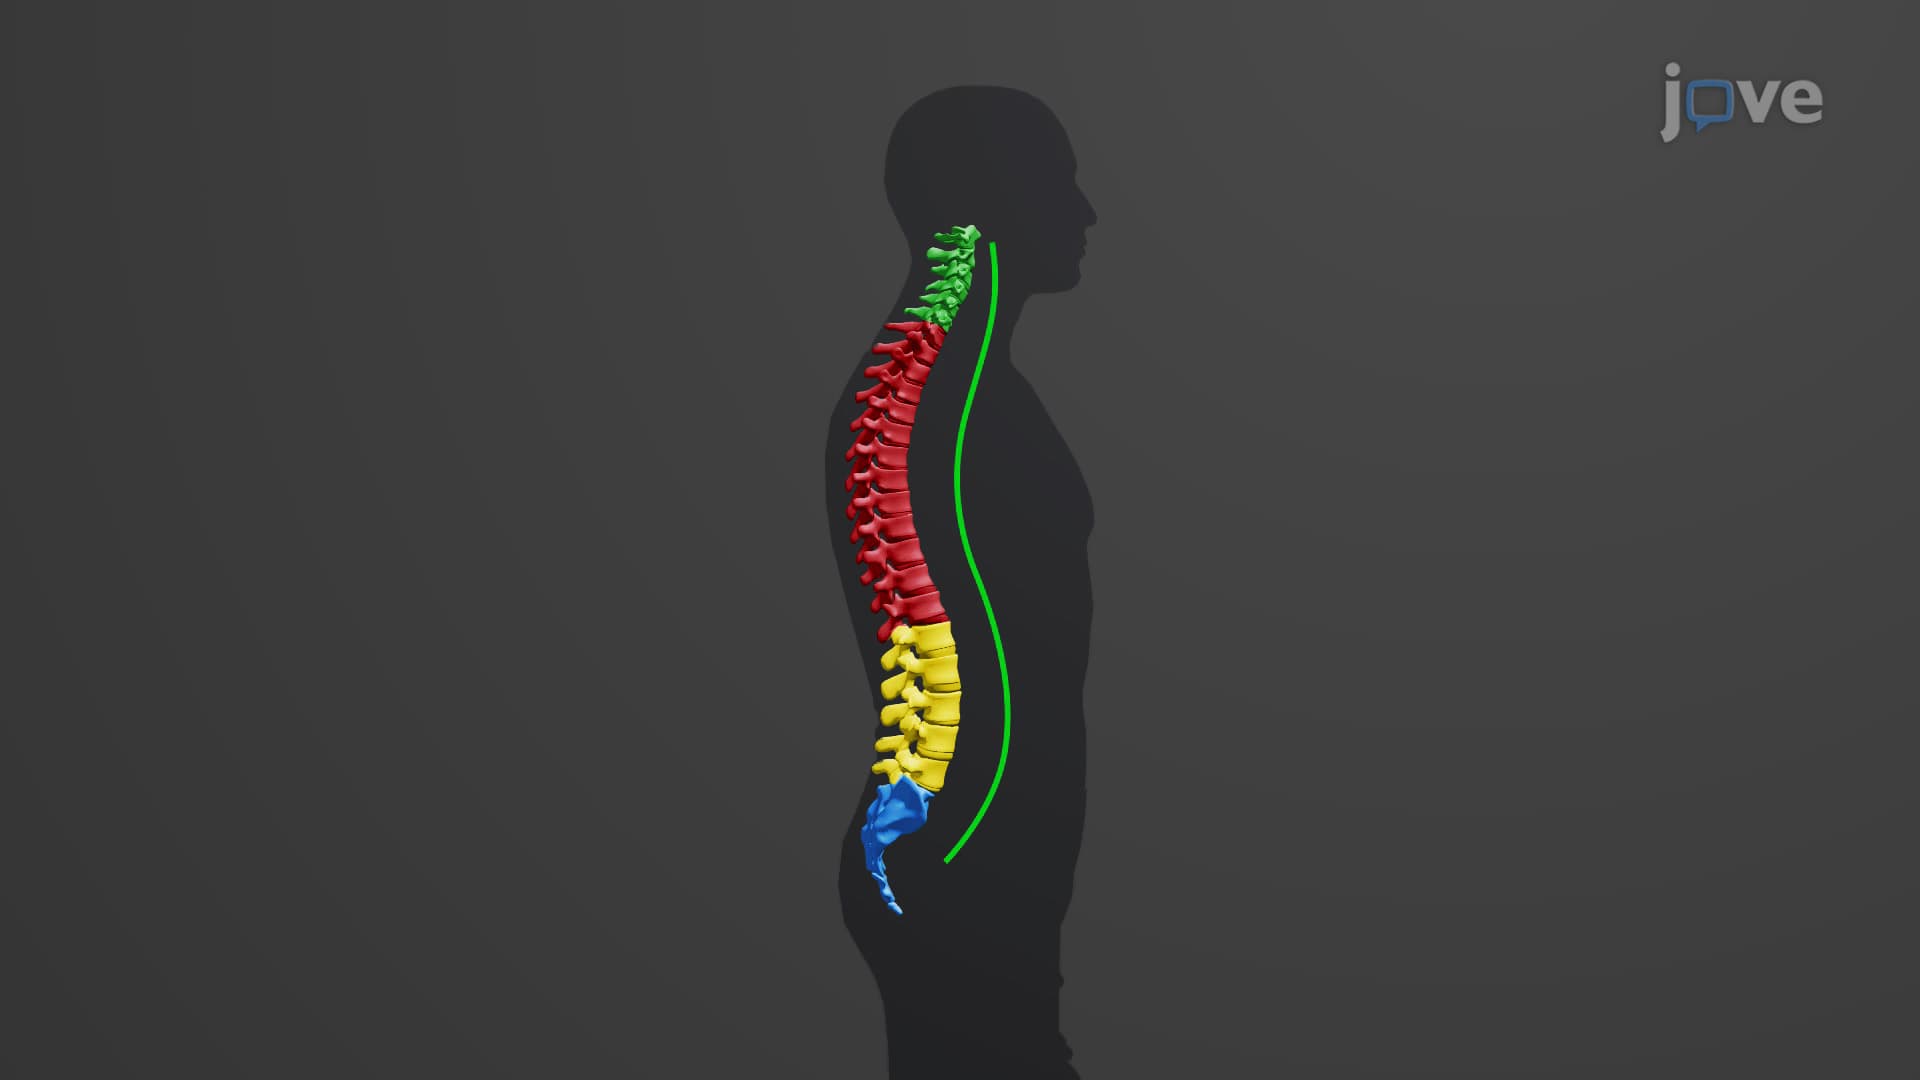 01:16
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:17
Structural Joints: Cartilaginous Joints
There are two types of cartilaginous joints:
Synchondrosis
A synchondrosis ("joined by cartilage") is a cartilaginous joint where bones are connected by hyaline cartilage. Synchondrosis may be temporary...