Related Experiment Video
Updated: Apr 20, 2026
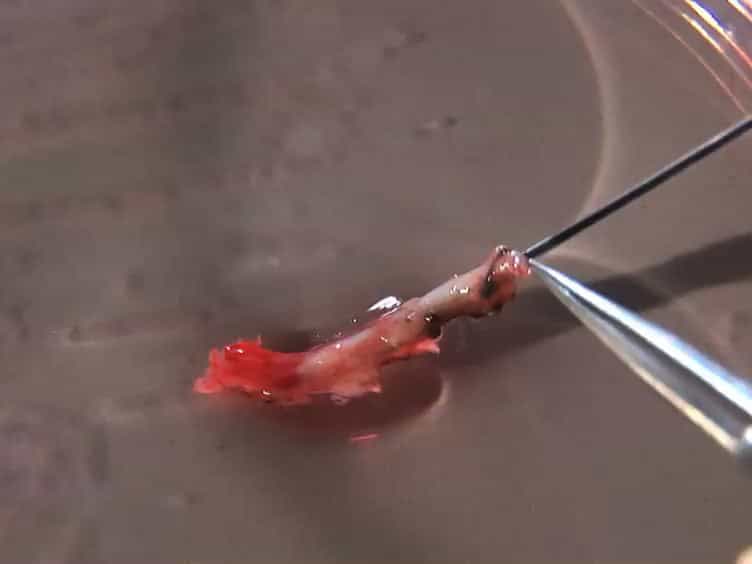

Human Internal Mammary Artery IMA Transplantation and Stenting: A Human Model to Study the Development of In-Stent Restenosis
Published on: May 9, 2012
Bilateral internal mammary artery grafting in diabetics: outcomes, concerns and controversies
1Department of Cardiac Surgery, Harefield Hospital, London, United Kingdom.

Insights
Bilateral internal mammary artery (BIMA) grafting offers superior outcomes for diabetic patients undergoing coronary artery bypass grafting (CABG). Despite concerns about sternal wound infection, BIMA utilization should be considered for this high-risk population.
Area of Science:
- Cardiovascular Surgery
- Diabetology
Background:
- Coronary artery disease (CAD) poses significant mortality risks for diabetic patients, who comprise a substantial portion of revascularization candidates.
- Diabetic patients undergoing revascularization face higher mortality and repeat procedure rates due to factors like co-morbidities and diffuse disease.
- Coronary artery bypass grafting (CABG) is preferred for multi-vessel disease in diabetics, with arterial conduits showing better outcomes than venous ones.
Purpose of the Study:
- To review the outcomes, concerns, and controversies surrounding bilateral internal mammary artery (BIMA) grafting in diabetic patients.
- To evaluate the presumed benefits of BIMA grafting in diabetics, mirroring its advantages in non-diabetic populations.
- To address the underutilization of BIMA in diabetics due to perceived increased risks.
Main Methods:
- Review of existing literature on BIMA grafting in diabetic patients undergoing CABG.
- Analysis of outcomes data comparing BIMA to other conduits in diabetic populations.
- Examination of concerns, including sternal wound infection, and controversies regarding BIMA use.
Main Results:
- Bilateral internal mammary arteries (BIMA) are recognized as superior arterial conduits for CABG, linked to improved cardiac event-free survival.
- BIMA grafting is presumed to offer similar benefits to diabetic patients as observed in non-diabetic individuals.
- Underutilization of BIMA in diabetics persists, often attributed to concerns about sternal wound infection risk.
Conclusions:
- Bilateral internal mammary artery (BIMA) grafting is a potentially beneficial revascularization strategy for diabetic patients with multi-vessel coronary artery disease.
- Addressing concerns regarding sternal wound infection is crucial for increasing the adoption of BIMA grafting in this high-risk group.
- Further research and evidence are needed to fully elucidate the role and optimize the use of BIMA in diabetic patients undergoing CABG.
Abstract:
Coronary artery disease (CAD) is a leading cause of mortality and morbidity in diabetics. Diabetics make up to 20%-35% of all patients undergoing coronary revascularization. Patients with diabetes represent a particularly difficult subset for revascularization due to increased short- and long-term mortality as well as a higher risk of repeat revascularization procedures. Potential factors contributing to the increased risk include co-morbid illnesses, small, diffusely diseased target vessels, progression of native CAD, hyperglycaemic endothelial dysfunction, and systemic inflammation. For diabetic patients with multi-vessel disease, revascularization by coronary artery bypass grafting (CABG) is regarded as the preferred option. There is increasing recognition that the use of arterial conduits for CABG is associated with improved outcomes compared to use of venous conduits. Amongst arterial conduits bilateral internal mammary arteries (BIMA) have emerged as the superior conduits due to better cardiac event-free survival. Consistent with its benefits in non-diabetic patients, BIMA grafting is presumed to offer similar benefits in diabetic patients. However, BIMA grafting remains underutilised in diabetics due to perceived increased risk of sternal wound infection. This review article provides an overview of BIMA grafting in diabetic patients focussing on outcomes, concerns, and controversies associated with BIMA usage in this high-risk group of patients.


