Related Experiment Video
Updated: Apr 19, 2026


Bile Duct Ligation in Mice: Induction of Inflammatory Liver Injury and Fibrosis by Obstructive Cholestasis
Published on: February 10, 2015
Diagnostic accuracy of hyperbilirubinaemia in anticipating appendicitis and its severity
Sven Muller1, Claudius Falch1, Steffen Axt1
1Working Group for Surgical Technology and Training, Clinic for Visceral, General and Transplant Surgery, Tübingen University Hospital, Tübingen, Germany.

Background:
Hyperbilirubinaemia is reported to be a positive predictor in diagnosing appendicitis and especially appendiceal perforation. We, therefore, analysed the diagnostic accuracy of serum bilirubin in anticipating appendicitis and its severity.
Methods:
All consecutive patients undergoing appendectomy for suspected appendicitis from May 2009 to August 2011 were analysed. Patients were classified based on final histopathological findings into the groups: no appendiceal inflammation, non-perforated appendicitis and perforated appendicitis. Primary outcome was the diagnostic accuracy of serum bilirubin levels in discriminating between no appendiceal inflammation and any appendicitis (perforated and non-perforated appendicitis) and non-perforated and perforated appendicitis.
Results:
Of 493 analysed patients, 125 (25%) had no appendiceal inflammation, 312 (64%) had non-perforated appendicitis and 56 (11%) had perforated appendicitis. The proportion of patients with bilirubin elevation (>1.1 mg/dL) was different between those with no appendiceal inflammation (14%) and any appendicitis (36%) (p<0.0001), and between non-perforated appendicitis and perforated appendicitis 48% (p=0.04). However, the positive and negative likelihood ratios (LRs) for an elevated bilirubin were poor at discriminating the groups: no appendiceal inflammation versus any appendicitis (LR+ 2.62 (95% CI 1.65 to 4.16) and LR- 0.75 (95% CI 0.67 to 0.83)) and non-perforated appendicitis versus perforated appendicitis (LR+ estimate 1.74 (95% CI 1.28 to 2.38) and LR- 0.72 (95% CI 0.55 to 0.93)).
Conclusions:
Hyperbilirubinaemia is present in acute appendicitis but has a low diagnostic accuracy in discriminating between any appendicitis versus no appendiceal inflammation and perforated versus non-perforated appendicitis and is, therefore, of limited value in clinical routine.
Trial Registration Number:
NCT01698099.
More Related Videos
 07:10
Measurement of the Hepatic Venous Pressure Gradient and Transjugular Liver Biopsy
Published on: June 18, 2020
 05:22
Intraoperative Strategy under Complex Vascular Adhesion for Laparoscopic Radical Resection of Bismuth-Corlette Type IIIb Perihilar Cholangiocarcinoma
Published on: February 13, 2026
Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:19
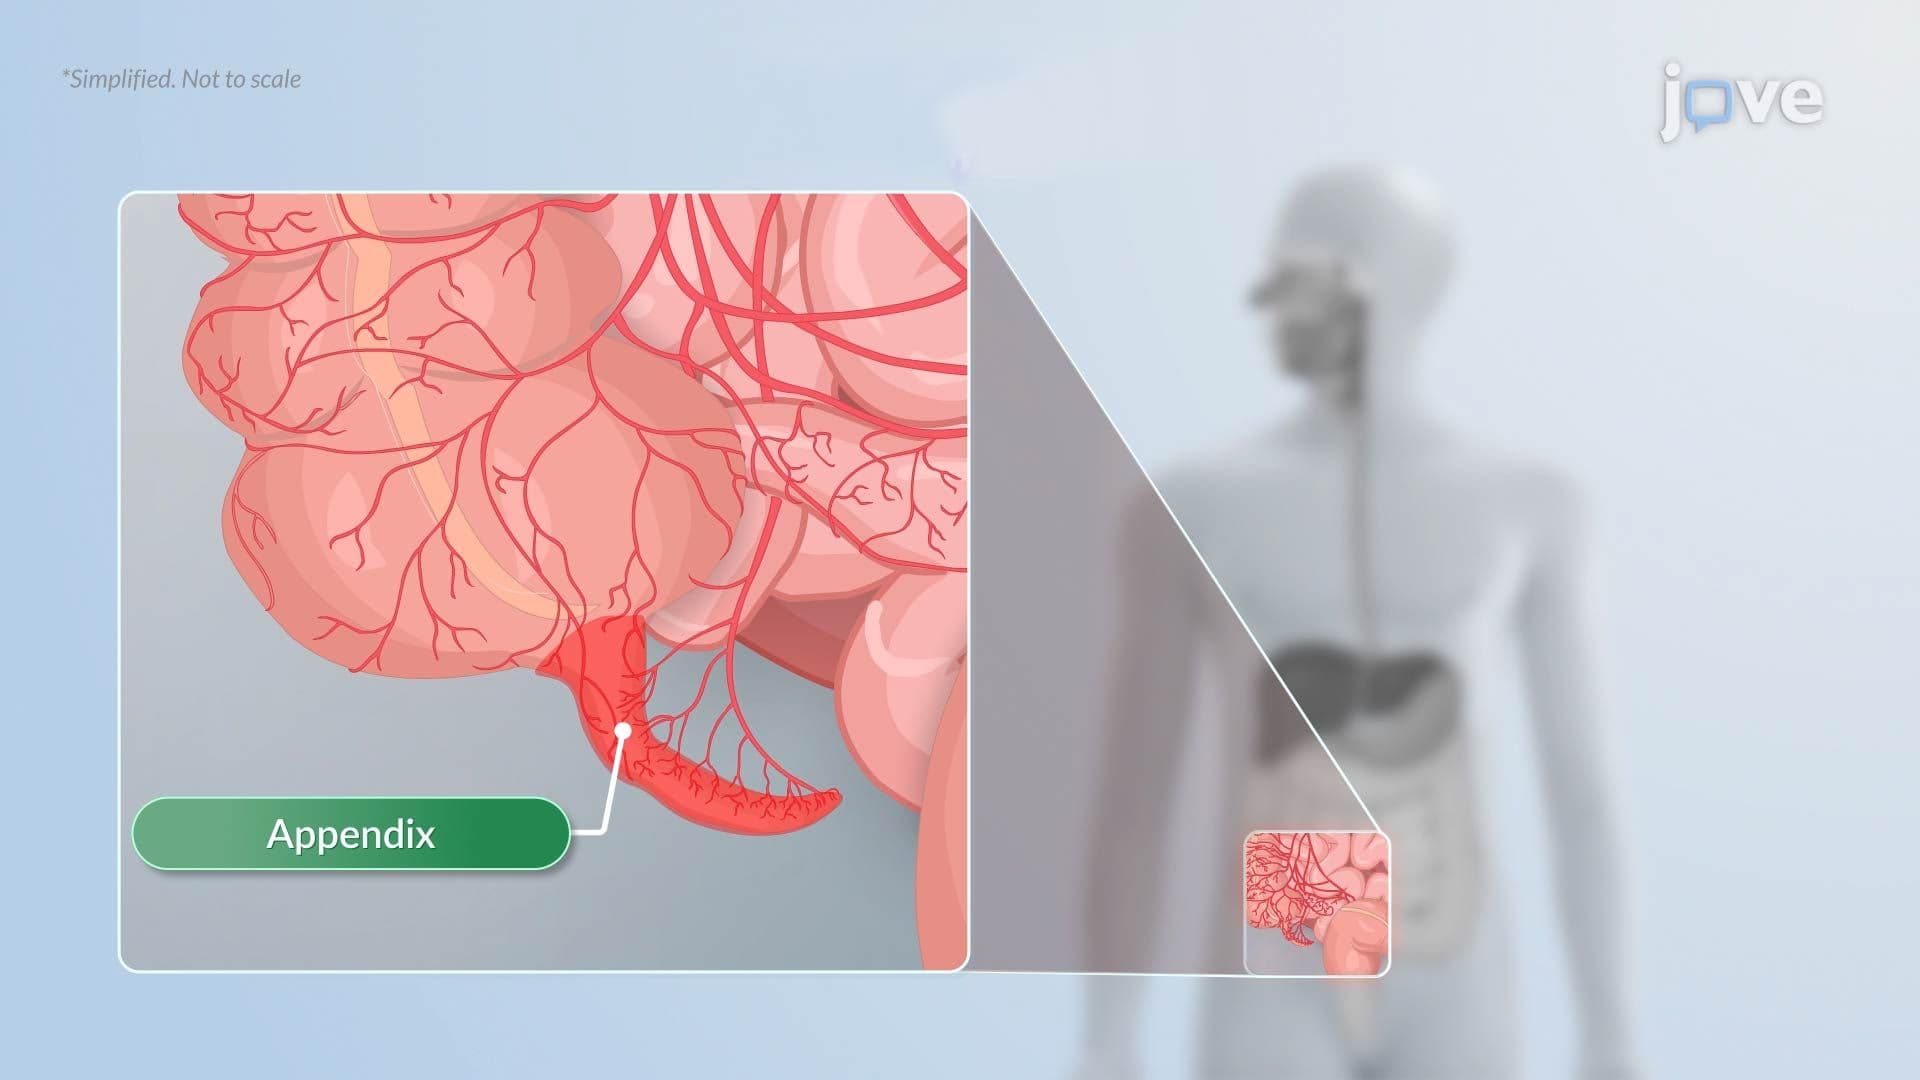
Appendicitis
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:25
Ultrasound II: Endoscopic Ultrasound and FibroScan
Endoscopic Ultrasound (EUS):
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.