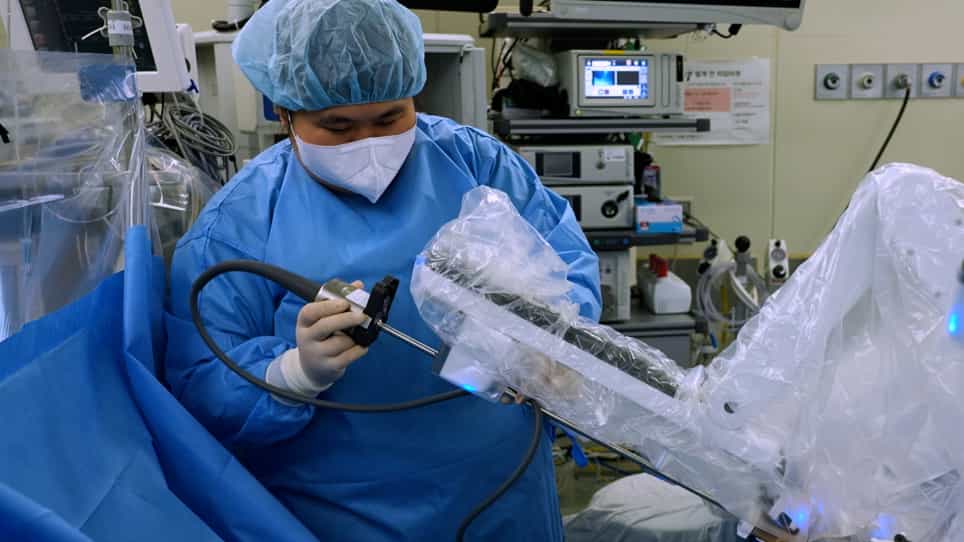
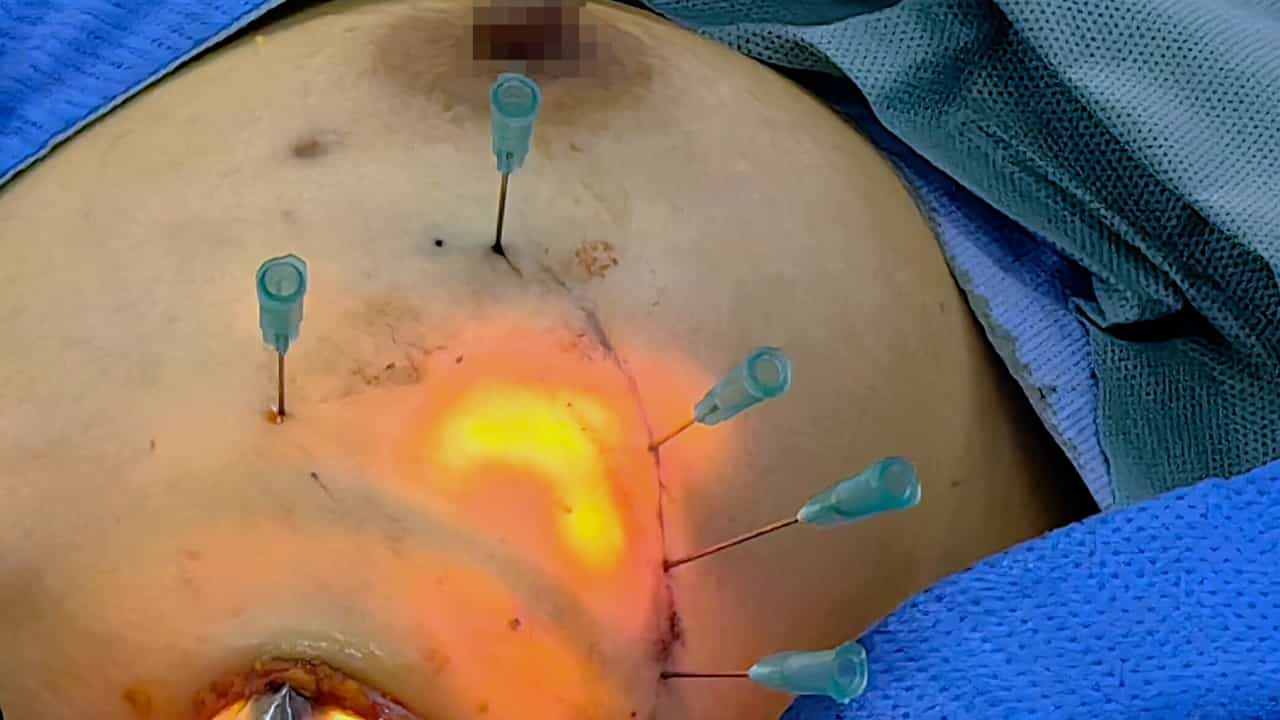
A comparison of robotic surgery in children weighing above and below 15.0 kg: size does not affect surgery success
Related Experiment Video
Updated: Apr 19, 2026
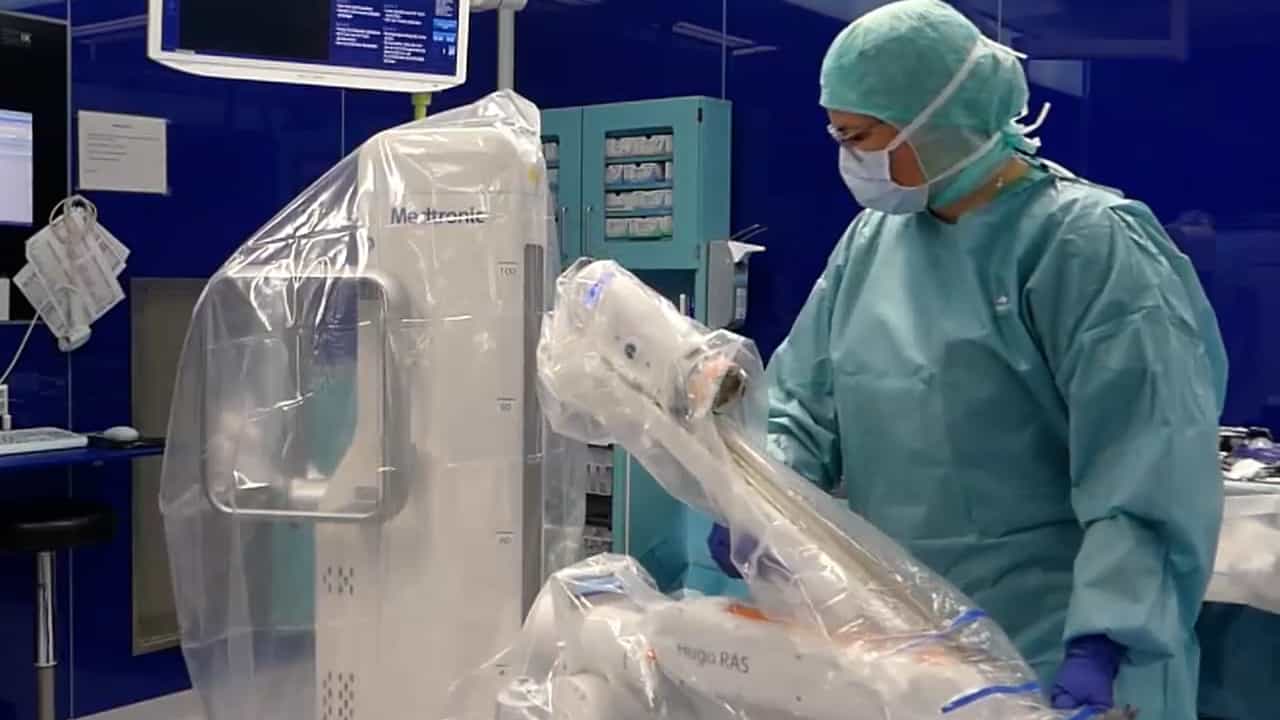
Robotics in Surgery: A Modular Robotic Platform Driven Gastric Wedge Resection
Published on: February 7, 2025
Quentin Ballouhey1, Thierry Villemagne, Jérôme Cros
1Service de chirurgie viscérale pédiatrique, Hôpital des Enfants, 8 Avenue Dominique Larrey, 87042, Limoges Cedex, France, q.ballouhey@gmail.com.

Insights
Robotic-assisted surgery is feasible and safe in small children, even neonates. While setup time is longer for younger patients, operative time and hospital stay are comparable to older children.
Area of Science:
- Minimally Invasive Surgery
- Pediatric Urology
- Surgical Robotics
Background:
- Robotic-assisted surgery shows promise in pediatric urology.
- Limited data exists for its use in infants and neonates.
- This study compares outcomes in younger vs. older pediatric surgical patients.
Purpose of the Study:
- To evaluate the feasibility and safety of robotic-assisted surgery in pediatric patients.
- To compare outcomes between children weighing less than 15.0 kg and those weighing more.
Main Methods:
- A multicentric study analyzed 178 robotic procedures (2008-2012).
- Patients were divided into two groups based on weight: <15.0 kg (Group A) and >15.0 kg (Group B).
- Perioperative and intraoperative data were collected and analyzed.
Main Results:
- Group A (62 patients, 11.1 kg) had a higher conversion rate (5% vs. 2%) mainly in neonatal thoracic procedures.
- Setup time was longer for Group A (p < 0.05) in pyeloplasty, partial nephrectomy, and fundoplication.
- No significant differences were found in operative time, hospital stay, or postoperative outcomes.
Conclusions:
- Robotic-assisted surgery is feasible in small children, including neonates.
- Specific adjustments in patient positioning and trocar placement may be needed.
- Outcomes are comparable to older children, despite the absence of dedicated instruments for pediatric robotic surgery.
Background:
Initial results in pediatric surgery are encouraging, particularly in the field of pediatric urology. However, there is limited experience with its application in infants and neonates. The aim of this study was to compare the feasibility and safety of robotic-assisted surgery in two populations of children, one weighing less and one weighing more than 15.0 kg.
Methods:
A multicentric study was performed comparing the success of robotic-assisted surgery in patients who weighed less than 15.0 kg (group A) to patients heavier than 15.0 kg (group B), with a total of 178 procedures performed between January 2008 and December 2012. Data concerning the perioperative and intraoperative periods were prospectively collected and retrospectively analyzed.
Results:
The success of robotic-assisted surgery was compared between group A (62 patients, 11.1 kg) and group B (116 patients, 30.2 kg), with a mean follow-up of 37 months (16-75 months). The conversion rate was superior for group A (5 vs. 2%) and involved three neonatal thoracic procedures. Focusing on three common procedures for both groups (pyeloplasty, partial nephrectomy, and fundoplication), the amount of time for set up was longer for group A (p < 0.05). We found no statistical differences in the mean total operative time and length of hospital stay. The postoperative follow-up revealed similar results for both groups.
Conclusions:
Cautious adjustments in the patient positioning and trocar placement were necessary in a subset of this pediatric population. For these three particular procedures, with the exception of the longer set up time, the results between the two groups were comparable. These data support the feasibility of robotic-assisted surgery for small children, despite the lack of dedicated instruments.