Related Experiment Video
Updated: Apr 19, 2026

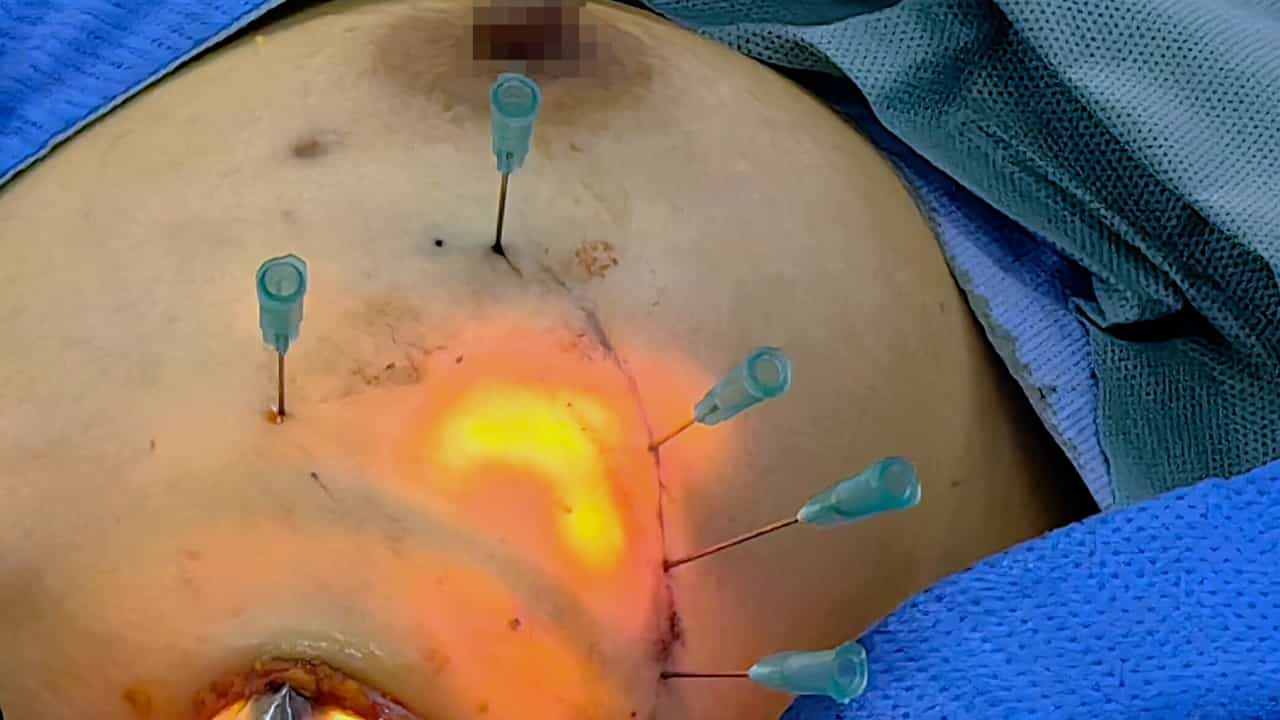
Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Reduced risk of axillary lymphatic spread in triple-negative breast cancer
Emil Villiam Holm-Rasmussen1, Maj-Britt Jensen, Eva Balslev
1Department of Breast Surgery, Copenhagen University Hospital, Section 4124, Blegdamsvej 9, 2100, Copenhagen, Denmark.

Abstract:
We examined the association between the hormone receptor (HR) and human epidermal growth factor receptor 2 (HER2) status of women with primary breast cancer and the risk of axillary lymph node (ALN) involvement at the time of diagnosis. Information on 20,009 women diagnosed with primary breast cancer between 2008 and 2012 was retrieved from the Danish Breast Cancer Cooperative Group database. The associations between clinical and pathological variables and ALN involvement at the time of diagnosis were evaluated in univariate and multivariate regression analyses, as well as the significance of tumor subtypes in ALN involvement. The risk of ALN metastases at the time of diagnosis was significantly reduced in HR-negative patients compared to HR-positive patients [adjusted odds ratio (OR) 0.69; 95 % CI 0.63-0.76; P = 0.0009]. A HER2-positive status was associated with an increased risk of ALN involvement at diagnosis compared to a HER2-negative status (OR 1.37; 95 % CI 1.24-1.50; P < 0.0001). An interaction between HER2 and HR was observed, with a HER2-positive status significantly associated with ALN involvement at the time of diagnosis only in HR-negative patients (P < 0.0001). The triple-negative breast cancer (TNBC) patients showed a significantly reduced risk of ALN involvement at the time of diagnosis compared to patients with HR-positive/HER2-negative tumors (OR 0.55; 95 % CI 0.49-0.62; P < 0.0001). The HR and HER2 statuses are significantly associated with ALN involvement at the time of diagnosis. Despite the poor prognosis, TNBC patients have a reduced risk of ALN involvement at the time of diagnosis compared to patients with other subtypes, when adjusting for other risk factors. This may indicate that TNBC tends to spread hematogenously rather than lymphogenously.