Related Experiment Video
Updated: Apr 19, 2026

Intraspinal Cell Transplantation for Targeting Cervical Ventral Horn in Amyotrophic Lateral Sclerosis and Traumatic Spinal Cord Injury
Published on: September 18, 2011
Complications Associated With High-dose Corticosteroid Administration in Children With Spinal Cord Injury
Jason M Cage1, Jeffrey B Knox, Robert L Wimberly
1*Tripler Army Medical Center, Orthopedic Surgery Service, Honolulu, HI †Department of Orthopedics, Texas Scottish Rite Hospital for Children and Children's Medical Center, Dallas, TX ‡Center for Policy & Public Administration, Principal Outcomes Consultant, Draper, UT.

Insights
High-dose steroids for pediatric spinal cord injuries did not increase infection rates, contrary to adult data. Hyperglycemia occurred in all patients, but infections were lower in the steroid group.
Area of Science:
- Pediatric Traumatology
- Neurology
- Pediatric Critical Care
Background:
- Complications of high-dose steroid use in adult spinal cord injury (SCI) are known.
- Limited data exists on early complications in pediatric SCI patients receiving this therapy.
Purpose of the Study:
- To determine the incidence of early complications associated with high-dose steroid administration in pediatric SCI patients.
- To compare complication rates between pediatric SCI patients who received high-dose steroids and those who did not.
Main Methods:
- Retrospective review of pediatric SCI patients (2003-2011) at a level 1 trauma center.
- Complications categorized into infectious, gastrointestinal (GI), hyperglycemia/endocrine, and wound healing.
- Statistical comparison using Student's t test and Fischer's exact test.
Main Results:
- Thirty-four pediatric SCI patients were analyzed; 23 received steroids, 11 did not.
- Hyperglycemia was present in all patients, irrespective of steroid treatment.
- The steroid group had significantly lower overall infection rates (26% vs. 64%) and respiratory tract infections (9% vs. 45%) compared to the control group.
Conclusions:
- High-dose steroids in pediatric SCI patients were not associated with increased infection rates.
- Hyperglycemia is a common finding in pediatric SCI, regardless of steroid use.
- Further multicenter prospective studies are necessary to fully elucidate risks in this population.
Background:
Complications with high-dose steroid administration for spinal cord injury are documented in adult patients. Our purpose was to determine the incidence of early complications of this therapy in pediatric patients with spinal cord injuries.
Methods:
An IRB-approved retrospective review was performed for patients treated for spinal cord injury at a level 1 pediatric trauma center between 2003 and 2011. Demographic data, injury characteristics, and surgical interventions were documented. Complications were divided into 4 categories: infectious, gastrointestinal (GI), hyperglycemia/endocrine, and wound healing problems. Complication rates were compared using a Student's t test and Fischer's exact test.
Results:
Thirty-four spinal cord injury patients were identified. Twenty-three patients (mean age 6.6 y) in the treatment group received high-dose steroid treatment and 11 patients (mean age 8.4 y) did not and comprised the control group. No statistical difference was detected between the 2 groups regarding age, mechanism of injury, rate of surgical intervention, level of injury, and injury severity. Hyperglycemia was the most common complication and was present in all patients in both the treatment and control groups. The overall infection rate was 64% in the control group compared with 26% in the treatment (P<0.05). The control group demonstrated a significantly increased rate of respiratory tract infections [45% control vs. 9% treatment (P<0.05)]. No surgical patients developed a wound infection. One treatment group patient experienced a GI bleed.
Conclusions:
This is the largest study evaluating the complications associated with high-dose steroid administration for spinal trauma in a pediatric population. Hyperglycemia was found in all spinal cord injury patients, regardless of steroid treatment. Paradoxically, infection rates were noted to be higher in the control group. GI and wound problems were not significantly different. Larger, multicenter prospective studies are needed to better understand the risks in pediatric SCI patients.

Related Concept Videos
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
 01:14
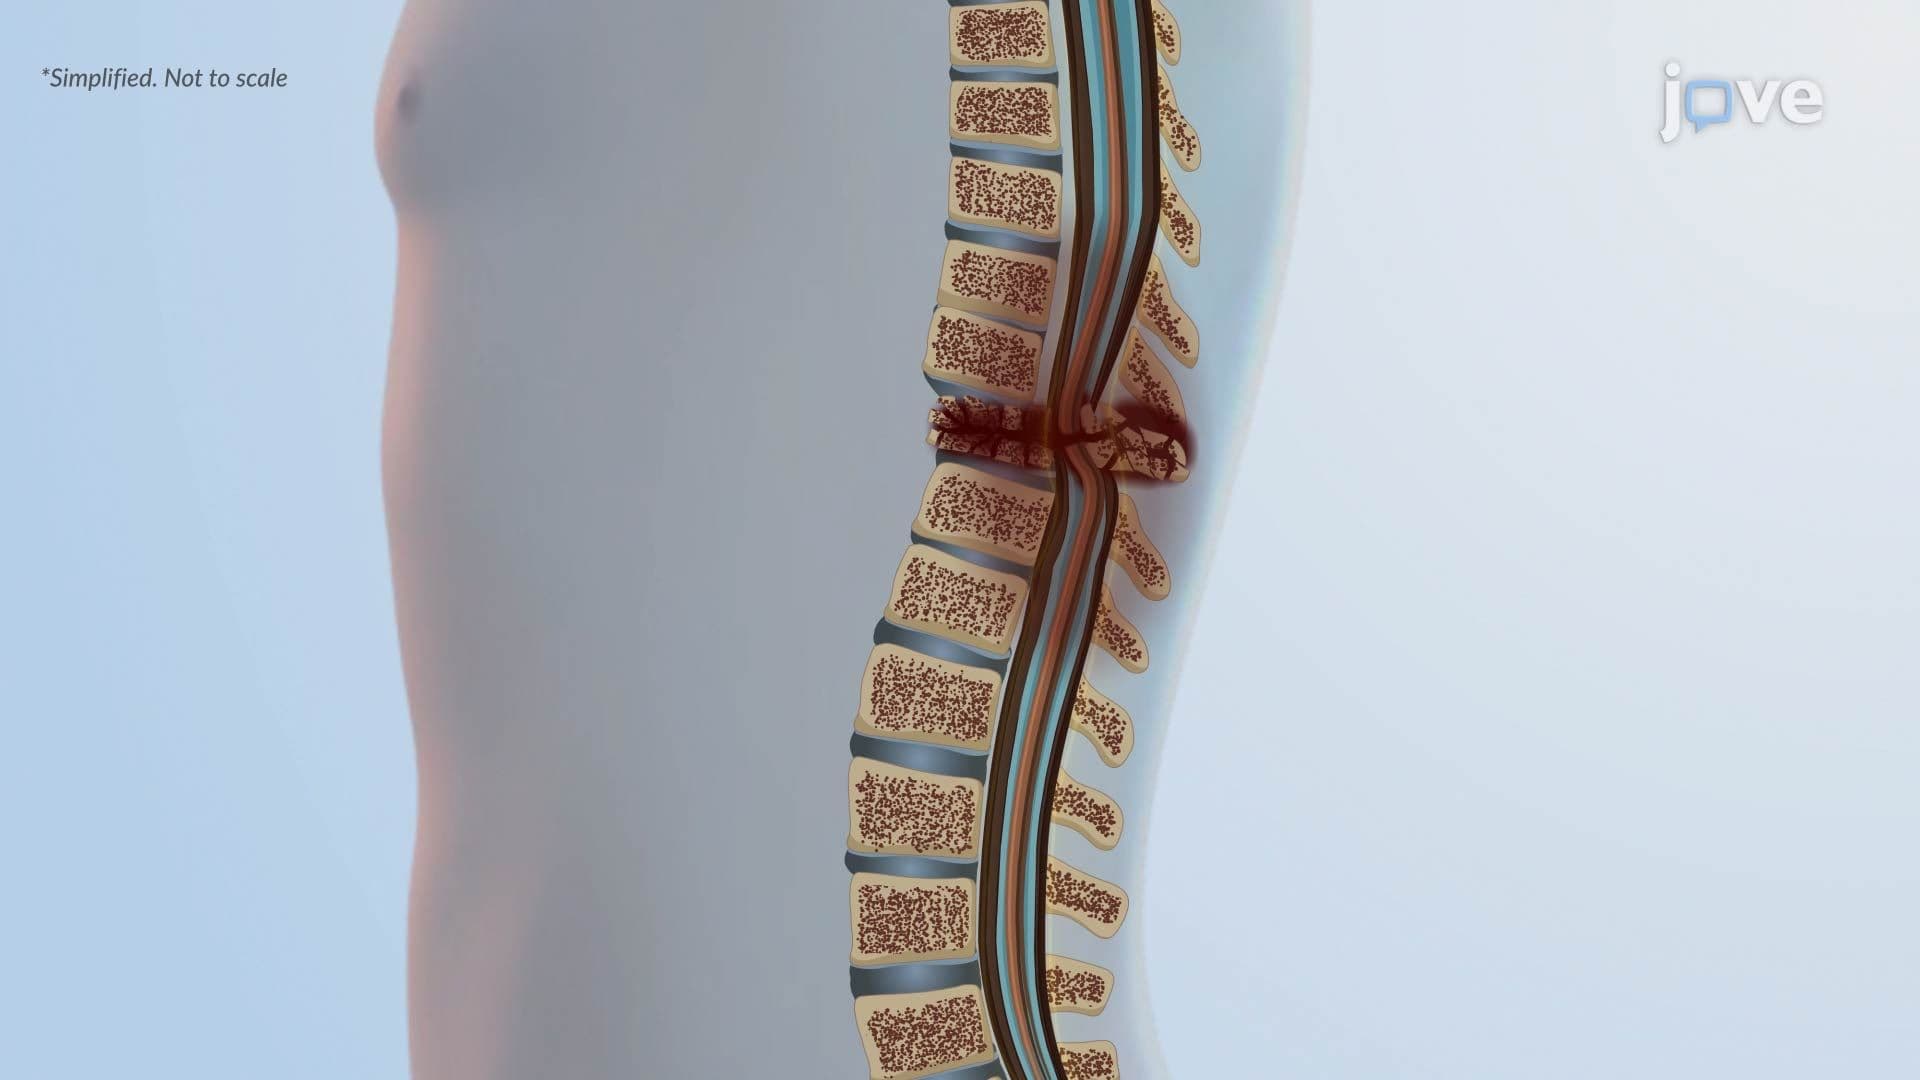
Spinal Cord Injury ll: Pathophysiology
 01:27
Adrenal Gland Disorders
Adrenal insufficiency, characterized by insufficient cortisol and aldosterone production, leads to conditions like Addison's disease. This disorder, affecting the adrenal cortex, exhibits symptoms such as skin bronzing, dehydration, low blood pressure, fatigue, and weight loss. Congenital adrenal hyperplasia, a genetic ailment causing...
 01:19
Cushing Syndrome II: Pathophysiology
 01:26
Cushing Syndrome I: Introduction
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...