Related Experiment Video
Updated: Apr 19, 2026
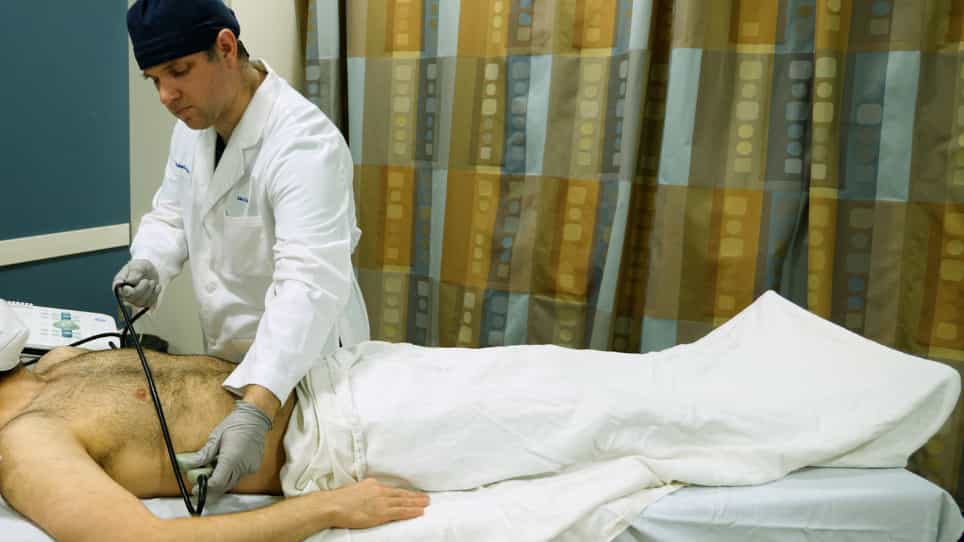
Focused Assessment with Sonography for Trauma FAST Exam: Image Acquisition
Published on: September 22, 2023
The peril of thoracoabdominal firearm trauma: 984 civilian injuries reviewed
Regan J Berg1, Kenji Inaba, Obi Okoye
1From the Division of Trauma Surgery and Surgical Critical Care, Los Angeles County Medical Center, University of Southern California, Los Angeles, California.

Background:
Thoracoabdominal firearm injuries present major diagnostic and therapeutic challenges because of the risk for potential injury in multiple anatomic cavities and the attendant dilemma of determining the need for and correct sequencing of cavitary intervention. Injury patterns, management strategies, and outcomes of thoracoabdominal firearm trauma remain undescribed across a large population.
Methods:
All patients with thoracoabdominal firearm injury admitted to a major Level I trauma center during a 16-year period were reviewed.
Results:
The 984 study patients experienced severe injury burden; 25% (243 of 984) presented in cardiac arrest, and 75% (741 of 984) had an Abbreviated Injury Scale (AIS) score of 3 or greater in both the chest and the abdomen. Operative management occurred in 86% (638 of 741). Of the patients arriving alive, 68% (507 of 741) underwent laparotomy alone, 4% (27 of 741) underwent thoracotomy alone, and 14% (104 of 741) underwent dual-cavitary intervention. Negative laparotomy occurred in 3%. Diaphragmatic injury (DI) occurred in 63%. Seventy-five percent had either DI or hollow viscus injury. Cardiac injury was present in 33 patients arriving alive. Despite the use of trauma bay ultrasound, 44% of the patients with cardiac injury underwent initial laparotomy. In half of this group, ultrasound did not detect pericardial blood. The need for thoracotomy, either alone or as part of dual-cavitary intervention, was the strongest independent risk factor for mortality in those arriving alive.
Conclusion:
Greater kinetic destructive potential drives the peril of thoracoabdominal firearm trauma, producing clinical challenges qualitatively and quantitatively different from nonfirearm injuries. Severe injury, on both sides of the diaphragm, generates high operative need with low rates of negative exploration. The need for emergent intervention and a high incidence of DI or hollow viscus injury limit opportunity for nonoperative management. Even with ultrasound, emergent preoperative diagnosis remains challenging, as the complex combination of intra-abdominal, thoracic, and diaphragmatic injuries can provoke misinterpretation of both radiologic and clinical data. Successful emergent management requires thorough assessment of all anatomic spaces, integrating ultrasonographic, radiologic, and clinical findings.
Level Of Evidence:
Epidemiologic study, level III.
More Related Videos
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
 04:20
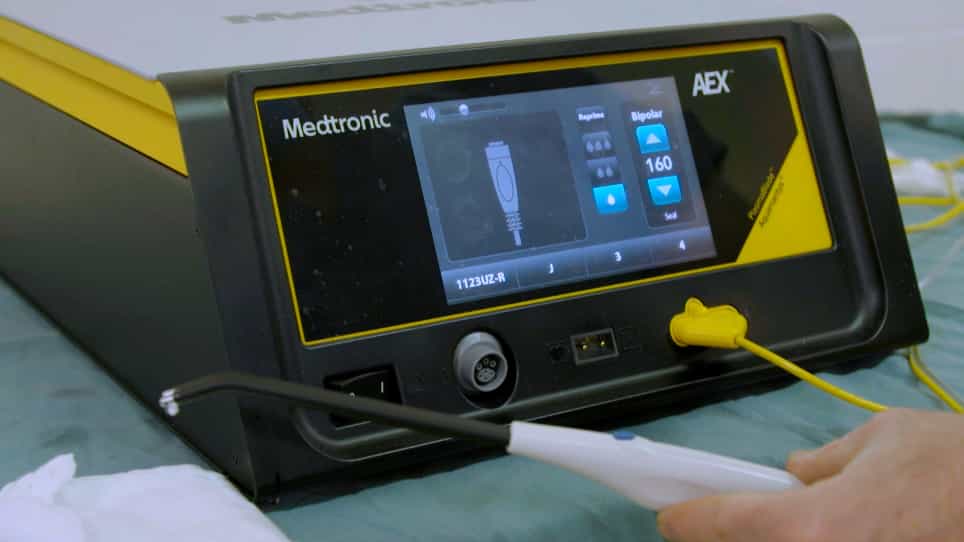
A Saline/Bipolar Radiofrequency Energy Device As an Adjunct for Hemostasis in Solid Organ Injury/Trauma
Published on: July 28, 2020
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:15
Thoracic Aorta